Single-Cell Resolution of Cellular Landscape and Intercellular Communication in Colorectal Cancer Reveals Key Oncogenic Drivers and Therapeutic Targets
This comprehensive single-cell RNA sequencing analysis of colorectal cancer identifies significant shifts in cell type populations, genomic stability, and intercellular communication within the tumor microenvironment compared to adjacent normal tissue. Key findings include widespread aneuploidy and hyper-proliferation in malignant intestinal epithelial cells, a pronounced M2-like polarization of tumor-associated macrophages, and an enrichment of immunosuppressive T cell subsets. The study highlights extensive remodeling of cell-cell interaction networks and activation of critical oncogenic and immune evasion pathways, providing a rich resource for understanding colorectal cancer pathogenesis and identifying novel therapeutic avenues.
Contents
- Dataset overview
- UMAP Analysis of Single-Cell Populations by Condition, Sample, Cell Type, and Ploidy in Colon Tissue
- Major Cell Type Score and Ploidy Status Visualization on UMAP
- Marker Gene Expression Across Cell Subsets
- Copy Number Variation (CNV) Landscape of Tumor-Origin Intestinal Epithelial Cells in Colorectal Cancer
- UMAP Visualization of CNV Patterns by Cell Type, Ploidy, Condition, and Sample
- Minor Cell Type Population Analysis in Colon Adenocarcinoma
- T Cell Subset Population Analysis in Colorectal Cancer
- Analysis of T Cell Subset Proportions in Colorectal Cancer
- Macrophage Subset Population Analysis in Colorectal Cancer
- Macrophage Subset Population Shifts in Colorectal Cancer
- Ploidy Status of Intestinal Epithelial Cells in Colorectal Cancer
- Cell-Cell Interaction Patterns in Colorectal Tissue: Tumor vs. Adjacent Normal
- Condition-Specific Cell-Cell Interaction Patterns in Colorectal Cancer
- Condition-Specific Cell-Cell Interaction Patterns of Immune Checkpoint and Cell Cycle Pathway Genes in Colorectal Cancer
- Intestinal Epithelial Cell Condition-Specific Surfaceome Markers in Colorectal Cancer
- Macrophage Surfaceome Markers in Colorectal Cancer
- Fibroblast Condition-Specific Surfaceome Markers in Colorectal Cancer
- T cell CD4+ Condition-Specific Surfaceome Markers in Colorectal Cancer
- Dysregulation of Cell Cycle Pathway Genes in Intestinal Epithelial Cells of Colorectal Cancer
- Gene Ontology (GSA) Enrichment in Intestinal Epithelial Cells Across Different Conditions in Colorectal Cancer
- Gene Set Enrichment Analysis (GSEA) Across Colorectal Cancer Cell Types
- Discussion
- Query List
0. Dataset overview
Dataset Summary
- Dimensions: 85,038 cells by 27,779 genes.
- Species: Human.
- Tissue: Colon.
- Conditions: Tumor, Adj_normal.
- Observed Ploidy: Diploid (86.3%), Aneuploid (13.4%), Unclear (0.3%).
- Resolved Tumor-Origin Cell Type: Intestinal Epithelial cell.
Metadata Columns (obs)
- Clinical & Sample Information: SPECIMEN_TYPE, SOURCE_HOSPITAL, PatientTypeID, HistologicTypeSimple, MMRStatus, TumorStage, NodeStatusSimple, MetastasisStatus, TumorSize, Sex, Age, Ethnicity, Race, batchID, sample, condition.
- Cell Type Annotations: celltype_major, celltype_minor, celltype_subset.
- Ploidy & CNV Information: ploidy_score, ploidy_dec, aneuploid_gsa_candidate, diploid_gsa_candidate, cnv_cluster, cnv_sample_diversity_index.
Cell Type Hierarchy
- Major Cell Types: Intestinal Epithelial cell, Myeloid cell, T cell, Mast cell, B cell, Endothelial cell, Stromal cell, unassigned.
- Minor Cell Types: Intestinal Epithelial cell, Macrophage, T cell CD4+, Mast cell, Plasma cell, ILC, Endothelial cell, B cell, T cell CD8+, Fibroblast, NK cell, Smooth muscle cell, unassigned.
- Subset Cell Types: Enterocyte, Microfold cell, Goblet cell, Crypt cell, Macrophage (M1), T cell (Tfh), Mast cell, Plasma cell, T cell (Naive), ILC1, Endothelial cell, B cell (Follicular), Tuft cell, Fibroblast, Macrophage (M2A), T cell (Th1), T cell (Th2), T cell (Cytotoxic), B cell (Memory), T cell (Treg), Paneth cell, NK cell, Smooth muscle cell, and many more, including various subtypes.
Precomputed Results
- Cell-Cell Interaction (CCI): Available per condition and per sample, stored in uns['CCI'] and uns['CCI_sample'] respectively, with columns like gene_pair, cell_pair, pval, mean.
- Differential Expression Genes (DEG): Results for each celltype_minor comparing one condition vs. the rest, stored in uns['DEG'], with columns like log2_FC, pval_adj, gene, Rp.
- Gene Set Enrichment Analysis (GSEA): Results for each celltype_minor comparing one condition vs. the rest, stored in uns['GSEA'], with columns like Name, NES, FDR q-val, Lead_genes.
- Gene Set Analysis / Gene Ontology (GSA/GO): Results for each celltype_minor comparing one condition vs. the rest, stored in uns['GSA_up'], with columns like Term, pval_adj, genes.
Inferred Disease Context
- The dataset is inferred to be related to Colorectal cancer, based on labels such as 'Tumor' and 'Adj_normal', 'Colon' tissue, extensive cancer clinical metadata, detected 'Aneuploid' cells, and 'Intestinal Epithelial cell' as the resolved tumor-origin cell type. CNV estimates and differential analyses against 'Adj_normal' further support this context.
1. UMAP Analysis of Single-Cell Populations by Condition, Sample, Cell Type, and Ploidy in Colon Tissue
[Analysis Visualization Results]...
Analysis Overview
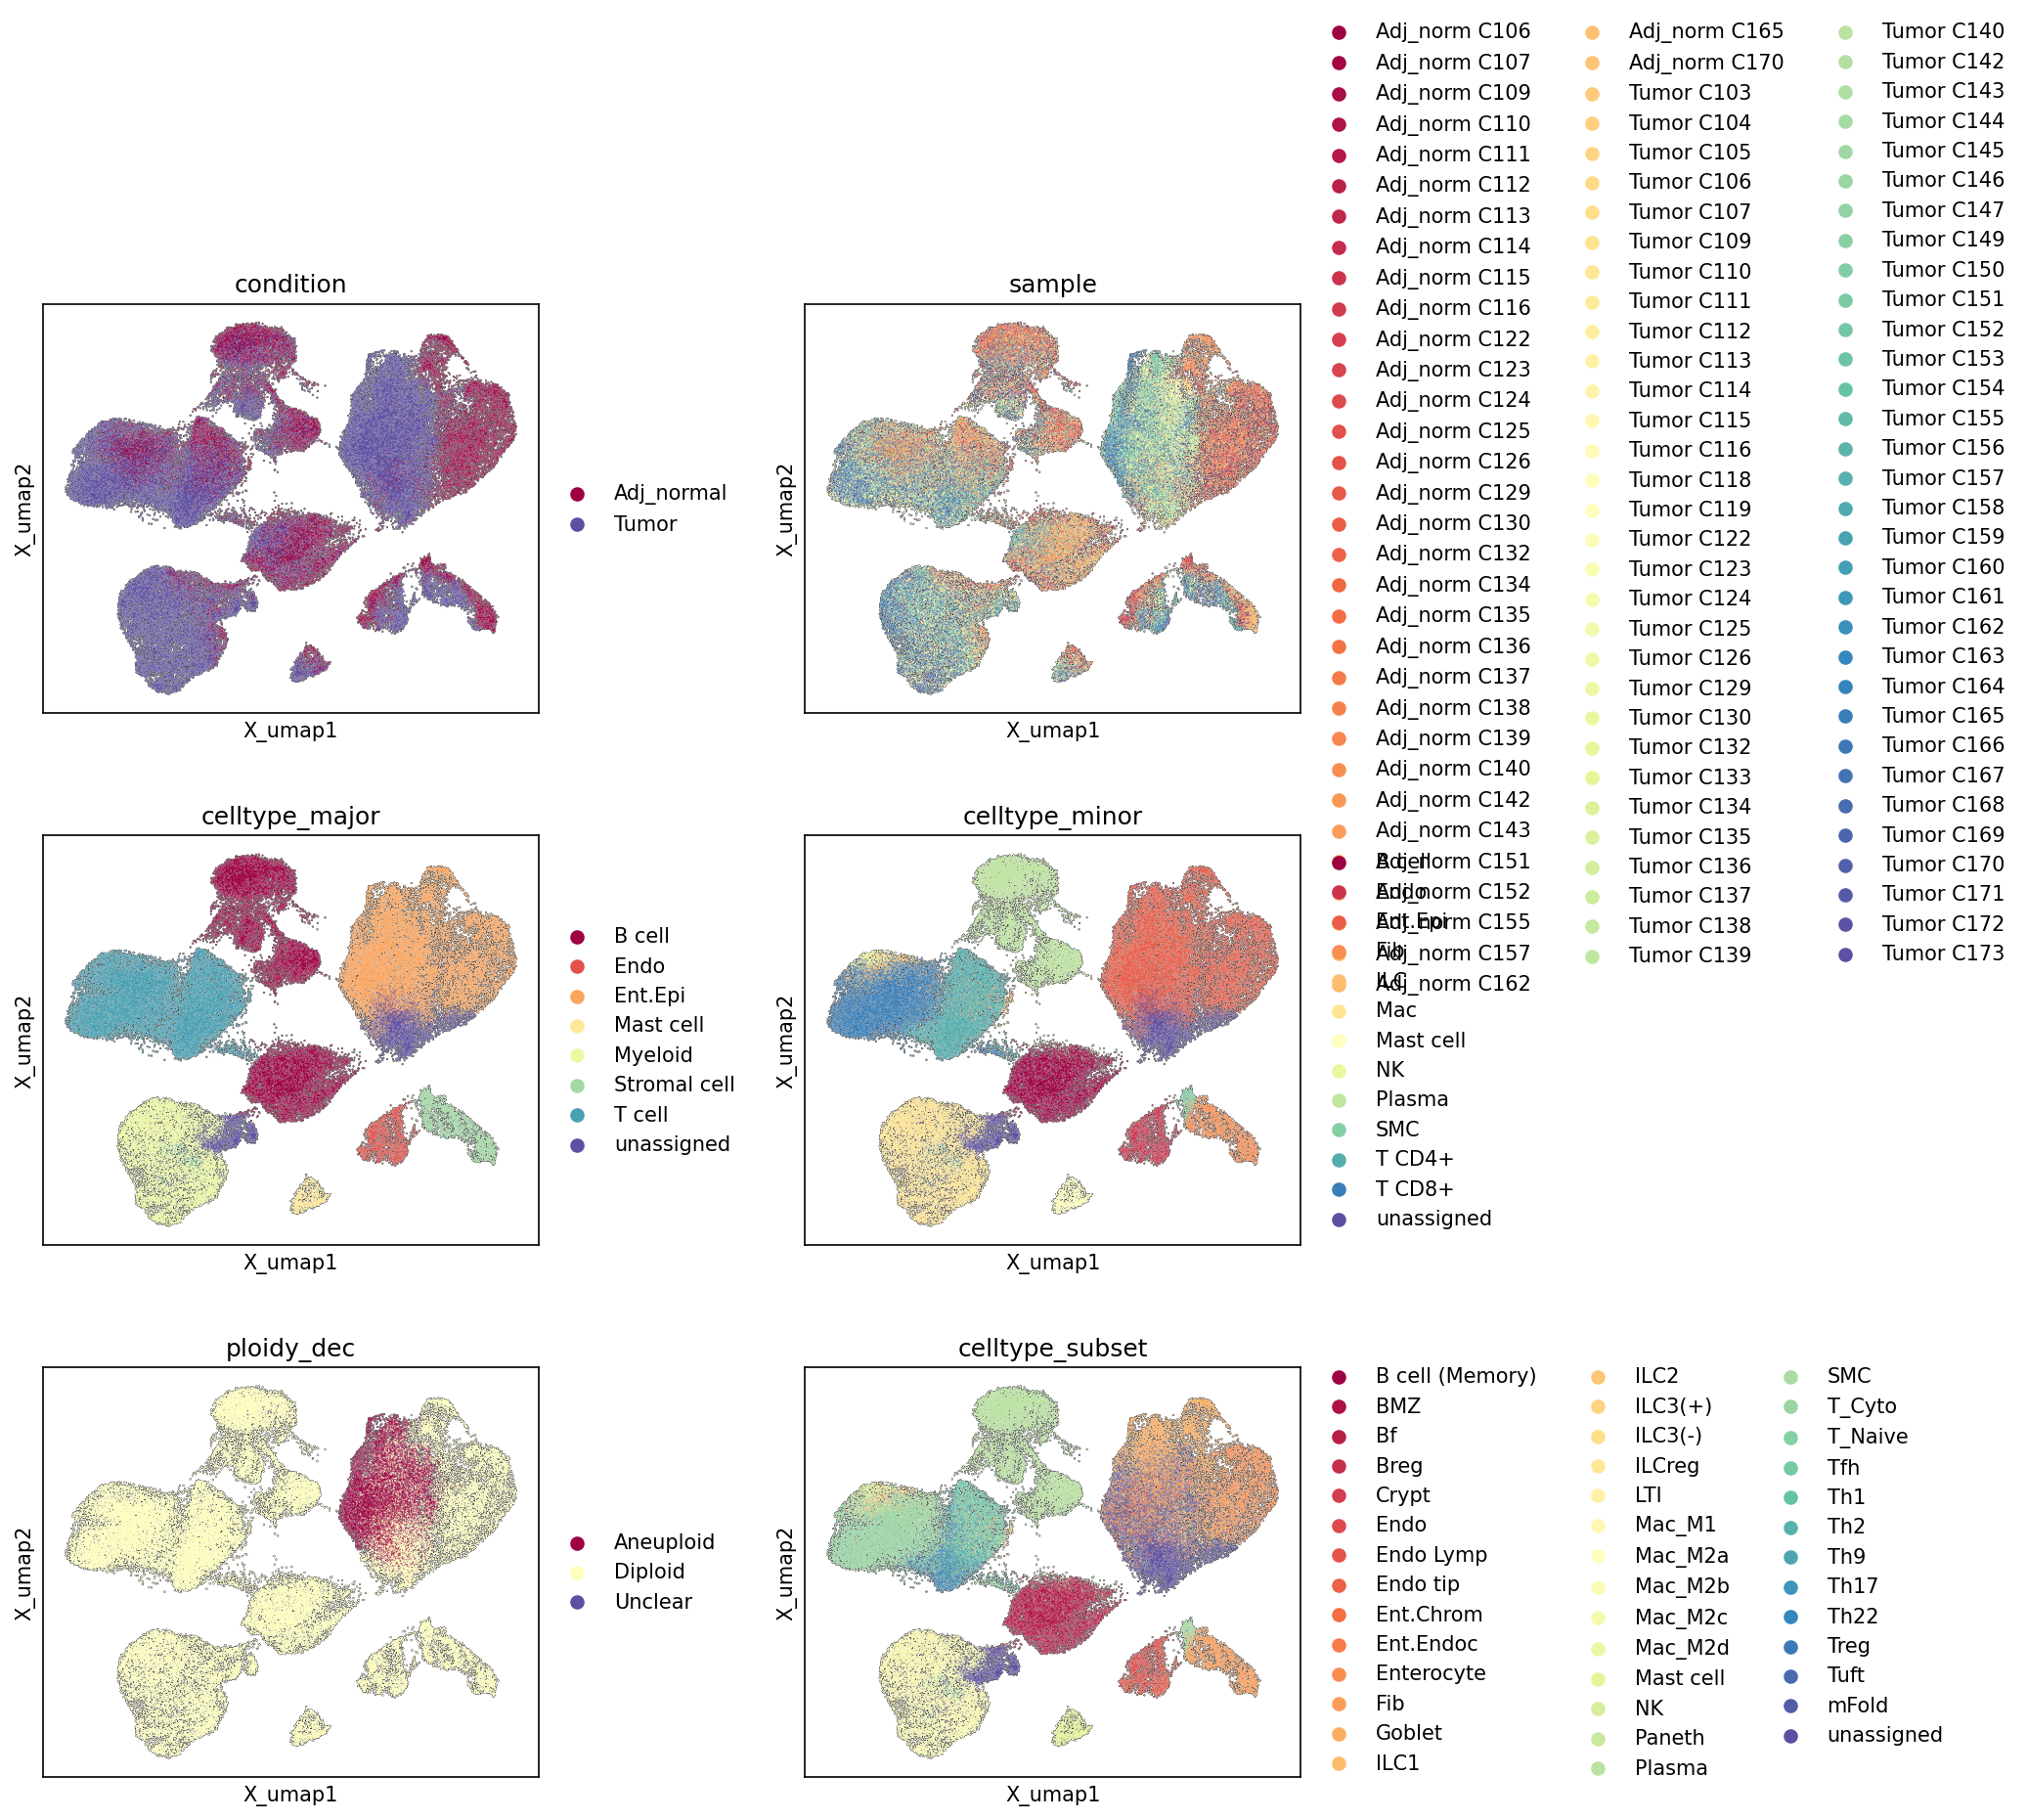
This analysis presents Uniform Manifold Approximation and Projection (UMAP) visualizations of single-cell RNA-sequencing data from colon tissue. The UMAP plots show the distribution of 85,038 cells, colored by several key metadata annotations: 'condition' (Tumor vs. Adj_normal), 'sample', 'celltype_major', 'celltype_minor', 'ploidy_dec', and 'celltype_subset'. These visualizations are critical for assessing the overall structure of the dataset, identifying distinct cell populations, evaluating sample integration, and understanding the biological differences between tumor and adjacent normal tissues, particularly in the context of colorectal cancer.
Visual Summary
Condition
The 'condition' UMAP reveals a clear separation between cells originating from "Tumor" and "Adj_normal" tissues. While there is some intermingling at the boundaries of major clusters, distinct regions are predominantly occupied by cells from one condition or the other. Specifically, several large cell clusters appear enriched for "Tumor" cells (purple), while other clusters are predominantly "Adj_normal" (red). This indicates significant transcriptomic differences driven by the disease state.
Sample
The 'sample' UMAP shows that cells from different samples (both tumor and adjacent normal) are generally well-interspersed across the UMAP space, particularly within shared cell type clusters. This suggests a good batch integration, where variations due to individual samples are largely minimized, allowing for biological signals to dominate the clustering. However, some smaller clusters show enrichment for specific samples, which could indicate unique biological features of those samples or residual batch effects.
Celltype_major
The 'celltype_major' UMAP demonstrates distinct clustering of the eight major cell types. "Intestinal Epithelial cell" (Ent.Epi, orange) forms a large, distinct cluster, as do "T cell" (cyan) and "Myeloid cell" (light green) populations, which appear in several related clusters. "B cell" (dark red), "Endothelial cell" (Endo, red), and "Stromal cell" (light yellow) also form relatively separated clusters. The 'unassigned' cells (dark purple) form a small, compact cluster, suggesting a potentially distinct but currently uncharacterized cell population. This clear separation indicates robust cell type identification.
Celltype_minor
The 'celltype_minor' UMAP provides a more granular view, showing further sub-clustering within the major cell types. For instance, T cells are resolved into "T cell CD4+" and "T cell CD8+", which largely co-cluster but show some internal structure. Myeloid cells are resolved into "Macrophage" (Mac), "NK cell", and "Mast cell". Plasma cells form a distinct cluster within the broader B cell area. "Intestinal Epithelial cell" remains a large, dominant population with internal heterogeneity. The fine-grained clustering indicates successful resolution of diverse cell populations.
Ploidy_dec
The 'ploidy_dec' UMAP highlights the distribution of cells based on their estimated ploidy status: "Aneuploid" (dark red), "Diploid" (light yellow), and "Unclear" (dark purple). A significant population of "Aneuploid" cells forms a large, distinct cluster, predominantly overlapping with the main "Intestinal Epithelial cell" cluster and with regions heavily populated by "Tumor" cells from the 'condition' UMAP. The vast majority of "Diploid" cells form several large clusters, broadly corresponding to immune, stromal, and some epithelial cell populations, and are prevalent in "Adj_normal" regions. The "Unclear" cells are scattered, suggesting they might represent cells with ambiguous ploidy calls or transitional states.
Celltype_subset
The 'celltype_subset' UMAP offers the highest resolution, revealing the intricate heterogeneity within the minor cell types. For example, Intestinal Epithelial cells are further resolved into "Enterocyte", "Goblet cell", "Crypt cell", "Paneth cell", "Enteroendocrine cell", "Tuft cell", and "Microfold cell". T cells show subsets like "T cell (Tfh)", "T cell (Th1)", "T cell (Th17)", "T cell (Treg)", and "T cell (Cytotoxic)". Macrophages are refined into subtypes such as "Macrophage (M1)", "Macrophage (M2A)", "Macrophage (M2B)", "Macrophage (M2C)", and "Macrophage (M2D)". The clear separation of these subsets, especially within the large "Intestinal Epithelial cell" and immune clusters, underscores the rich cellular diversity captured in the dataset and the successful annotation at this granular level.
Biological Interpretation
- Tumor-specific Cell Populations and Aneuploidy: The pronounced separation of "Tumor" and "Adj_normal" conditions, coupled with the clustering of "Aneuploid" cells, strongly supports the identification of tumor-derived cells. The overlap between "Aneuploid" cells and the "Intestinal Epithelial cell" population (as highlighted in the 'ploidy_dec' and 'celltype_major' UMAPs) confirms that the "Resolved tumor-origin cell type" is indeed Intestinal Epithelial cells, consistent with colorectal carcinoma, where epithelial cells undergo neoplastic transformation and often acquire aneuploidy.
- Immune Cell Infiltration and Heterogeneity: The UMAPs illustrate the diverse immune landscape within the colon, resolving T cells, B cells, Myeloid cells, and their various subsets. The distribution of these immune cells across "Tumor" and "Adj_normal" regions is crucial. For instance, different T cell subsets (e.g., cytotoxic T cells vs. regulatory T cells) might be enriched or depleted in the tumor microenvironment, reflecting distinct anti-tumor or pro-tumor immune responses. The presence of diverse macrophage subsets (M1, M2A-D) suggests complex myeloid cell plasticity within the tissue.
- Stromal Remodeling in Cancer: Fibroblasts and Smooth muscle cells, key components of the stromal compartment, show distinct clustering. Their interaction with tumor cells and immune cells is vital for tumor progression. Changes in their distribution or specific subtypes (e.g., cancer-associated fibroblasts) between "Tumor" and "Adj_normal" regions could reflect tumor-induced stromal remodeling.
- Epithelial Cell Identity and Malignant Transformation: The detailed 'celltype_subset' UMAP for Intestinal Epithelial cells (Enterocyte, Goblet cell, Crypt cell, etc.) allows for investigation into which specific epithelial subsets are more prone to aneuploidy and transformation, or how their proportions change in the tumor context. The presence of a substantial aneuploid epithelial population confirms their malignant potential within the tumor.
- Annotation Quality and Dataset Structure: The clear and consistent clustering of cell types across different levels of resolution (major, minor, subset) and the generally good integration of samples suggest high quality of cell type annotation and effective removal of major technical variations. The 'unassigned' cluster warrants further investigation to determine if it represents a novel cell type, doublets, or cells in a rare or transitional state.
Annotation Notes
The UMAPs provide a comprehensive overview of the single-cell landscape, confirming robust cell type identification and the distinct molecular signatures associated with tumor versus adjacent normal conditions. The clear separation of cell types at various granularities (major, minor, subset) indicates successful clustering and annotation. The observation of aneuploid cells predominantly within the intestinal epithelial compartment in tumor samples aligns well with the biological expectations for colorectal cancer. The distribution of cells across samples suggests good integration, which is critical for downstream differential analyses. Further investigation into the 'unassigned' cluster could refine the cell type annotations.
2. Major Cell Type Score and Ploidy Status Visualization on UMAP
[Analysis Visualization Results]...
Analysis Overview
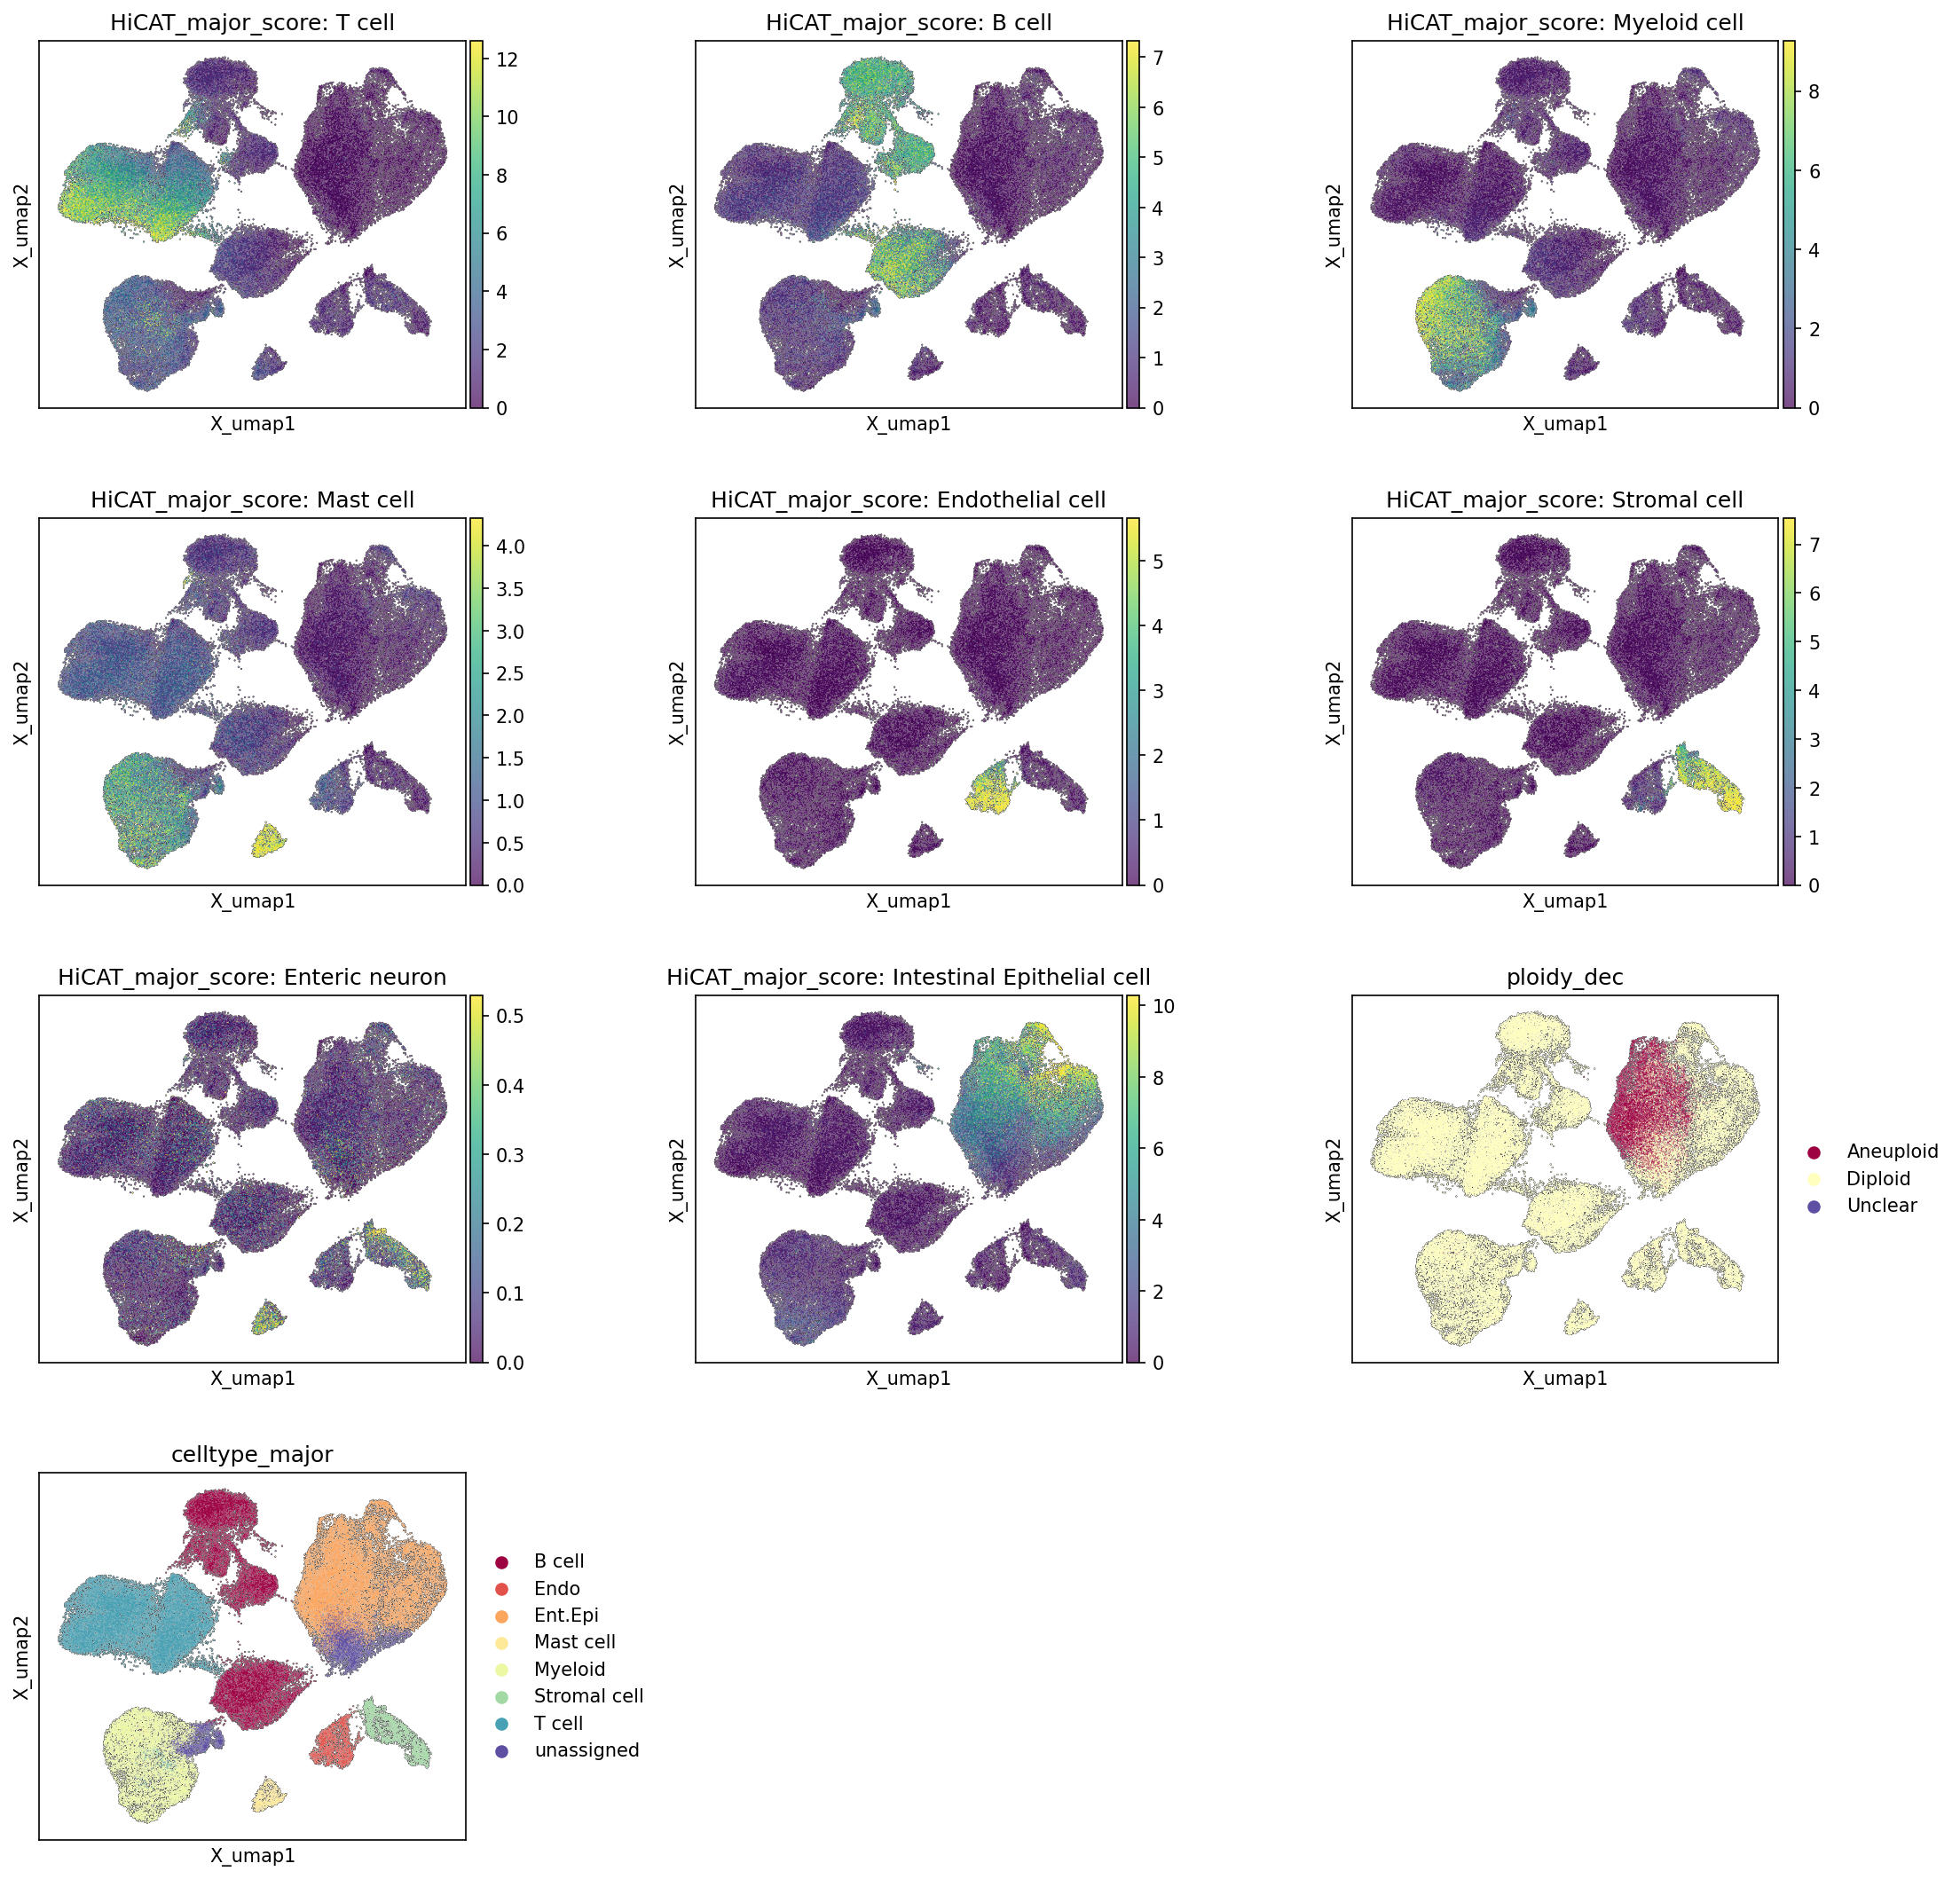
This analysis presents UMAP visualizations of single-cell RNA-seq data from human Colon tissue. The primary goal was to visualize the distribution of major cell type scores, computed by HiCAT, across the UMAP embedding. This is complemented by a UMAP colored by the celltype_major assignments and another showing the ploidy_dec status (Diploid, Aneuploid, Unclear) for all cells. The dataset includes cells from both Tumor and Adjacent normal conditions, with a focus on colorectal cancer.
Visual Summary
The UMAP embedding reveals a complex architecture with distinct clusters representing various cell populations.
Major Cell Type Score Distribution (HiCAT_major_score plots):
- Each major cell type (T cell, B cell, Myeloid cell, Mast cell, Endothelial cell, Stromal cell, Intestinal Epithelial cell, Enteric neuron) exhibits high scores predominantly within specific, well-separated regions of the UMAP. This indicates a strong and localized presence of cells characteristic of that type.
- For instance, HiCAT_major_score: T cell shows high scores in the clusters positioned at the lower-left and upper-left, which correspond directly to the T cell cluster in the celltype_major plot. Similarly, Intestinal Epithelial cell scores are highest in the large cluster on the upper-right, consistent with the Ent.Epi label.
- The Enteric neuron score plot shows very low scores across the entire UMAP, with only a few sparse cells exhibiting minimal scores (max 0.5), suggesting that enteric neurons are either very rare, poorly captured, or transcriptionally less distinct in this dataset relative to the defined major types.
Ploidy Status (ploidy_dec plot):
- A prominent cluster of Aneuploid cells (red) is observed, primarily localized within the large upper-right cluster.
- The vast majority of the remaining cells across the UMAP are Diploid (yellow), distributed among various other clusters.
- A very small number of cells are labeled as Unclear (purple), scattered without forming a distinct cluster.
Major Cell Type Assignment (celltype_major plot):
- This plot provides the assigned identity for each cell. It confirms that the areas with high HiCAT scores for a given cell type generally align perfectly with the corresponding celltype_major labeled clusters.
- The Intestinal Epithelial cell (Ent.Epi, orange) cluster in the upper-right region is large and distinct, as are clusters for T cells (Teal), Myeloid cells (Light green), B cells (Maroon), Stromal cells (Light yellow), Endothelial cells (Dark orange), and Mast cells (Light purple).
- A relatively small cluster of 'unassigned' cells (Purple-grey) is present, located centrally and not strongly overlapping with any high HiCAT major cell type score regions.
Biological Interpretation
The UMAP visualizations effectively segment the single-cell transcriptomic landscape of the Colon tissue, highlighting distinct cell identities and their spatial relationships in the embedding.
- Robust Cell Type Identification: The strong concordance between the HiCAT major cell type scores and the celltype_major annotations provides confidence in the accuracy and specificity of the cell type assignments. Each major cell type forms transcriptionally distinct populations within the UMAP, reflecting their unique gene expression profiles.
- Identification of Malignant Epithelial Cells: The Intestinal Epithelial cell cluster represents a significant portion of the dataset and shows a strong overlap with the Aneuploid cell population as observed in the ploidy_dec plot. This is a critical finding in the context of colorectal cancer, as the resolved tumor-origin cell type is Intestinal Epithelial cell, and aneuploidy is a hallmark of malignancy. This suggests that a substantial proportion of the Intestinal Epithelial cell population within the tumor samples are cancerous cells. PubMed Search: Colorectal cancer aneuploidy epithelial cells
- Tumor Microenvironment Composition: The presence of distinct clusters for various immune cells (T cells, B cells, Myeloid cells, Mast cells) and stromal cells (Endothelial cells, Stromal cells) underscores the complexity of the colorectal cancer tumor microenvironment. These non-malignant cells play crucial roles in tumor progression, immune response, and therapeutic efficacy. Their clear segregation on the UMAP indicates distinct roles and states within the tumor and adjacent normal tissues.
- Minor Cell Populations: The low scores for Enteric neuron suggest that these cells are either rare in the analyzed samples, have low RNA content leading to poor capture, or their transcriptional profiles are not as strongly defined by the marker genes used for scoring within this particular assay and annotation scheme. The "unassigned" cells may represent rare cell types, transitional states, or cells with ambiguous transcriptional profiles that did not meet the confidence thresholds for specific major cell type assignment.
Annotation Notes
- The agreement between the HiCAT_major_score plots and the celltype_major assignments confirms the high quality of cell type annotation and the robustness of the clustering approach. The scores provide a quantitative measure of confidence for each cell's assignment to its respective major cell type.
- The clear separation of distinct cell populations on the UMAP embedding indicates a well-resolved single-cell dataset, allowing for meaningful downstream differential expression and functional analyses for each identified cell type.
- The ploidy_dec status provides a crucial layer of annotation for distinguishing malignant from non-malignant cells, especially within the Intestinal Epithelial cell compartment. This distinction is paramount for studying tumor-specific biology and interactions within the tumor microenvironment.
3. Marker Gene Expression Across Cell Subsets
[Analysis Visualization Results]...
Analysis Overview
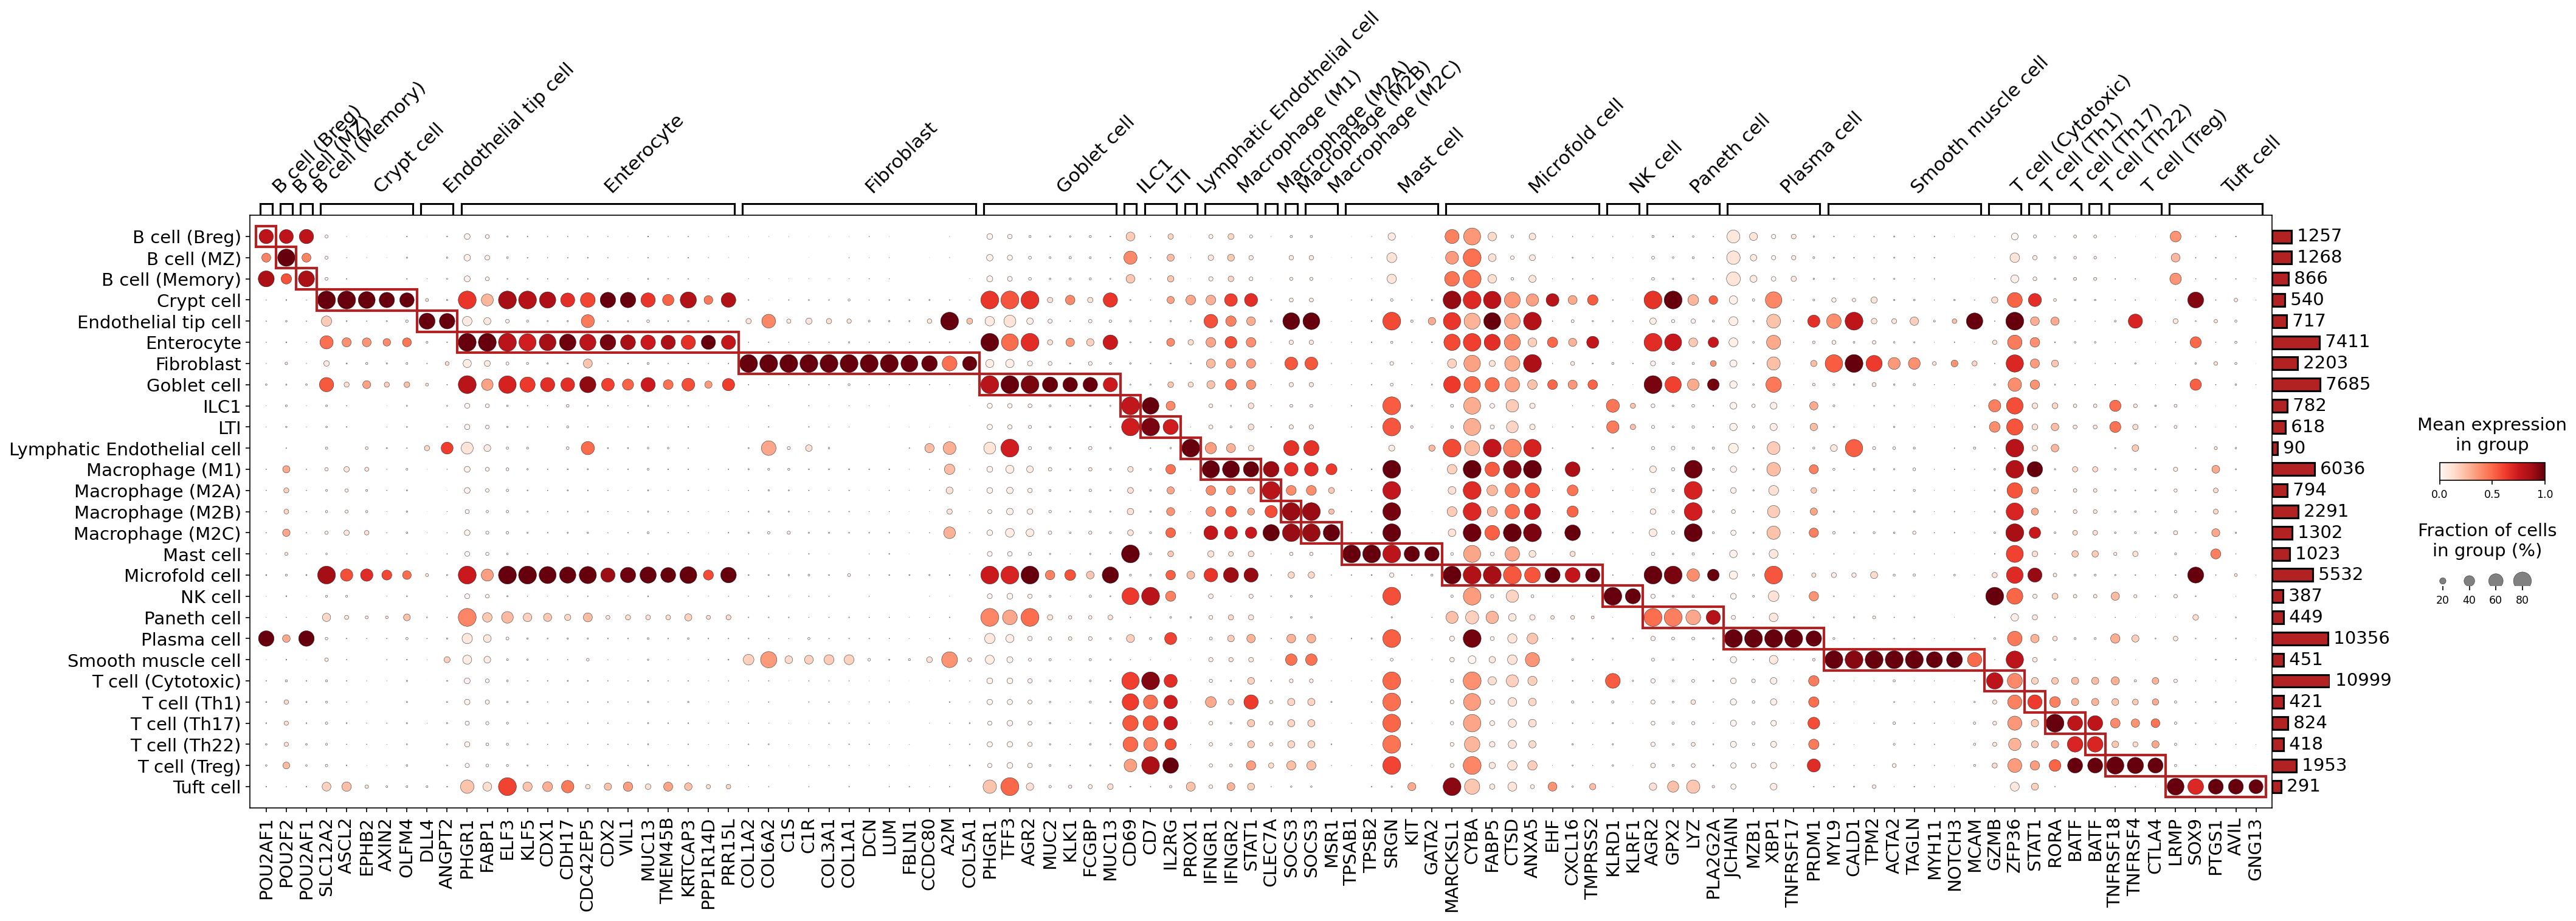
This analysis presents a dot plot visualizing the expression of marker genes across various celltype_subset populations identified within the Colon tissue single-cell RNA-seq dataset. The primary goal is to assess and confirm the identity of these cell subsets based on the specificity and expression levels of known or highly enriched marker genes. Each row represents a specific cell subset, and each column represents a marker gene. The size of the dot indicates the fraction of cells within that subset expressing the gene, while the color intensity (from light red to dark red) reflects the mean expression level of the gene in that cell subset. The genes are grouped and labeled with a 45-degree rotation for improved readability, and red boxes highlight gene clusters characteristic of specific cell types or closely related cell type groups.
Visual Summary
The dot plot effectively displays distinct patterns of gene expression, allowing for clear differentiation between most celltype_subset populations. Several groups of genes show highly specific and elevated expression within a single cell type or a small cluster of related cell types, often highlighted by the red bounding boxes. For instance, B cell (Breg), B cell (MZ), and B cell (Memory) show strong expression of pan-B cell markers, with some subtle differences. Similarly, distinct epithelial cell types such as Crypt cell, Enterocyte, Goblet cell, Microfold cell, Paneth cell, and Tuft cell exhibit unique marker gene profiles. Macrophage subtypes (M1, M2A, M2B, M2C) also show shared and unique markers. T cell subsets, including T cell (Cytotoxic), T cell (Th1), T cell (Th17), T cell (Th22), and T cell (Treg), demonstrate expected differential expression of T-cell related genes. Overall, the plot reveals well-defined clusters of marker genes corresponding to the annotated cell subsets, indicating robust cell type classification. The bar chart on the right indicates the total number of cells for each celltype_subset.
Biological Interpretation
The marker gene expression patterns observed in the dot plot largely support the assigned celltype_subset annotations, providing strong evidence for their distinct identities within the colon microenvironment.
- B cell Subsets: POU2AF1 and POU2F2 (OCT transcription factors) are broadly expressed across B cell subsets, consistent with their role in B cell development and function PubMed Search: POU2AF1 POU2F2 B cell function. CD79A is another canonical B cell marker, part of the B cell receptor complex, which shows strong expression. Distinct B cell subtypes (B cell (Breg), B cell (MZ), B cell (Memory)) are evident by specific or enriched expression profiles, although the plot shows more general B cell markers. Plasma cells, a mature B cell lineage, are clearly identified by MZB1, XBP1, and PRDM1 (BLIMP1) UniProt: PRDM1, indicative of their antibody-secreting function.
Intestinal Epithelial Cells:
- Crypt cells: Highly express ASCL2, EPHB2, and AXIN2, characteristic markers of intestinal stem cells and proliferative progenitor cells located in the crypts of Lieberkühn GeneCards: ASCL2.
- Enterocytes: Show strong expression of FABP1, FABP2, VIL1, and CDX1/2, reflecting their role in nutrient absorption and epithelial differentiation GeneCards: VIL1.
- Goblet cells: Marked by MUC2, TFF3, and AGR2, which are involved in mucus production and protection of the intestinal barrier GeneCards: MUC2.
- Paneth cells: Distinctly express LYZ and DEFA5, indicating their role in secreting antimicrobial peptides GeneCards: LYZ.
- Tuft cells: Identified by PTGS1 and AVIL, consistent with their role in chemosensation and immune modulation PubMed Search: Tuft cell markers PTGS1 AVIL.
- Microfold cells: Show enrichment of GP2, a specific marker for M cells involved in antigen sampling from the gut lumen GeneCards: GP2.
Stromal Cells:
- Fibroblasts: Characterized by high expression of COL1A1, COL3A1, COL5A1, DCN, and LUM, indicative of their extracellular matrix production function GeneCards: DCN.
- Smooth muscle cells: Express ACTA2 (alpha-SMA), TAGLN, MYH11, and TPM2, which are essential components of the contractile machinery in muscle cells GeneCards: ACTA2.
Endothelial Cells:
- Endothelial tip cell and Lymphatic Endothelial cell show expression of general endothelial markers like PECAM1 and CDH5 (VE-cadherin), but also subtype-specific genes. PROX1 is a key transcription factor for lymphatic endothelial cell specification GeneCards: PROX1.
Myeloid Cells:
- Macrophages: Subsets (M1, M2A, M2B, M2C) display overlapping and distinct marker expression. MSR1 (CD204) and ANXA5 are observed markers. These distinctions align with the known plasticity and functional polarization of macrophages PubMed Search: Macrophage M1 M2 markers.
- Mast cells: Strongly express KIT (CD117), TPSAB1, and TPSB2, confirming their identity GeneCards: KIT.
T cells:
- T cell (Cytotoxic) shows high expression of GZMB, indicative of their effector function GeneCards: GZMB.
- T cell (Th1) expresses STAT1, involved in IFN-gamma signaling.
- T cell (Treg) expresses CTLA4 and FOXP3, key molecules for immune suppression GeneCards: FOXP3.
- RORC (RORγt) is a defining transcription factor for T cell (Th17) GeneCards: RORC.
- Natural Killer (NK) cells: Express KLRF1, which is associated with NK cell function.
Annotation Notes
The comprehensive marker expression dot plot confirms that the celltype_subset annotations are well-supported by distinct and characteristic gene expression profiles. Most cell types exhibit specific enrichment of expected lineage-defining markers. The clear segregation of epithelial, immune, and stromal cell populations, and the further refined distinctions within these major categories (e.g., specific epithelial cell types, macrophage subsets, T cell subsets), indicate high confidence in the quality of the cell type annotations. This robust annotation is crucial for downstream differential expression, pathway analysis, and cell-cell interaction studies, especially in the context of colorectal cancer.
4. Copy Number Variation (CNV) Landscape of Tumor-Origin Intestinal Epithelial Cells in Colorectal Cancer

[Analysis Visualization Results]...
Analysis Overview
This analysis investigates the copy number variation (CNV) profiles of Intestinal Epithelial cells, identified as the tumor-origin cell type, across different patient samples and conditions (Adj_normal, Diploid Tumor, and Tumor). The primary goal is to visualize the genomic instability within these cells, grouped by sample, and to summarize frequently amplified genomic regions. The log2(Copy Number Ratio) is depicted in the first heatmap, showing relative copy number gains (red) and losses (blue) across the genome. The second heatmap provides a summary of the frequency of amplification for specific cytogenetic bands within each tumor sample.
Visual Summary
log2(CNR) Heatmap
The first heatmap illustrates the genomic landscape of copy number alterations in Intestinal Epithelial cells.
- Adjacent Normal Samples: Cells from Adj_normal samples exhibit largely stable copy numbers, with minimal red (amplification) or blue (deletion) signals, indicating genomic integrity as expected for healthy tissue.
- Diploid Tumor Samples: A subset of tumor samples, classified as Diploid Tumor, show some focal CNVs, particularly amplifications, although generally less pervasive than in the Tumor samples. This suggests that even cells broadly categorized as diploid might harbor specific genomic alterations.
- Tumor Samples: The Tumor samples display extensive and widespread copy number alterations, characterized by numerous and often large regions of amplification (red) and deletion (blue). This genomic instability is a hallmark of cancer.
Common CNV Patterns:
- Amplifications: Frequent amplifications are observed on chromosome arms 8q, 13q, and 20q across many tumor samples. Focal amplifications are also noticeable in regions like 7p (containing EGFR) and 17q (containing ERBB2) in specific samples.
- Deletions: Recurrent deletions are apparent on chromosome arms 8p, 17p (containing TP53), and 18q.
CNA Summary Heatmap (Amplification Frequency)
The second heatmap provides a quantitative summary of amplification frequencies within specific cytogenetic bands for each tumor sample.
Highly Amplified Regions:
- 8q24.21 (MYC): This region consistently shows a very high frequency of amplification, often exceeding 80% of cells, across nearly all Tumor samples. The MYC oncogene is located in this band.
- 13q34 (CDX2, GABRA4, etc.): A high frequency of amplification is observed in this region across multiple tumor samples. CDX2 is a transcription factor important in intestinal differentiation.
- 20q13.33 (TPX2, BCL2L1, etc.): This region also exhibits frequent amplification in a large proportion of cells across many tumor samples.
- 7p11.2 (EGFR): Amplification in this region, containing the EGFR gene, is prominent in a subset of tumor samples (e.g., C104, C106, C132, C134, C140, C143, C169), often affecting a substantial percentage of cells.
- 17q12 (ERBB2): This region, containing the ERBB2 (HER2) oncogene, shows amplification in specific samples (e.g., C134, C143, C169).
- Inter-Sample Heterogeneity: While some amplifications like 8q24.21 are broadly present, the overall landscape of frequently amplified regions varies considerably between individual tumor samples, highlighting patient-specific genomic profiles.
Biological Interpretation
The CNV analysis strongly supports the identification of Intestinal Epithelial cell as the tumor-origin cell type. The stark contrast in genomic stability between Adj_normal and Tumor samples, where Adj_normal cells show a near-diploid state and Tumor cells exhibit widespread CNVs, confirms the malignant nature of the latter.
The observed CNV patterns are highly consistent with known genomic alterations in colorectal cancer (CRC):
- 8q Amplification (MYC): Amplification of 8q24.21, harboring the *MYC* oncogene, is a very common event in CRC and is associated with increased cell proliferation and tumor growth [PubMed Search: MYC amplification colorectal cancer]. Its high frequency in nearly all tumor samples underscores its significance in this cohort.
- 18q Deletion: Deletions on 18q, often affecting tumor suppressor genes like *SMAD4* and *DCC*, are common in CRC progression [GeneCards: SMAD4, GeneCards: DCC].
- 17p Deletion (TP53): Deletions involving 17p13.1, the locus of the *TP53* tumor suppressor gene, are critical events in many cancers, including CRC, leading to loss of cell cycle control and increased genomic instability [GeneCards: TP53].
- 20q Amplification: Gain of chromosome arm 20q is a frequent chromosomal aberration in CRC, associated with poor prognosis and harboring several oncogenes [PubMed Search: 20q amplification colorectal cancer].
- EGFR (7p11.2) and ERBB2 (17q12) Amplifications: Amplifications of *EGFR* and *ERBB2* (HER2) are known to drive proliferation and are targeted in various cancers [GeneCards: EGFR, GeneCards: ERBB2]. Their presence in a subset of samples suggests distinct molecular subtypes or evolutionary paths within the tumor cohort.
The distinction between Diploid Tumor and Tumor samples in the log2(CNR) heatmap is crucial. While Diploid Tumor cells might maintain an overall diploid state as measured by broad ploidy assessments, they still exhibit focal CNVs, differentiating them from truly normal cells. The more widespread and numerous CNVs in the Tumor group likely correspond to the Aneuploid cells observed (13.4% of total cells), indicating a higher degree of genomic chaos characteristic of advanced malignancy. This suggests a spectrum of genomic instability even within tumor samples.
Clinical or Translational Implications
The comprehensive CNV profiling of tumor-origin Intestinal Epithelial cell populations offers valuable insights for colorectal cancer research and potential clinical applications:
- Tumor Characterization and Classification: Identification of recurrent CNVs, such as amplifications of *MYC*, *EGFR*, and *ERBB2*, or deletions of *TP53* and 18q, can help stratify CRC patients into molecular subgroups, potentially informing prognosis and predicting treatment response.
- Biomarker Discovery: The specific regions of recurrent amplification (e.g., 8q24.21, 13q34, 20q13.33) and deletion (e.g., 17p, 18q) represent potential diagnostic or prognostic biomarkers that could be further investigated for clinical utility.
- Annotation Validation: The clear CNV patterns observed in the Intestinal Epithelial cell population provide robust validation for their correct identification as the tumor-origin cells, distinct from both normal adjacent tissue and potentially less genomically unstable 'diploid' tumor cells. This strengthens the confidence in subsequent analyses performed on this specific cell type.
5. UMAP Visualization of CNV Patterns by Cell Type, Ploidy, Condition, and Sample
[Analysis Visualization Results]...
Analysis Overview
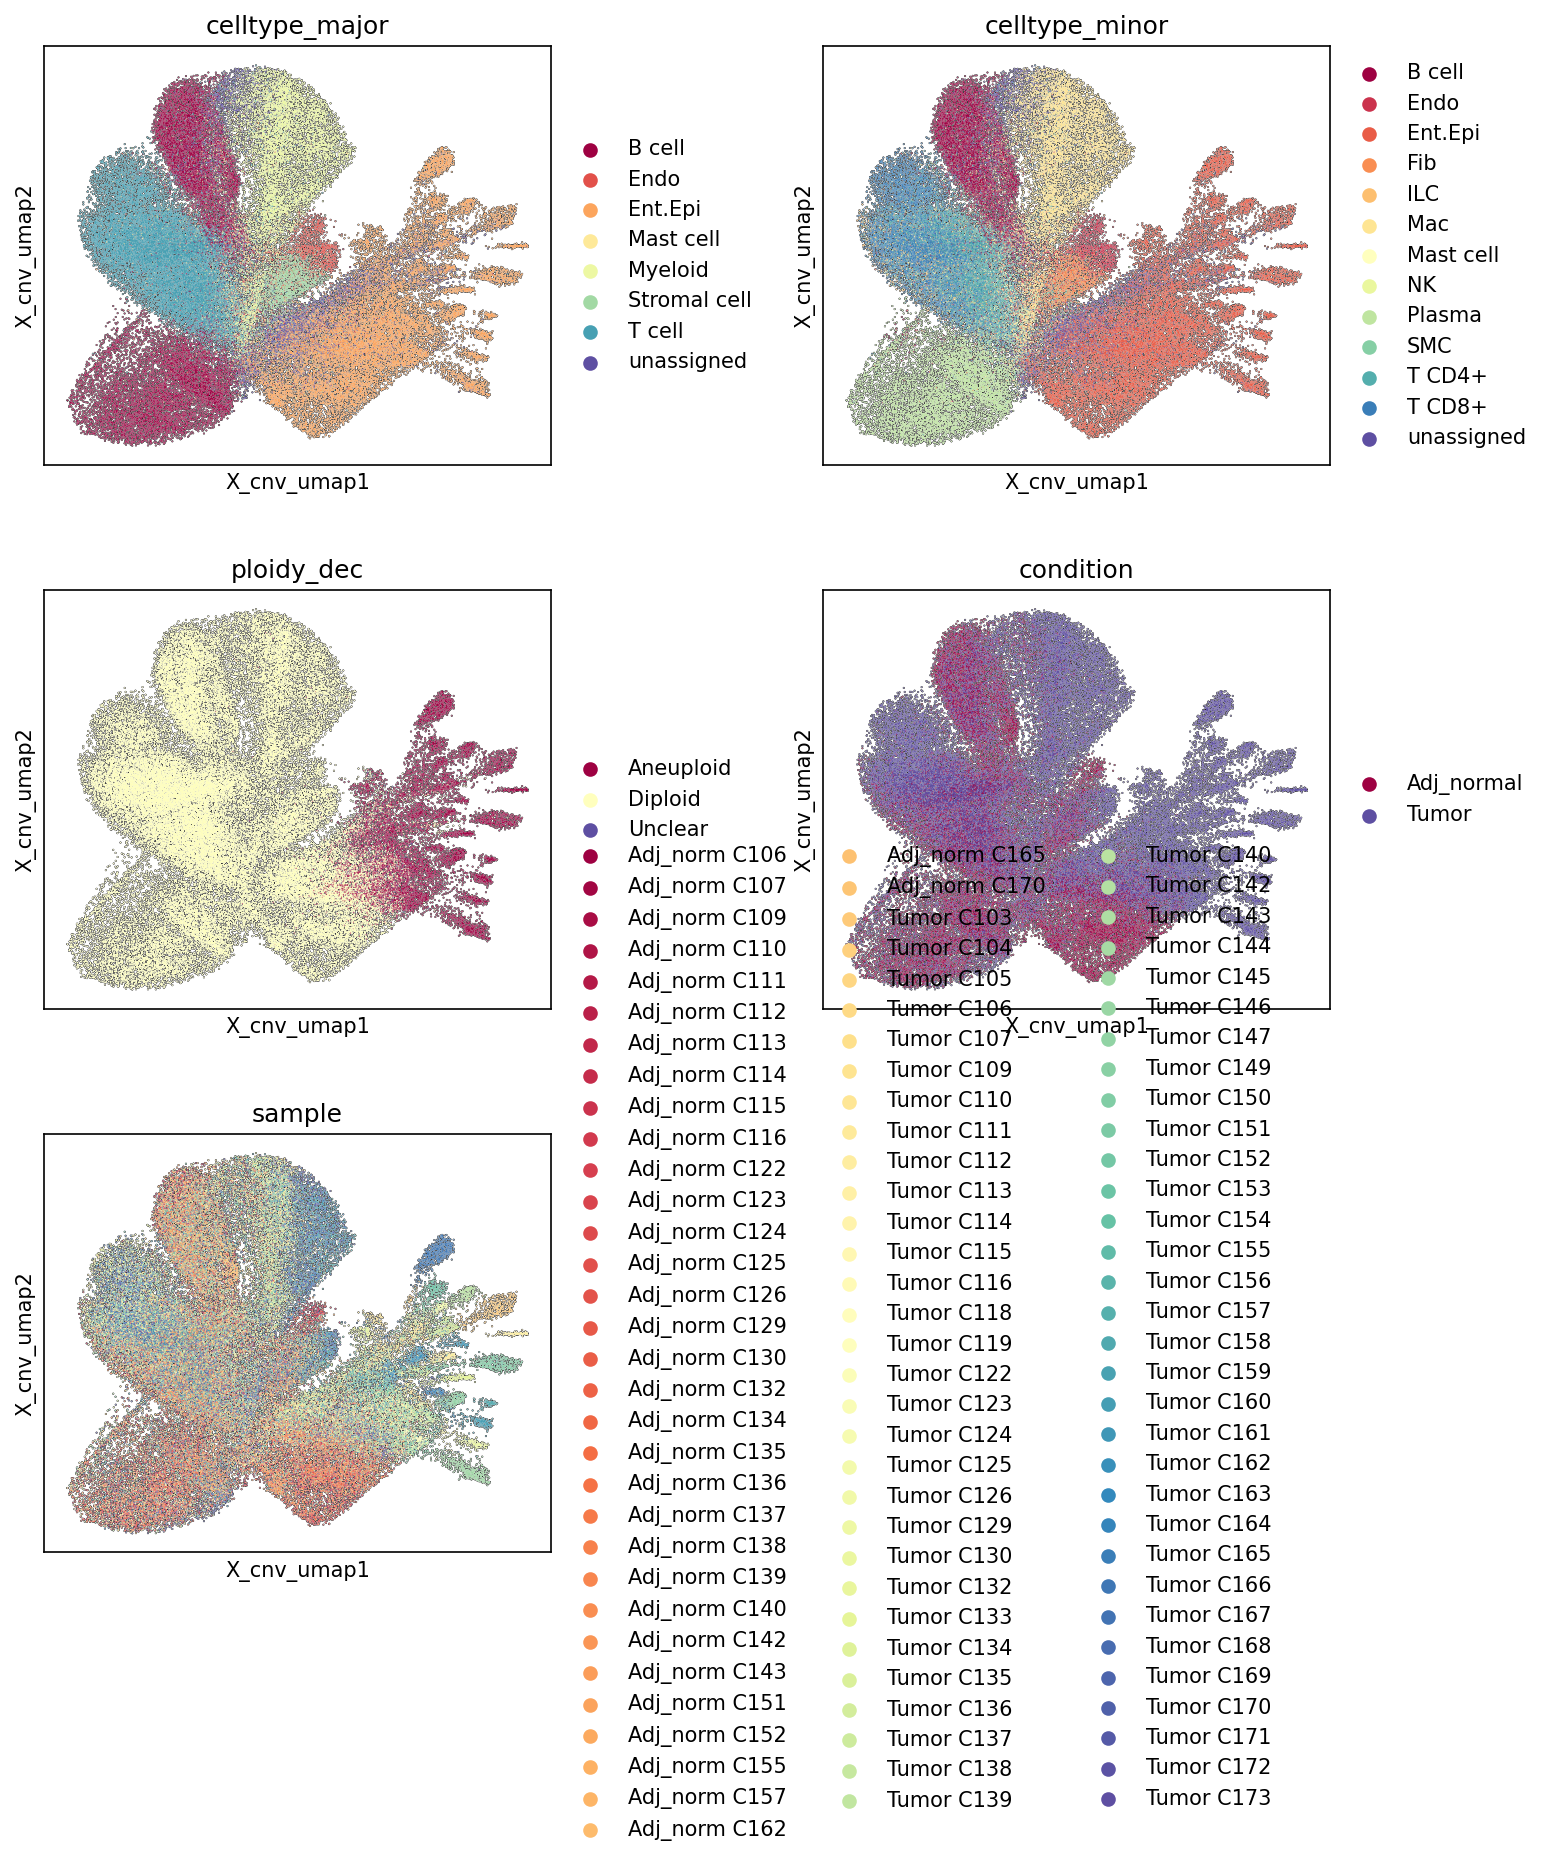
This analysis presents UMAP visualizations of single-cell RNA-seq data, specifically focusing on the embedding space derived from CNV (Copy Number Variation) patterns. The UMAPs are colored by various cellular and sample-level annotations: major cell type, minor cell type, ploidy status, experimental condition (Tumor/Adj_normal), and individual sample IDs. This allows for an assessment of how these annotations stratify cells in a CNV-informed manifold, providing insights into cellular heterogeneity, tumor-specific populations, and potential batch effects within the colorectal cancer dataset.
Visual Summary
The UMAP plots reveal distinct patterns when cells are colored by different attributes:
celltype_major and celltype_minor:
- The UMAPs demonstrate that cells largely cluster by their major and minor cell types, indicating that cell identity is a primary driver of transcriptional and potentially CNV-associated heterogeneity in this dataset.
- Intestinal Epithelial cells (Ent.Epi) form a prominent, largely contiguous cluster, consistent with their role as the primary epithelial component of the colon and the inferred tumor-origin cell type.
- Other immune cell types (e.g., T cell, Myeloid cell, B cell, Plasma cell) and stromal cells (Stromal cell, Fibroblast, Endothelial cell, Smooth muscle cell) also form recognizable clusters, although some show more diffuse distributions or overlap at their boundaries.
- The 'unassigned' cells are sparsely distributed, indicating they do not form a distinct, coherent cluster.
ploidy_dec:
- Diploid cells (light yellow) constitute the vast majority of cells and form the main, centrally located body of the UMAP.
- Aneuploid cells (dark red) are predominantly localized to a distinct, smaller, and more diffuse region, primarily extending from one side of the main Intestinal Epithelial cell cluster. This distinct segregation strongly suggests that aneuploidy defines a specific population of cells with altered genomic profiles.
- The Unclear cells (light purple) are very few and scattered, not forming a significant cluster.
condition:
- Cells from Adj_normal (red) and Tumor (purple) conditions exhibit clear separation. Adj_normal cells largely overlap with the Diploid population, suggesting that healthy tissue primarily consists of diploid cells.
- Tumor cells occupy a much broader region, overlapping significantly with both the Diploid and Aneuploid populations. Crucially, the region dominated by Aneuploid cells is almost exclusively composed of Tumor cells. This confirms the presence of aneuploid cells specifically within the tumor microenvironment.
sample:
- The sample plot, displaying individual patient samples, shows a generally well-mixed pattern within the major cell type clusters, suggesting that batch effects, if present, are not the dominant factor shaping the overall UMAP structure. Cells from different samples are interspersed rather than forming large, distinct sample-specific clusters.
- However, subtle patterns of sample-specific clustering can be observed, particularly in the Aneuploid and Intestinal Epithelial cell-rich regions. This may indicate patient-specific heterogeneity in tumor CNV profiles or cellular composition.
Biological Interpretation
The CNV-informed UMAP analysis effectively disentangles the major sources of cellular variation within this colorectal cancer dataset.
- Cell Type Specificity: The robust clustering of cells by celltype_major and celltype_minor highlights that distinct cell lineages possess unique gene expression and potentially underlying CNV patterns, which dictate their positions in the UMAP space. The Intestinal Epithelial cell population, identified as the Resolved tumor-origin cell type, forms a large, central cluster, providing a clear reference for assessing changes.
- Aneuploidy as a Tumor Hallmark: The stark segregation of Aneuploid cells into a specific, distinct UMAP region strongly supports that these cells represent the malignant population. This finding is consistent with the inferred disease context of colorectal cancer, where aneuploidy is a common characteristic of tumor cells and a key driver of tumor progression and heterogeneity GeneCards: Aneuploidy. The localization of aneuploid cells almost exclusively within the Tumor condition further validates their tumor-specific origin.
- Tumor Microenvironment Complexity: The Tumor condition encompasses both Diploid and Aneuploid cells, reflecting the complex cellular composition of the tumor microenvironment. This includes not only the malignant (aneuploid) epithelial cells but also host stromal and immune cells (often diploid) that infiltrate the tumor. The Adj_normal tissue, as expected, is primarily composed of diploid cells, aligning with healthy tissue characteristics.
- Heterogeneity within Tumor Epithelium: The diffuse nature of the Aneuploid cluster, particularly its branching and spread, might suggest significant CNV heterogeneity among the malignant Intestinal Epithelial cells from different tumor regions or patients. This aligns with the understanding that cancer often exhibits intra-tumor heterogeneity in genomic alterations.
- Batch Effect Assessment: The intermingling of cells from different sample IDs across most cell type clusters indicates that the CNV embedding successfully integrates data from various patients without being overly influenced by strong sample-specific batch effects, at least at the broader cluster level. This enhances confidence in the biological patterns observed.
Annotation Notes
- The visual separation of Aneuploid cells strongly supports the accuracy and biological relevance of the ploidy_dec annotation.
- The clear distinction between Tumor and Adj_normal conditions in the UMAP, particularly with respect to the Aneuploid population, validates the condition labels and their biological significance in the context of cancer.
- The consistent clustering of celltype_major and celltype_minor annotations reinforces the quality of the cell type assignments in this dataset.
- While overall batch effects are not dominant, careful examination of sample-specific patterns within the tumor cell populations might reveal patient-specific CNV profiles or subtle batch effects that warrant further investigation in downstream differential analyses.
6. Minor Cell Type Population Analysis in Colon Adenocarcinoma
[Analysis Visualization Results]...
Analysis Overview
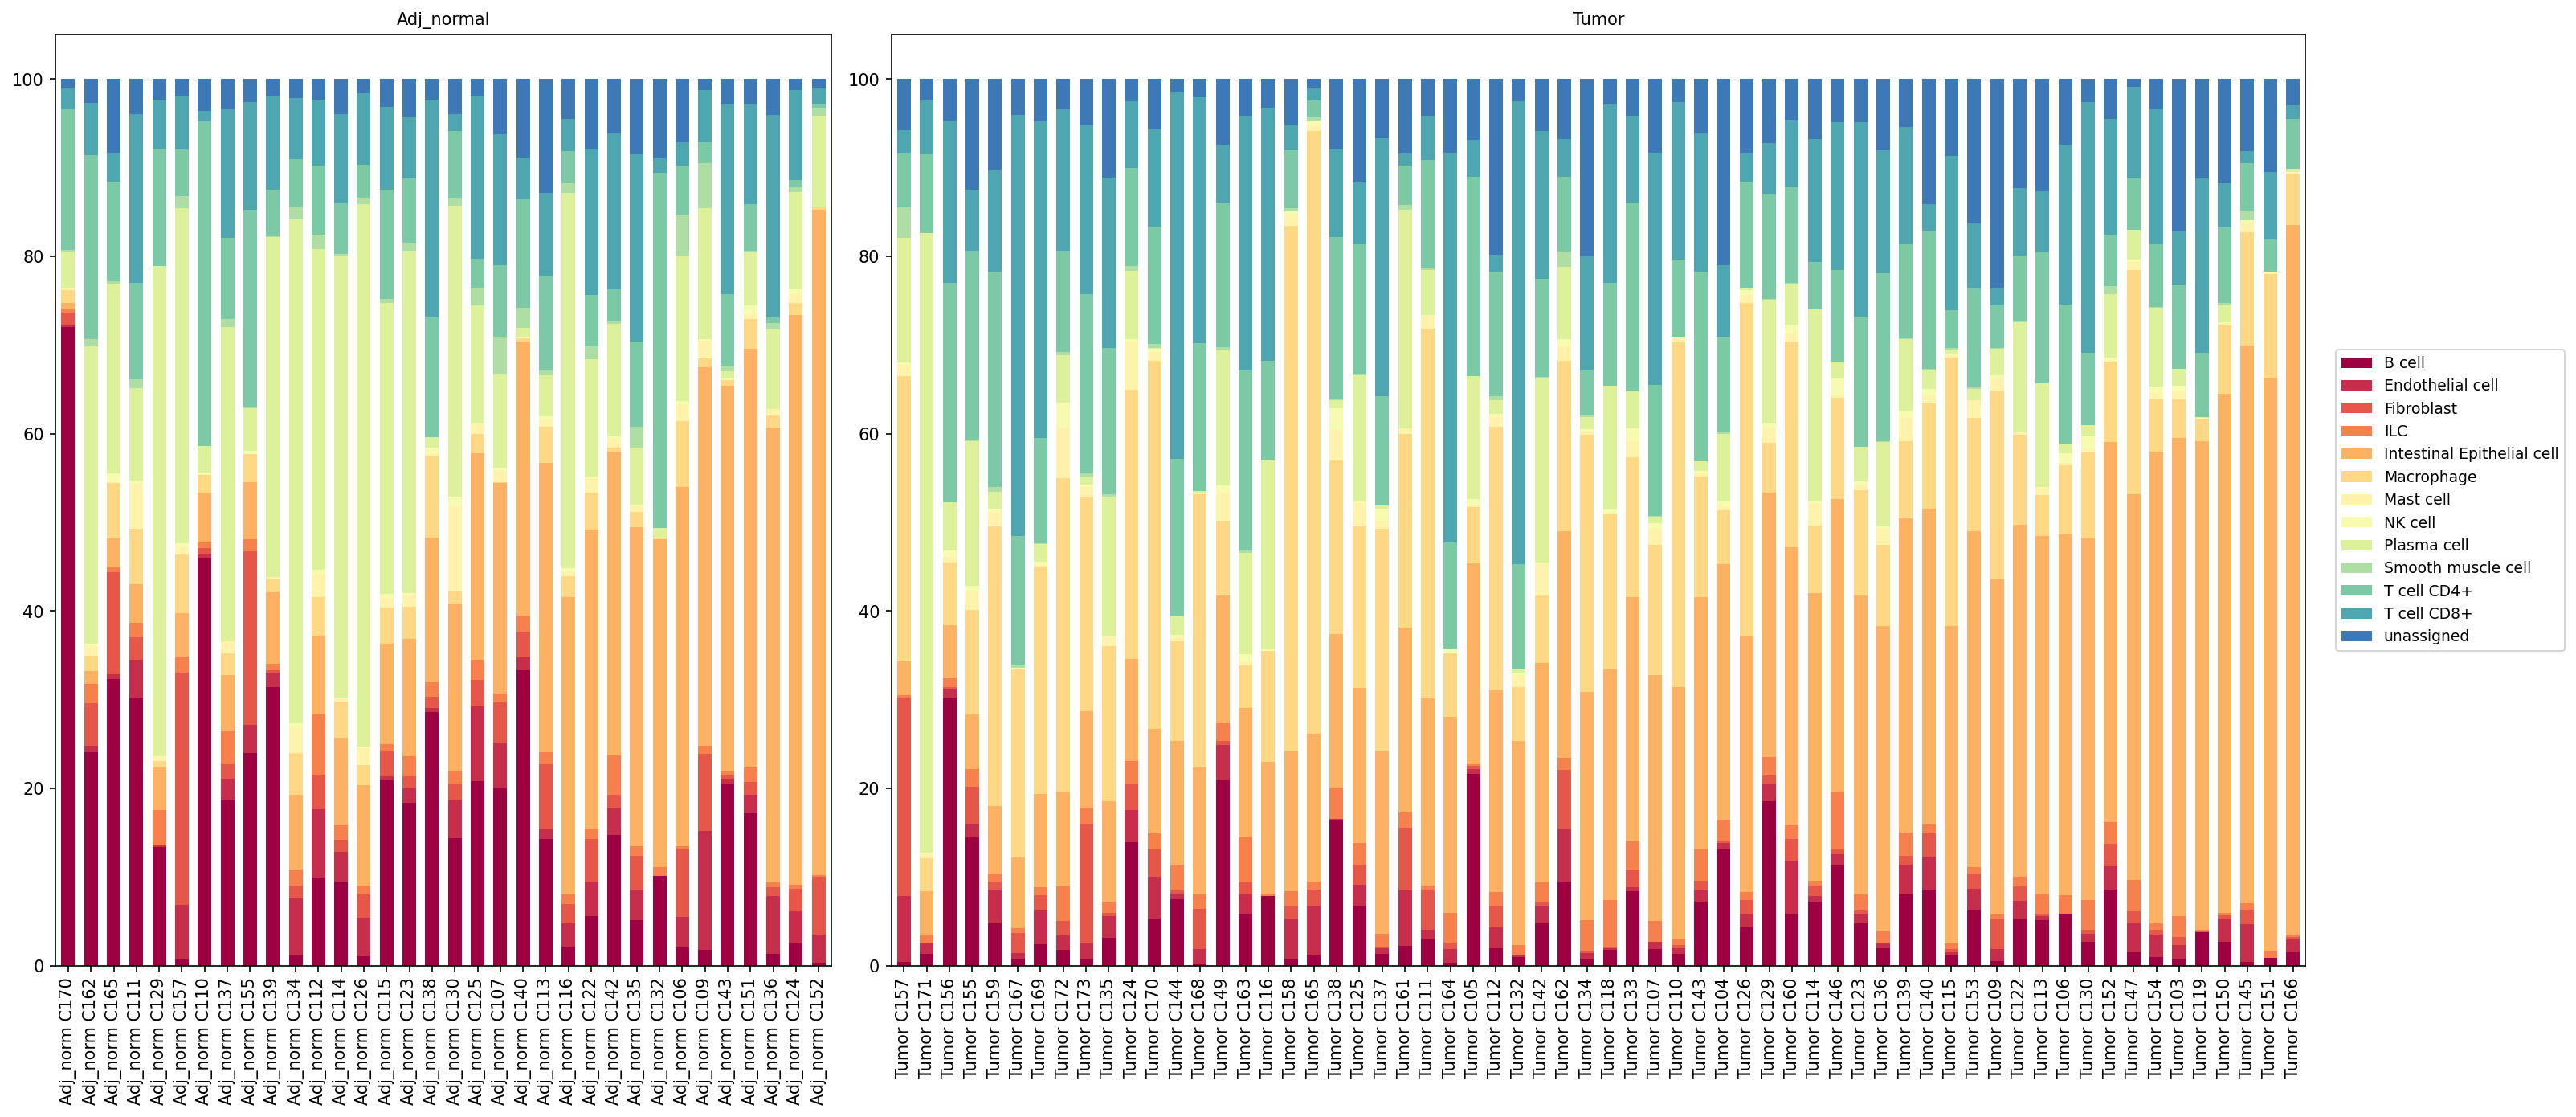
This analysis presents a population bar plot visualizing the relative proportions of different minor cell types across individual samples from both adjacent normal colon tissue and colorectal tumor tissue. The goal is to identify shifts in cellular composition associated with the tumor microenvironment, providing insights into disease-specific cellular dynamics. Each bar represents a single sample, and the stacked segments within each bar correspond to the percentage of each identified celltype_minor.
Visual Summary
The visualization consists of two main panels, one for "Adj_normal" samples and one for "Tumor" samples, with each panel displaying stacked bar plots for individual patients.
- Intestinal Epithelial Cells: Intestinal Epithelial cell (orange/light orange) is a dominant cell type in both adjacent normal and tumor tissues. However, in many tumor samples, its relative proportion appears generally reduced compared to adjacent normal samples. This reduction is not universal across all tumor samples but is a noticeable trend in a significant subset (e.g., Tumor C157, Tumor C171, Tumor C155, Tumor C169).
- Immune Cell Infiltration:
- T cells (CD4+ and CD8+): T cell CD4+ and T cell CD8+ (shades of blue/teal) show a notable increase in their relative proportions within many tumor samples compared to adjacent normal tissue. This suggests enhanced immune cell infiltration in the tumor microenvironment.
- Macrophages: Macrophage populations (light yellow/creamy) also appear more prominent and variable in tumor samples, consistent with the presence of tumor-associated macrophages (TAMs).
- B cells and Plasma Cells: B cell (dark maroon) and Plasma cell (light green/yellow-green) proportions, while present in both conditions, appear to be relatively lower in many tumor samples compared to several adjacent normal samples, which sometimes exhibit substantial B cell populations.
- Other Immune Cells: NK cell, ILC, and Mast cell populations are generally minor components and do not show consistently drastic shifts between conditions, though individual sample variability exists.
- Stromal Cell Dynamics:
- Fibroblasts: Fibroblast (red) proportions show an increase in several tumor samples (e.g., Tumor C157, Tumor C171, Tumor C155, Tumor C169, Tumor C163, Tumor C116, Tumor C125, Tumor C105) compared to adjacent normal tissues, suggesting an expanded stromal component.
- Endothelial Cells: Endothelial cell (dark red) populations are present but do not show a clear, consistent trend of increase or decrease between tumor and normal tissue across all samples.
- Smooth Muscle Cells: Smooth muscle cell (light green-grey) remains a minor component, with no obvious differential pattern.
- Unassigned Cells: The proportion of unassigned cells (dark blue) is consistently low across nearly all samples, indicating high confidence in the cell type assignments.
Biological Interpretation
The observed shifts in minor cell type populations provide crucial biological insights into colorectal cancer progression. The general reduction in Intestinal Epithelial cell proportion in tumor samples, despite being the resolved tumor-origin cell type, likely reflects the expansion and infiltration of non-epithelial cells, particularly immune and stromal cells, within the tumor microenvironment (TME). This "dilution" effect is common as the TME becomes more complex and heterogeneous.
The increased presence of T cell CD4+ and T cell CD8+ in tumors indicates active immune infiltration, which can be either anti-tumorigenic (e.g., cytotoxic CD8+ T cells) or pro-tumorigenic (e.g., regulatory T cells within the CD4+ population or exhausted T cells). The higher Macrophage proportion is consistent with the role of TAMs, which can exert diverse functions, often promoting tumor growth, angiogenesis, and immunosuppression [1]. The potential decrease in B cell and Plasma cell proportions in tumors relative to adjacent normal tissue could suggest altered humoral immunity or compartmentalization effects in the TME.
The increased proportion of Fibroblast cells in tumors strongly suggests the development of cancer-associated fibroblasts (CAFs). CAFs are a critical component of the tumor stroma, known to promote tumor growth, invasion, metastasis, and therapy resistance through extracellular matrix remodeling and secretion of growth factors and cytokines [2]. This desmoplastic reaction is a hallmark of many solid tumors, including colorectal cancer.
Clinical or Translational Implications
These cell population dynamics have significant clinical implications for colorectal cancer:
- Biomarkers and Prognosis: The relative abundance and specific subtypes of immune cells (e.g., CD8+ T cells, TAMs) and stromal cells (e.g., CAFs) can serve as prognostic biomarkers in colorectal cancer. For instance, a higher density of cytotoxic CD8+ T cells is generally associated with better prognosis, while a high density of certain TAM subsets or CAFs can correlate with worse outcomes [3].
- Immunotherapy Response: The observed immune cell infiltration patterns are critical for predicting and monitoring response to immunotherapies. Understanding the balance between anti-tumor (e.g., CD8+ T cells) and pro-tumor/immunosuppressive (e.g., certain macrophage subsets, regulatory T cells, CAFs) cell types is key for developing effective strategies.
- Targeted Therapies: The increased Fibroblast population (CAFs) highlights the tumor stroma as a potential therapeutic target. Strategies aimed at depleting CAFs or modulating their pro-tumor functions are under investigation to enhance drug delivery and efficacy.
- Tumor Heterogeneity: The sample-to-sample variability in cell proportions underscores the high degree of inter-patient and intra-tumor heterogeneity in colorectal cancer, which necessitates personalized treatment approaches.
Overall, this population analysis provides a foundational understanding of the cellular landscape changes in colorectal cancer, pointing towards a complex interplay between tumor cells, immune cells, and stromal cells that drives disease progression and influences therapeutic outcomes.
---
References:
- Locati, M., et al. (2020). Macrophage Polarization and the Tumor Microenvironment. *Annual Review of Pathology: Mechanisms of Disease*, 15, 123-149. PubMed Search: "macrophage polarization tumor microenvironment"
- Öhlund, D., et al. (2017). Cancer-associated fibroblasts for the treatment of cancer. *Journal of Experimental Medicine*, 214(9), 2405-2415. PubMed Search: "cancer-associated fibroblasts colorectal cancer"
- Galon, J., et al. (2012). The Immunoscore: a World Consensus Panel (WCP) for the Classification of Tumors. *Journal of Translational Medicine*, 10(Suppl 1), S1. PubMed Search: "Immunoscore colorectal cancer"
7. T Cell Subset Population Analysis in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
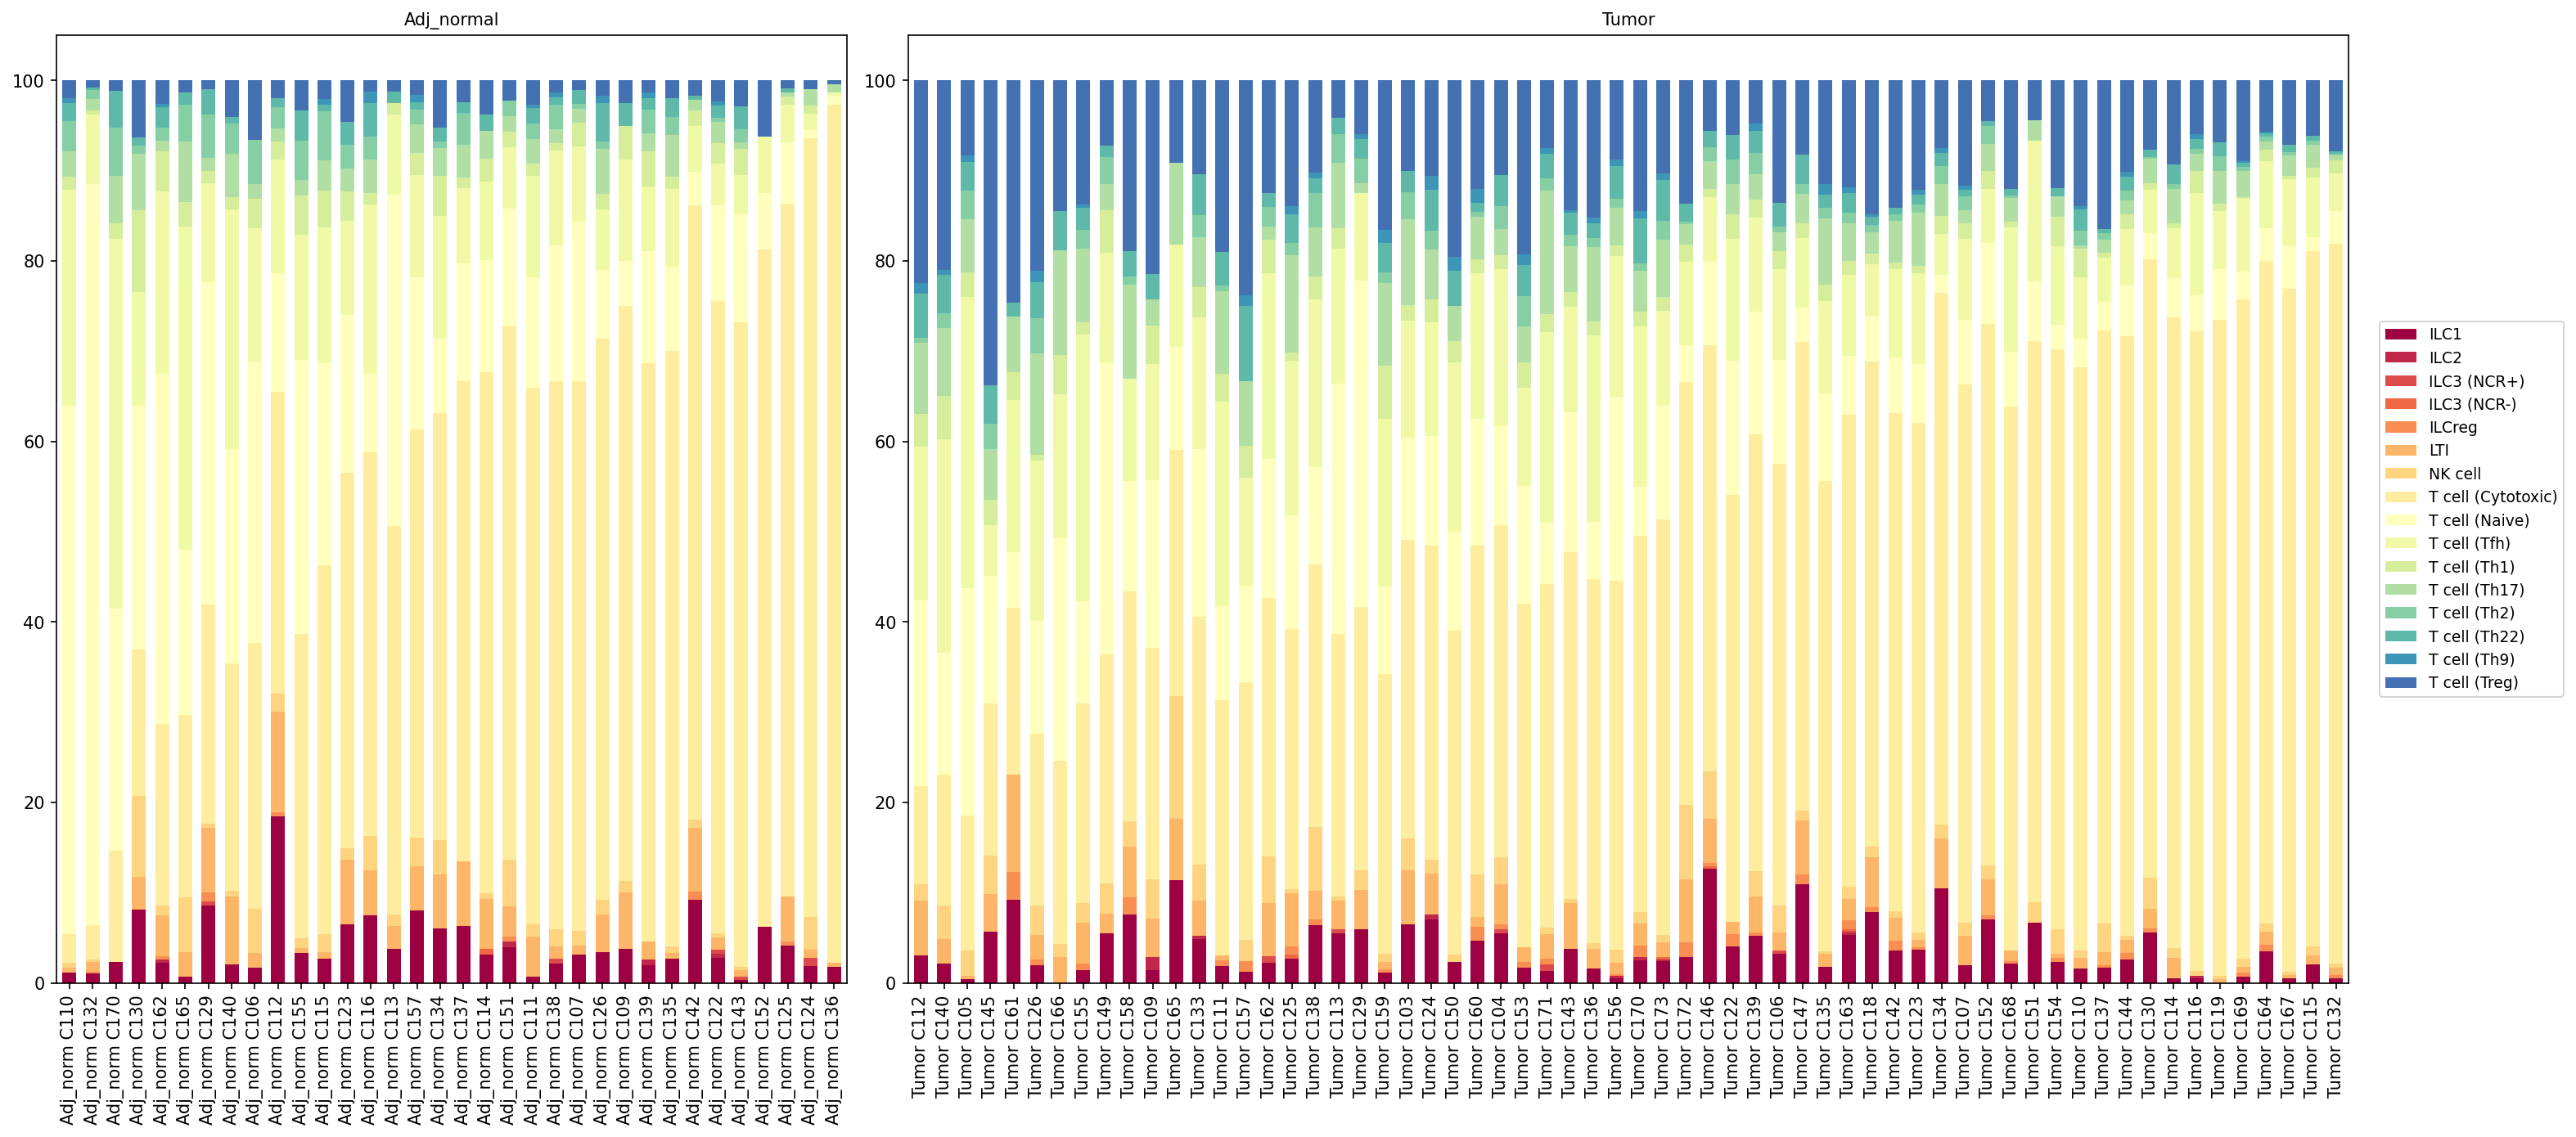
This analysis presents a population bar plot showing the proportional distribution of various T cell subsets, as well as related innate lymphoid cells (ILCs) and NK cells, across individual samples from both Adj_normal (adjacent normal colon tissue) and Tumor (colorectal tumor tissue) conditions. Each bar represents a single sample, and the stacked segments within each bar indicate the relative percentage of each immune cell subset within the broader T cell compartment (as defined by the initial filtering for 'T cell' major cell type). This visualization allows for a granular comparison of immune cell composition shifts associated with colorectal cancer.
Visual Summary
The stacked bar plots display the relative proportions of various T cell subsets and related immune cells (ILCs, NK cells) for each sample, separated by Adj_normal and Tumor conditions.
- Dominant Populations: In both Adj_normal and Tumor samples, T cell (Cytotoxic) (light yellow) and T cell (Naive) (lighter yellow) consistently represent substantial proportions of the overall T cell compartment.
- Innate Lymphoid Cells (ILCs) and NK cells: The populations of ILCs (ILC1, ILC2, ILC3 (NCR+), ILC3 (NCR-), ILCreg, LTI; maroon, red, orange shades) and NK cell (orange) appear to contribute more variably, and often with a relatively higher proportion, in Adj_normal samples compared to Tumor samples. While present in tumors, their relative contribution to the total T cell compartment seems to be less pronounced or highly heterogeneous in many tumor samples.
- T regulatory cells (Tregs): A notable and consistent difference is the apparent enrichment of T cell (Treg) (dark blue) in the Tumor samples. The dark blue band representing Tregs often appears thicker and more prominent at the top of the stack in tumor samples compared to Adj_normal samples.
- Other T Helper Subsets: Other T helper subsets such as T cell (Th1) (light green), T cell (Th17) (medium green), T cell (Th2) (darker green), T cell (Th22) (light blue-green), T cell (Th9) (medium blue-green), and T cell (Tfh) (very light yellow-green) are present across both conditions, but do not show visually striking, consistent shifts as pronounced as the T cell (Treg) population.
Biological Interpretation
The observed shifts in the proportions of T cell subsets and related immune cells between adjacent normal colon tissue and colorectal tumor tissue carry significant biological implications for the tumor microenvironment (TME) and immune evasion mechanisms in colorectal cancer.
- Treg Enrichment in the Tumor Microenvironment: The most striking finding is the increased proportion of T cell (Treg) in Tumor samples. Regulatory T cells are potent immunosuppressive cells that play a critical role in maintaining immune tolerance and preventing autoimmune responses. In the context of cancer, their accumulation and activation within the TME is a well-established mechanism by which tumors evade anti-tumor immunity. Tregs suppress the activity of effector immune cells, including cytotoxic T cells and NK cells, thereby hindering effective anti-tumor responses and promoting tumor growth and progression PubMed search: Tregs colorectal cancer immune evasion.
- Potential Alteration in Innate Lymphoid and NK Cell Contributions: The apparent relative decrease or higher variability of ILCs (ILC1, ILC2, ILC3 (NCR+), ILC3 (NCR-), ILCreg, LTI) and NK cell populations in tumor samples suggests a potential shift in the overall immune landscape. Both ILCs and NK cells are crucial components of the innate immune system involved in direct anti-tumor surveillance and cytokine production. A reduction in their relative proportions within the T cell compartment could indicate either their physical displacement by other cell types or their functional impairment/exhaustion in the immunosuppressive TME, potentially compromising innate anti-tumor defenses PubMed search: ILCs NK cells cancer immunity.
- Balance of Effector T Cells: While T cell (Cytotoxic) populations remain abundant in tumor samples, their functional efficacy may be compromised by the elevated presence of Tregs. An immunosuppressive TME, dominated by Tregs, can induce an exhausted phenotype in cytotoxic T cells, diminishing their ability to recognize and kill tumor cells, even if their numbers are maintained. The overall balance between pro-inflammatory (e.g., Th1) and immunosuppressive (e.g., Tregs) T cell subsets dictates the nature of the anti-tumor immune response.
Clinical or Translational Implications
The findings from this T cell subset analysis have several important clinical and translational implications in the context of colorectal cancer:
- Prognostic Biomarker: High infiltration of Tregs in colorectal cancer is frequently associated with poor prognosis, more aggressive disease, and reduced patient survival GeneCards: FOXP3 biomarker. The observed enrichment of Tregs in Tumor samples supports their potential role as a prognostic biomarker for colorectal cancer.
- Therapeutic Target for Immunotherapy: The prominent role of Tregs in immune suppression within the TME makes them attractive targets for novel immunotherapeutic strategies. Approaches aimed at depleting Tregs, inhibiting their suppressive function, or converting them into effector T cells could enhance anti-tumor immunity and improve patient response to existing treatments, such as immune checkpoint inhibitors PubMed search: Treg targeting cancer therapy.
- Patient Stratification and Personalized Medicine: Detailed immune profiling, such as this T cell subset analysis, is crucial for stratifying patients who might benefit most from specific immunotherapies. Patients with a high Treg-to-effector T cell ratio might require combination therapies that not only activate effector cells but also mitigate Treg-mediated suppression. This contributes to the development of personalized treatment strategies in colorectal cancer.
- Understanding Immune Evasion Mechanisms: This analysis provides insights into one of the key immune evasion mechanisms employed by colorectal tumors – the establishment of an immunosuppressive microenvironment facilitated by Tregs. A comprehensive understanding of these mechanisms is fundamental for developing more effective therapies.
8. Analysis of T Cell Subset Proportions in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
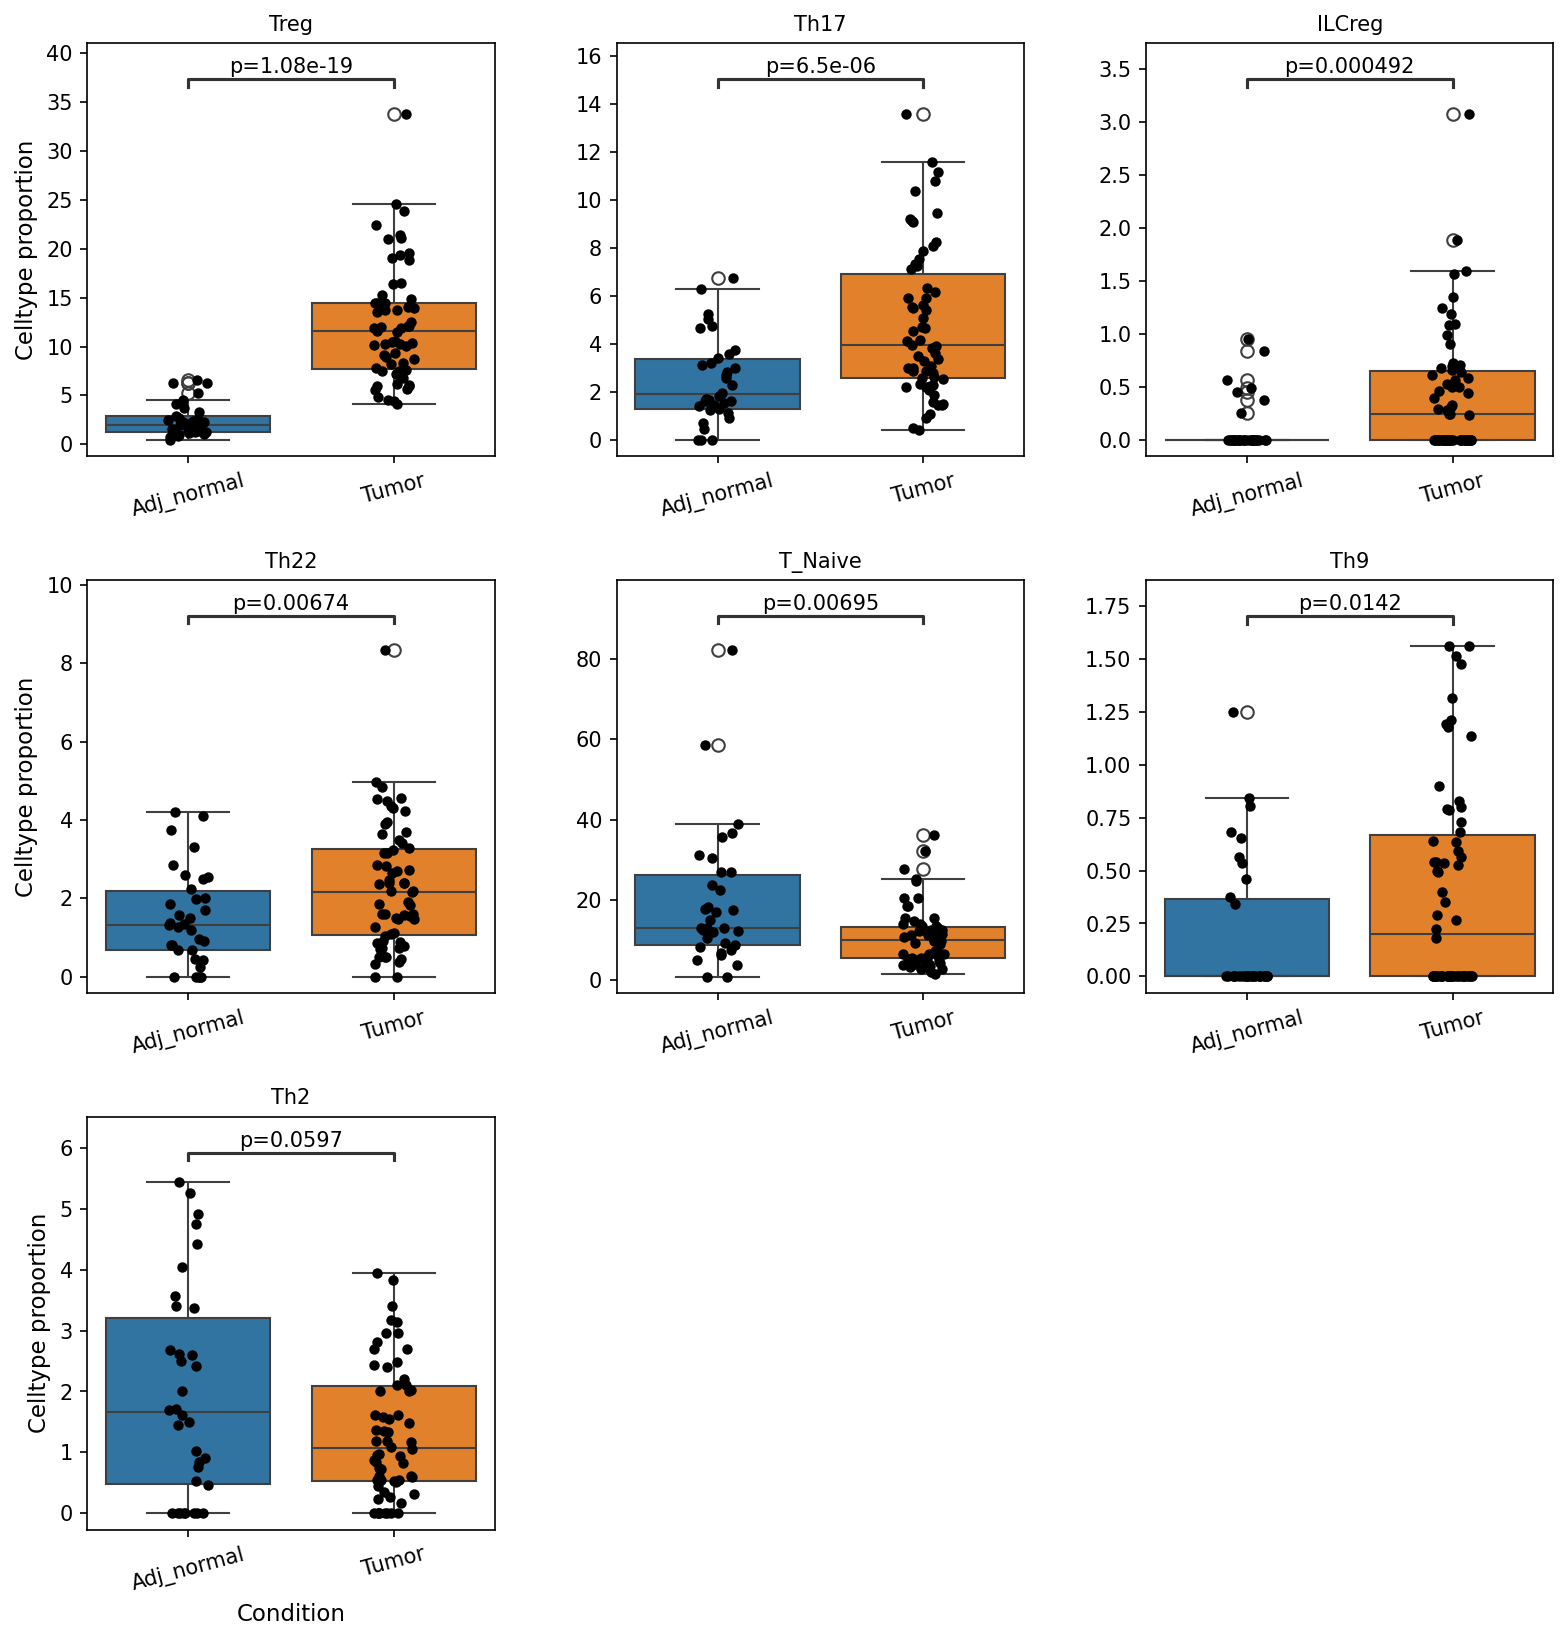
This analysis investigates the proportions of various T cell subsets in the context of colorectal cancer by comparing 'Tumor' tissue with 'Adj_normal' (adjacent normal) tissue samples. The box plots display the distribution of cell type proportions for each subset across samples, with individual data points overlaid as stripplots. Statistical significance (p-values) indicates subsets with notable differences between the two conditions. The analysis specifically focused on T cell subsets as defined by the celltype_subset annotation.
Visual Summary
The visualization presents seven box plots, each representing a distinct T cell subset identified with a statistically significant difference (p < 0.1) between 'Adj_normal' and 'Tumor' conditions.
- Treg (Regulatory T cells): A highly significant increase in proportion is observed in Tumor tissue (median ~12%) compared to Adj_normal tissue (median ~2%) (p=1.08e-19). The distribution in tumor tissue is also wider, indicating more variability.
- Th17 (T helper 17 cells): The proportion of Th17 cells is significantly elevated in Tumor tissue (median ~4%) compared to Adj_normal tissue (median ~2%) (p=6.5e-06).
- ILCreg (Regulatory Innate Lymphoid Cells): A significant increase in ILCreg proportion is noted in Tumor tissue (median ~0.2-0.3%) relative to Adj_normal tissue (median close to 0%) (p=0.000492), suggesting their recruitment or expansion in the tumor microenvironment.
- Th22 (T helper 22 cells): Th22 cell proportions are significantly higher in Tumor tissue (median ~2.5%) compared to Adj_normal tissue (median ~1.5%) (p=0.00674).
- T_Naive (Naive T cells): In contrast to the aforementioned subsets, T_Naive cells show a significant decrease in Tumor tissue (median ~10%) compared to Adj_normal tissue (median ~15%) (p=0.00695). This suggests a depletion or differentiation of naive T cells within the tumor microenvironment.
- Th9 (T helper 9 cells): A significant increase in Th9 cell proportion is observed in Tumor tissue (median ~0.2%) compared to Adj_normal tissue (median ~0.1%) (p=0.0142).
- Th2 (T helper 2 cells): Th2 cell proportions are significantly decreased in Tumor tissue (median ~1.0%) relative to Adj_normal tissue (median ~1.5%) (p=0.0597), albeit with a p-value closer to the cutoff, indicating a weaker but still significant difference.
Overall, there is a prominent trend of increased proportions for several regulatory and inflammatory T cell subsets (Treg, Th17, ILCreg, Th22, Th9) and a decrease in naive and Th2 T cell populations within the colorectal tumor microenvironment.
Biological Interpretation
The observed shifts in T cell subset proportions between 'Adj_normal' and 'Tumor' tissues provide critical insights into the immune landscape of colorectal cancer.
Increased Immunosuppressive and Inflammatory Populations:
- The striking increase in Treg cells in tumor tissue is a well-documented phenomenon in many cancers, including colorectal cancer. Tregs suppress anti-tumor immune responses, facilitating immune evasion and tumor progression. Their high abundance is often associated with poor prognosis. https://pubmed.ncbi.nlm.nih.gov/33946059/
- Th17 cells, while having context-dependent roles, are often associated with chronic inflammation and can promote tumor growth in colorectal cancer by contributing to angiogenesis and maintaining an immunosuppressive environment. https://pubmed.ncbi.nlm.nih.gov/37620245/
- The increase in Th22 and Th9 cells also points towards a complex inflammatory microenvironment. Th22 cells, by producing IL-22, can promote epithelial cell proliferation and survival, potentially contributing to tumor growth. https://pubmed.ncbi.nlm.nih.gov/34305881/ Th9 cells have a more controversial role, but an increase could indicate certain pro-tumorigenic inflammatory pathways. https://pubmed.ncbi.nlm.nih.gov/35791786/
- The significant increase in ILCreg cells, while less studied than Tregs, further suggests an enhanced regulatory and potentially immunosuppressive innate immune component within the tumor microenvironment. https://pubmed.ncbi.nlm.nih.gov/34267440/
Decreased Naive and Th2 Populations:
- The decrease in T_Naive cells is expected in a tumor environment, as naive T cells differentiate into various effector or regulatory subsets upon antigen encounter. This reduction might reflect extensive immune cell activation and differentiation within the tumor, or a failure of new naive cells to infiltrate or persist.
- The decrease in Th2 cells is interesting. While Th2 responses are generally considered pro-tumorigenic in some contexts by suppressing Th1-mediated anti-tumor immunity, their reduction here could suggest a dominant role of other suppressive mechanisms (e.g., Tregs) or a shift away from a Th2-biased suppressive environment towards other forms of immune evasion. https://pubmed.ncbi.nlm.nih.gov/35650193/
In summary, the colorectal tumor microenvironment appears to be characterized by an enrichment of diverse immunosuppressive (Treg, ILCreg) and inflammatory (Th17, Th22, Th9) T cell subsets, alongside a depletion of naive T cells. This immunological profile is highly conducive to immune evasion and tumor progression.
Clinical or Translational Implications
These findings have several potential clinical and translational implications for colorectal cancer:
- Prognostic Biomarkers: The altered proportions of specific T cell subsets, particularly the elevated Tregs and Th17 cells, could serve as prognostic biomarkers. High Treg infiltration, for example, is often correlated with worse patient outcomes in colorectal cancer.
- Therapeutic Targets: The enrichment of immunosuppressive cells (Tregs, ILCreg) highlights these populations as potential therapeutic targets for immune modulation. Strategies aimed at depleting or reprogramming Tregs could enhance anti-tumor immunity. Similarly, modulating the pro-tumorigenic aspects of Th17, Th22, and Th9 cells might offer new therapeutic avenues.
- Response to Immunotherapy: The observed immune landscape could influence the response to existing immunotherapies, such as checkpoint inhibitors. A highly immunosuppressive microenvironment with abundant Tregs might limit the efficacy of therapies designed to unleash effector T cells. Understanding these cell shifts could help stratify patients for immunotherapy or guide combination therapies.
- Disease Monitoring: Changes in these T cell subset proportions might be monitored as indicators of disease progression or response to treatment, potentially through liquid biopsies or tissue analysis.
9. Macrophage Subset Population Analysis in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
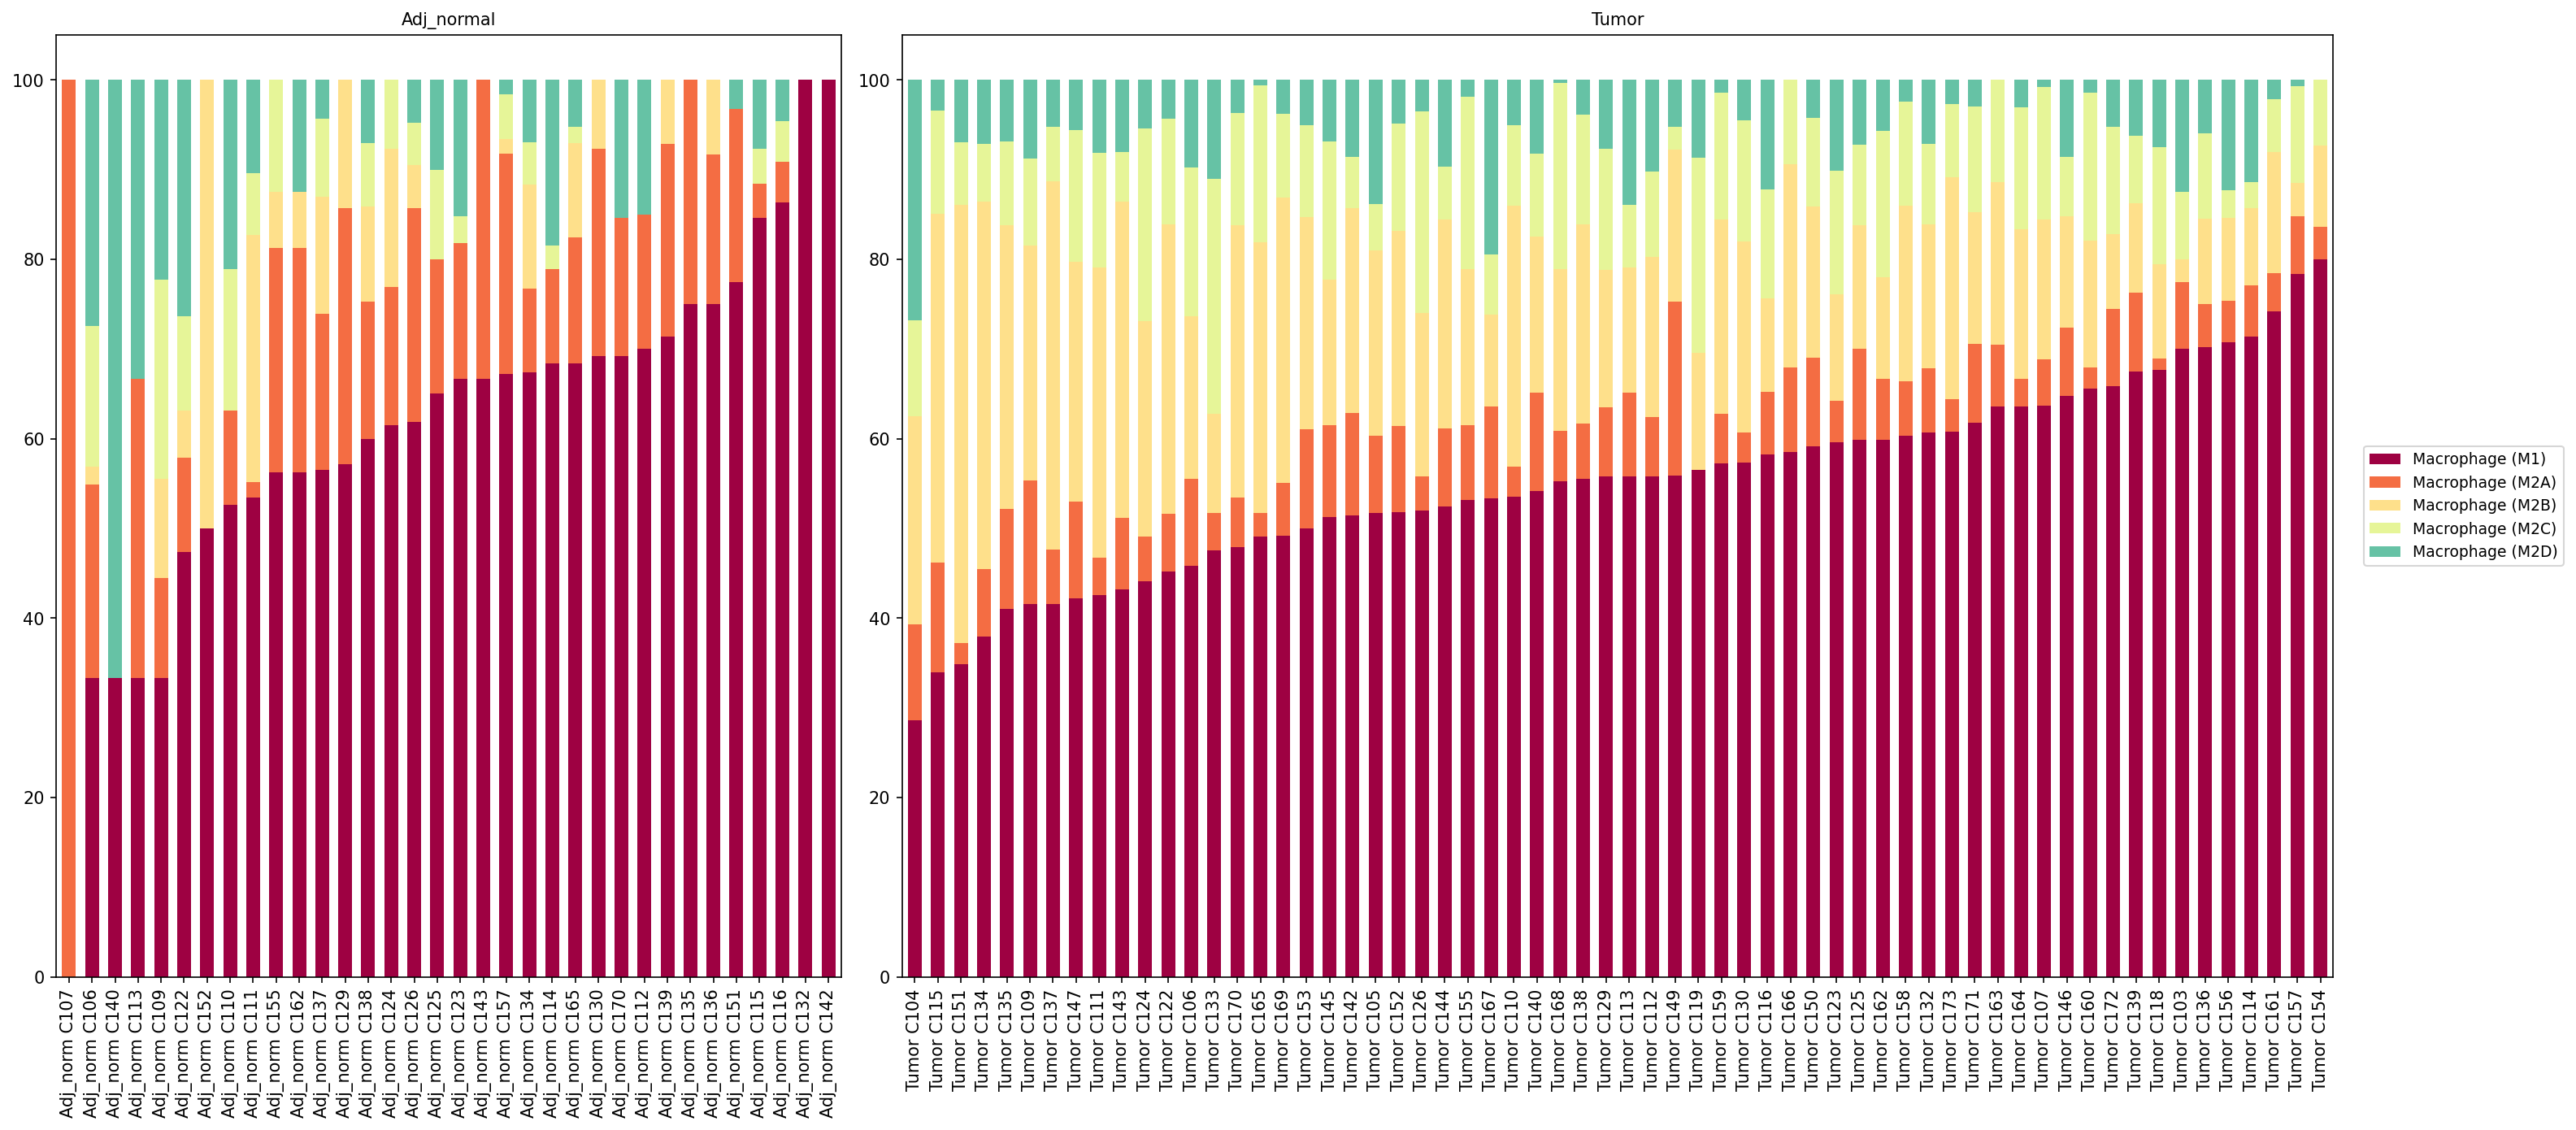
This analysis presents a population bar plot illustrating the relative proportions of different macrophage subsets (Macrophage M1, M2A, M2B, M2C, M2D) across individual samples derived from human Colon tissue. The data is stratified by condition into "Adj_normal" (adjacent normal tissue) and "Tumor" samples. Each bar on the plot represents a single sample, and the stacked colored segments within each bar denote the percentage contribution of each specific macrophage subset to the total macrophage population in that sample. This visualization is crucial for understanding potential shifts in macrophage polarization within the colorectal tumor microenvironment compared to the healthy or non-malignant tissue context.
Visual Summary
The visualization consists of two main panels, one for "Adj_normal" samples and one for "Tumor" samples, both depicting the proportional distribution of macrophage subsets.
In the "Adj_normal" tissue samples, the macrophage population displays a more varied composition. Macrophage (M1) (maroon) generally constitutes a substantial portion, often representing between 30% and 70% of the total macrophage population in many samples. Macrophage (M2A) (orange) is also distinctly present, contributing a notable, albeit variable, fraction. The other M2 subtypes—Macrophage (M2B) (pale yellow), Macrophage (M2C) (light green), and Macrophage (M2D) (teal)—are present but typically in smaller and more fluctuating proportions across different normal samples.
In stark contrast, the "Tumor" tissue samples exhibit a pronounced and consistent shift in macrophage composition. There is a clear reduction in the relative proportion of Macrophage (M1) (maroon) in the majority of tumor samples, frequently falling below 20-30% of the total macrophage pool. Concurrently, the M2-like macrophage subtypes collectively become dominant. Most notably, Macrophage (M2B) (pale yellow) shows a substantial increase in its relative abundance across many tumor samples, often becoming a major component of the macrophage population. Macrophage (M2A) (orange) also appears to maintain a significant presence in some tumor samples. Macrophage (M2C) (light green) and Macrophage (M2D) (teal) also contribute to the overall M2 dominance, with M2B showing the most prominent relative expansion. This pattern strongly indicates a widespread polarization towards an M2-like phenotype within the tumor microenvironment.
Biological Interpretation
The observed shift from a macrophage population with a relatively higher proportion of M1 macrophages and more balanced M2 subtypes in adjacent normal colon tissue, to a strong dominance of M2-like macrophages (particularly M2B) and a diminished proportion of M1 macrophages in colorectal tumor samples, holds significant implications for cancer biology.
- Macrophage Polarization: M1 macrophages are typically characterized by pro-inflammatory, anti-tumor functions, including antigen presentation and direct tumoricidal activity. In contrast, M2 macrophages are generally associated with anti-inflammatory responses, tissue repair, angiogenesis, immune suppression, and ultimately, promotion of tumor growth and metastasis. The specific M2 subtypes (M2A, M2B, M2C, M2D) represent distinct functional states within the M2 spectrum, each induced by different signals and contributing uniquely to the microenvironment.
- Tumor-Associated Macrophages (TAMs): In the context of cancer, macrophages that infiltrate the tumor are often termed Tumor-Associated Macrophages (TAMs). These TAMs are frequently skewed towards an M2-like phenotype, fostering an immunosuppressive and pro-tumorigenic microenvironment. The significant increase in M2B macrophages in tumor samples strongly suggests that these TAMs in colorectal cancer are largely polarized towards an M2B-like state.
- Role of M2B Macrophages in Cancer: M2B macrophages are known to be induced by immune complexes and TLR agonists, producing a mix of both pro-inflammatory (e.g., IL-6, TNFα) and anti-inflammatory cytokines (e.g., IL-10, TGF-β). In the tumor microenvironment, while they can initiate some inflammatory responses, their overall dominance alongside a reduction in M1 cells often points to a net immunosuppressive effect that supports tumor progression, neoangiogenesis, and metastasis.
Clinical or Translational Implications
The marked shift towards M2-like macrophage subsets, especially the prominent increase in M2B macrophages, within colorectal tumor tissue compared to normal tissue has several important clinical and translational implications:
- Prognostic Biomarker: An elevated proportion of M2-like macrophages, or specifically M2B macrophages, within the colorectal tumor microenvironment may serve as a prognostic indicator, potentially correlating with disease progression, metastasis, or poorer patient outcomes in colorectal cancer PubMed search: M2 macrophage colorectal cancer prognosis.
- Therapeutic Targeting: Given the pro-tumor functions of M2-like macrophages, strategies aimed at modulating macrophage polarization could represent novel therapeutic avenues. This includes approaches to repolarize pro-tumor M2 macrophages to an anti-tumor M1 phenotype, or to inhibit the differentiation and functions of M2 macrophages. Targeting specific M2 subtypes, such as M2B, might offer a more precise immunotherapeutic strategy for colorectal cancer PubMed search: macrophage polarization cancer therapy.
- Immunosuppressive Microenvironment: The dominance of M2-like macrophages signifies a highly immunosuppressive tumor microenvironment, which can potentially limit the effectiveness of existing immunotherapies, such as immune checkpoint inhibitors. Understanding the specific M2 subtypes driving this immunosuppression can inform the development of rational combination therapies designed to overcome resistance.
- Response to Therapy: Monitoring changes in the proportions of macrophage subsets during treatment could serve as a biomarker to assess therapeutic response or to predict resistance to immunomodulatory drugs.
This analysis underscores the critical role of macrophage plasticity in the pathogenesis of colorectal cancer and highlights the potential for therapeutically manipulating specific macrophage polarization states.
10. Macrophage Subset Population Shifts in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
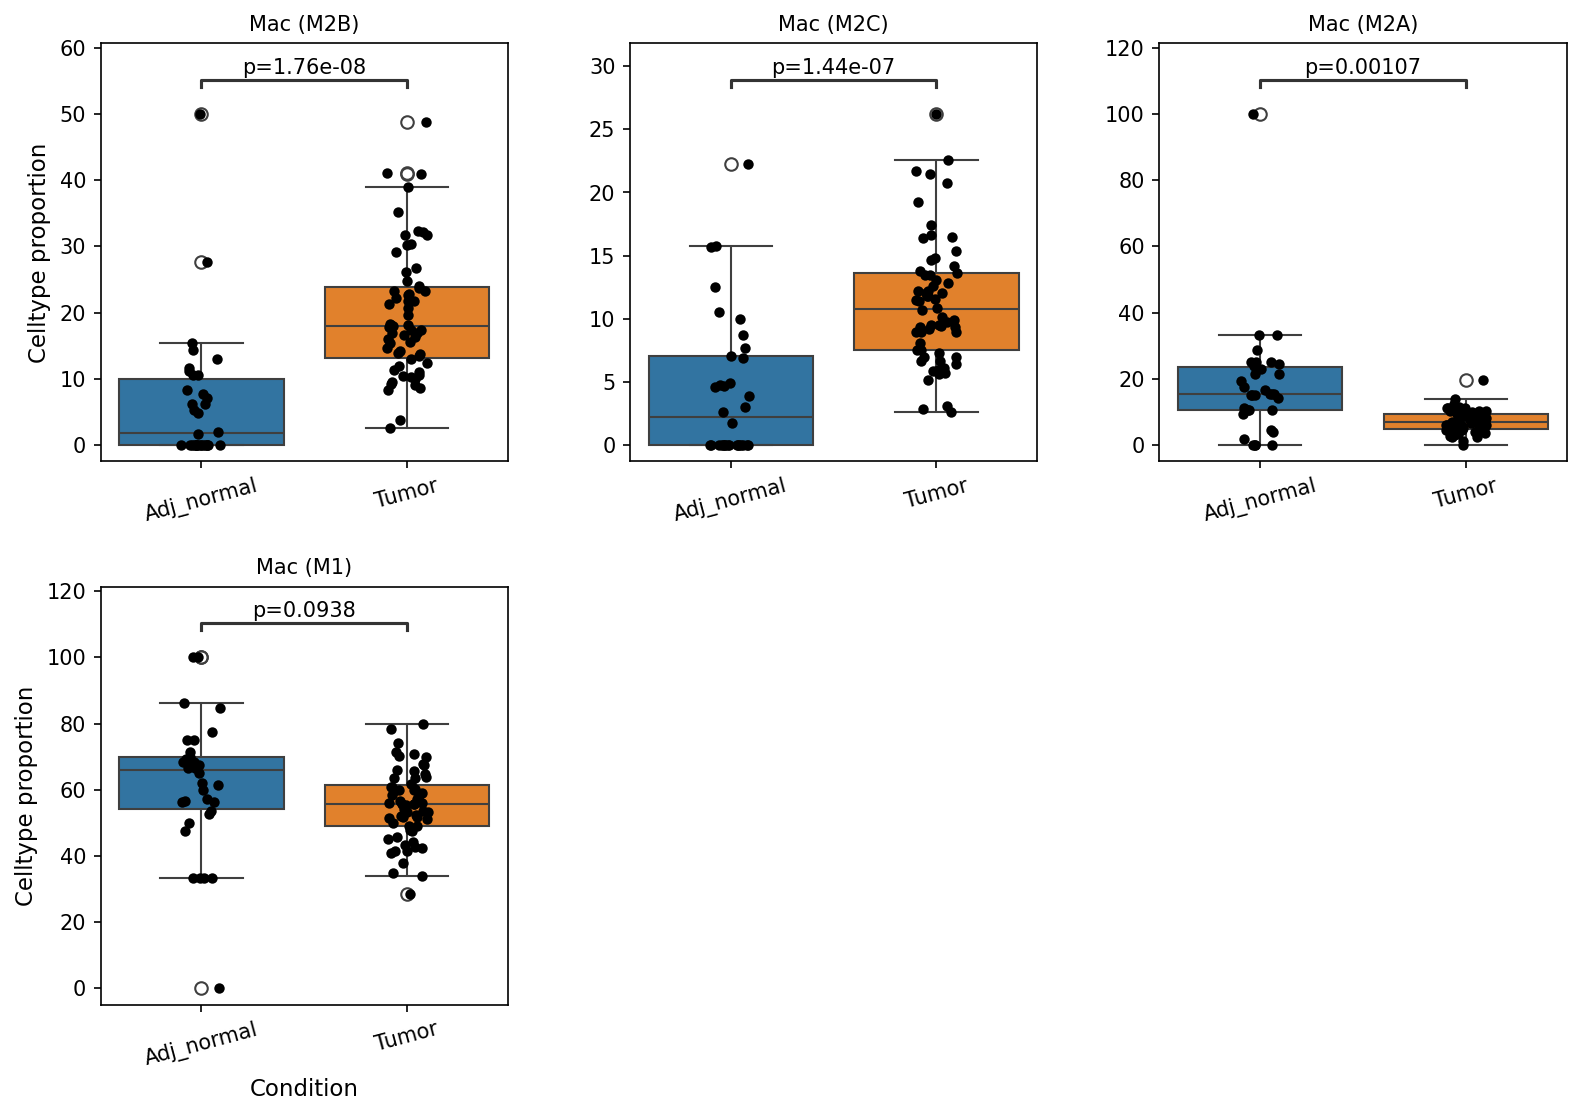
This analysis investigates the proportional representation of different macrophage subsets within colorectal cancer tissues compared to adjacent normal colon tissues. Specifically, it examines the relative abundance of Mac (M1), Mac (M2A), Mac (M2B), and Mac (M2C) populations, which are minor cell types derived from the broader 'Macrophage' category. Box plots are generated to visualize these proportions across 'Adj_normal' and 'Tumor' conditions, with statistical significance testing performed to identify subsets showing differential prevalence. A p-value cutoff of 0.1 was applied for significance.
Visual Summary
The box plots illustrate clear and statistically significant shifts in the proportions of several macrophage subsets between adjacent normal and tumor tissues in the colon:
Mac (M2B) and Mac (M2C) Enrichment in Tumors:
- The proportion of Mac (M2B) cells is significantly higher in Tumor samples compared to Adj_normal samples (p=1.76e-08). The median proportion in tumors is roughly two to three times greater than in normal tissue.
- Similarly, Mac (M2C) cell proportion is significantly elevated in Tumor samples (p=1.44e-07), showing a median proportion approximately double that observed in adjacent normal tissue.
Mac (M2A) Reduction in Tumors:
- In contrast, the proportion of Mac (M2A) cells is significantly lower in Tumor tissue compared to Adj_normal tissue (p=0.00107). The median proportion of Mac (M2A) in tumors is substantially reduced, indicating a depletion of this specific M2 subtype in the tumor microenvironment.
Mac (M1) Trend in Tumors:
- The proportion of Mac (M1) cells shows a trend towards reduction in Tumor samples compared to Adj_normal, with marginal statistical significance (p=0.0938). While the difference is less pronounced than for the other subsets, the median proportion appears slightly lower in tumor tissue.
Biological Interpretation
Macrophages are highly plastic immune cells that polarize into different functional states, traditionally categorized as M1 (pro-inflammatory, anti-tumor) and M2 (anti-inflammatory, pro-tumor) phenotypes, with further diverse subsets within these categories (e.g., M2A, M2B, M2C).
The observed findings reveal a substantial remodeling of the macrophage landscape in colorectal cancer. The significant increase in Mac (M2B) and Mac (M2C) populations within tumor tissues is highly indicative of a shift towards a pro-tumorigenic microenvironment. M2-polarized macrophages, often referred to as Tumor-Associated Macrophages (TAMs), are known to promote tumor growth, angiogenesis, metastasis, and immune evasion through various mechanisms including secretion of growth factors, cytokines, and matrix remodeling enzymes [NCBI]. The specific enrichment of M2B and M2C subsets suggests that these particular subtypes play a prominent role in supporting colorectal cancer progression.
Conversely, the decrease in Mac (M2A) and the trend of reduction in Mac (M1) populations suggest a suppression of specific anti-tumorigenic or less pro-tumorigenic macrophage phenotypes within the tumor microenvironment. While M2A macrophages are generally considered anti-inflammatory, their specific roles can vary, and their reduction might indicate that the dominant M2 phenotype in colorectal cancer is driven by M2B and M2C cells. The subtle decrease in M1 macrophages further supports the idea of an immunosuppressive tumor microenvironment, as M1 cells are crucial for initiating effective anti-tumor immune responses.
This overall pattern highlights how colorectal tumors actively recruit and polarize macrophages to foster an environment conducive to their growth and survival.
Clinical or Translational Implications
The distinct and statistically significant shifts in macrophage subset proportions between normal and tumor tissues have important clinical and translational implications for colorectal cancer:
- Therapeutic Targeting: The enrichment of Mac (M2B) and Mac (M2C) populations suggests these specific macrophage subsets could be attractive therapeutic targets. Strategies aimed at depleting these cells, reprogramming them towards an M1-like phenotype, or inhibiting their pro-tumorigenic functions may represent novel immunotherapeutic approaches for colorectal cancer.
- Prognostic and Predictive Biomarkers: The proportional representation of these macrophage subsets, particularly the elevated M2B and M2C populations, could potentially serve as prognostic biomarkers for disease progression or indicators of response to existing or developing immunotherapies in colorectal cancer patients.
- Understanding Tumor Microenvironment: A deeper understanding of the specific molecular pathways and stimuli that drive the polarization of macrophages towards M2B and M2C phenotypes in colorectal cancer is crucial for developing targeted interventions.
11. Ploidy Status of Intestinal Epithelial Cells in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
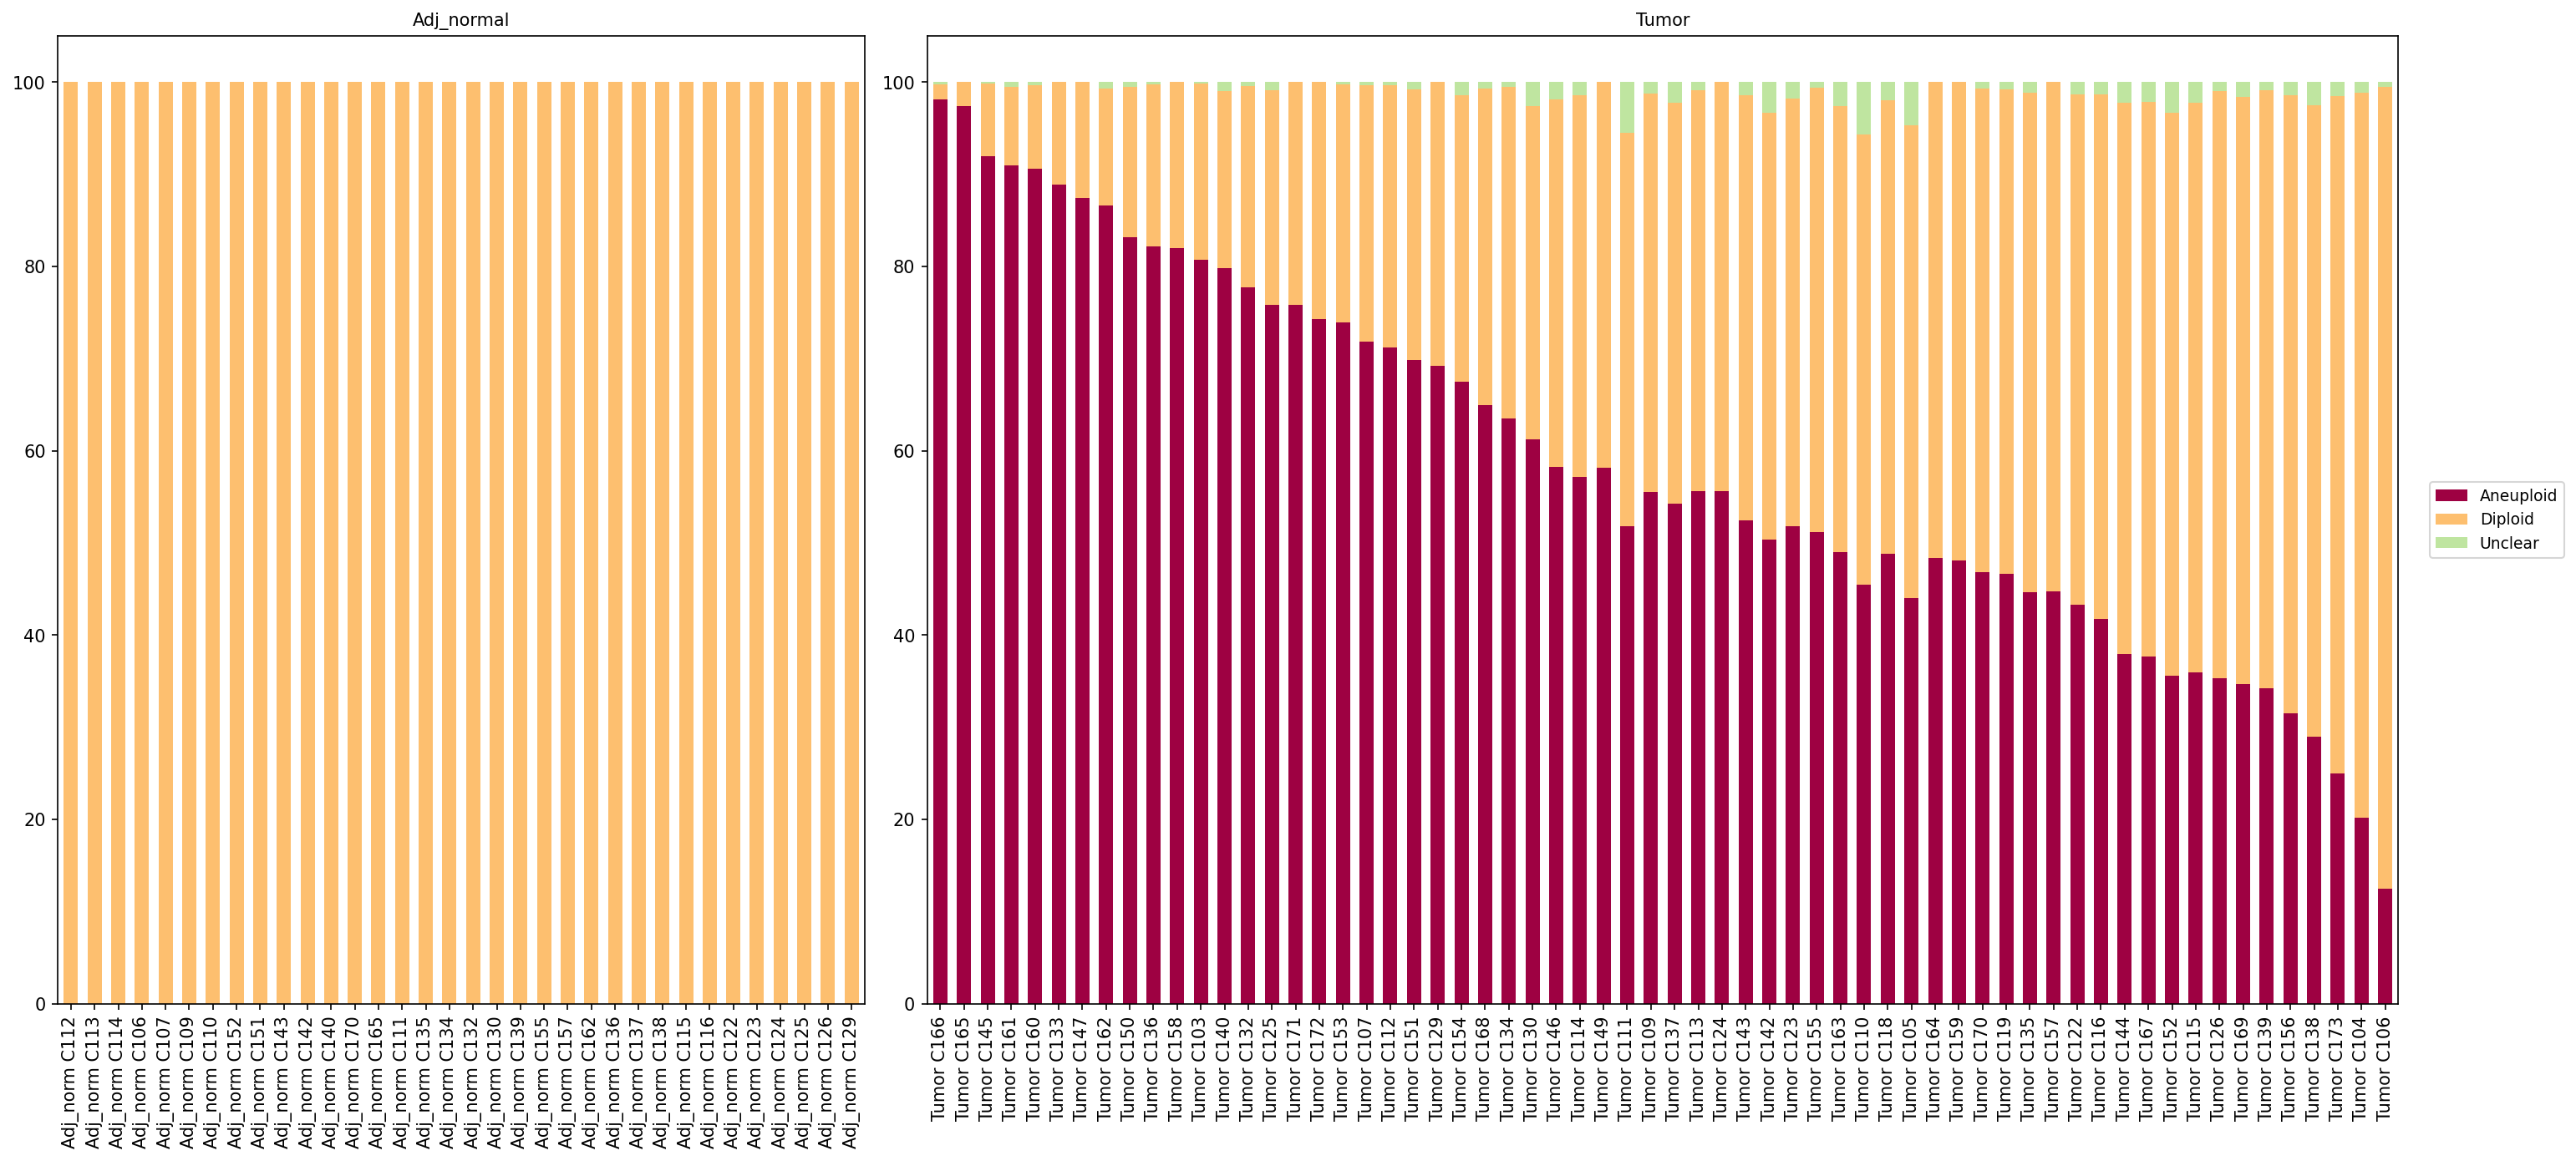
This analysis investigates the ploidy status (Aneuploid, Diploid, Unclear) of tumor-origin cells, specifically identified as Intestinal Epithelial cells, across various samples from both 'Adj_normal' (adjacent normal) and 'Tumor' conditions. The results are presented as stacked bar plots, with each bar representing a single sample and illustrating the proportional distribution of different ploidy populations within that sample. The goal is to characterize the genetic stability of these epithelial cells in the context of colorectal cancer.
Visual Summary
The visualization displays two panels: 'Adj_normal' and 'Tumor', each showing stacked bar plots for individual samples.
- Adj_normal Samples: The bars for all 'Adj_normal' samples are almost entirely composed of 'Diploid' cells (light orange), indicating a genetically stable cell population. A minimal fraction of 'Unclear' cells (light green) is observed in some normal samples, but 'Aneuploid' cells (maroon) are virtually absent.
- Tumor Samples: In stark contrast, 'Tumor' samples exhibit a highly variable but prominent presence of 'Aneuploid' cells (maroon). Many tumor samples (e.g., Tumor C166, Tumor C165, Tumor C161) show a high percentage, often exceeding 90%, of aneuploid cells. Other tumor samples present a mixed population, with the proportion of aneuploid cells ranging down to approximately 10-15% (e.g., Tumor C106, Tumor C104). The 'Diploid' cell population is inversely correlated with the 'Aneuploid' population in these samples, while the 'Unclear' fraction remains relatively small and consistent, similar to the normal samples.
Biological Interpretation
The observed ploidy patterns strongly align with the known characteristics of cancer.
- Cancer Hallmark: The significant presence of 'Aneuploid' cells, particularly within the 'Tumor' condition, is a classical hallmark of cancer. Aneuploidy, the condition of having an abnormal number of chromosomes, arises from genomic instability and is a driving force in tumorigenesis and tumor evolution. The near-exclusive diploid state of 'Intestinal Epithelial cells' from 'Adj_normal' tissue serves as a robust baseline, confirming the pathological nature of the aneuploidy observed in tumor samples.
- Tumor Heterogeneity: The substantial inter-sample variability in the proportion of 'Aneuploid' cells within the 'Tumor' cohort highlights the genetic heterogeneity of colorectal tumors. Some tumors are highly aneuploid, suggesting a pervasive genomic instability across their malignant cells. In contrast, other tumor samples show a significant 'Diploid' component alongside aneuploid cells. This could represent varying degrees of tumor purity (even after selecting for tumor-origin cells, some normal stromal or immune cells might remain, although the "tumor-origin cell type" selection aims to minimize this), or intrinsic biological heterogeneity where a subpopulation of tumor cells or less evolved clones retain a diploid karyotype. Alternatively, it may reflect the presence of early-stage tumors or those with different mechanisms of oncogenesis that do not primarily involve widespread aneuploidy.
- Validation of Tumor-Origin Cell Selection: The clear distinction in ploidy between 'Adj_normal' and 'Tumor' samples, especially among the 'Intestinal Epithelial cells' (the resolved tumor-origin cell type), reinforces the successful identification and isolation of malignant cells. This indicates that the downstream analyses on these cells are likely to capture tumor-specific biological processes.
Clinical or Translational Implications
- Diagnostic and Prognostic Relevance: Aneuploidy is a well-established indicator of malignancy. The degree of aneuploidy in colorectal cancer has been investigated as a potential prognostic marker, with higher levels often associated with more aggressive disease or worse outcomes, although further clinical correlation would be needed for definitive conclusions in this dataset.
- Understanding Tumor Biology: Characterizing the ploidy landscape of tumor cells provides crucial insights into the genomic instability driving colorectal cancer. The heterogeneity observed underscores the importance of personalized approaches in cancer treatment, as tumors with different levels of aneuploidy might respond differently to therapies.
- Quality Control for Single-Cell Analysis: This ploidy analysis serves as an important quality control step, confirming the distinct genetic states of cells from different conditions and providing confidence in the subsequent differential analyses (e.g., DEG, GSEA) performed on these specific cell populations.
12. Cell-Cell Interaction Patterns in Colorectal Tissue: Tumor vs. Adjacent Normal
[Analysis Visualization Results]...
Analysis Overview
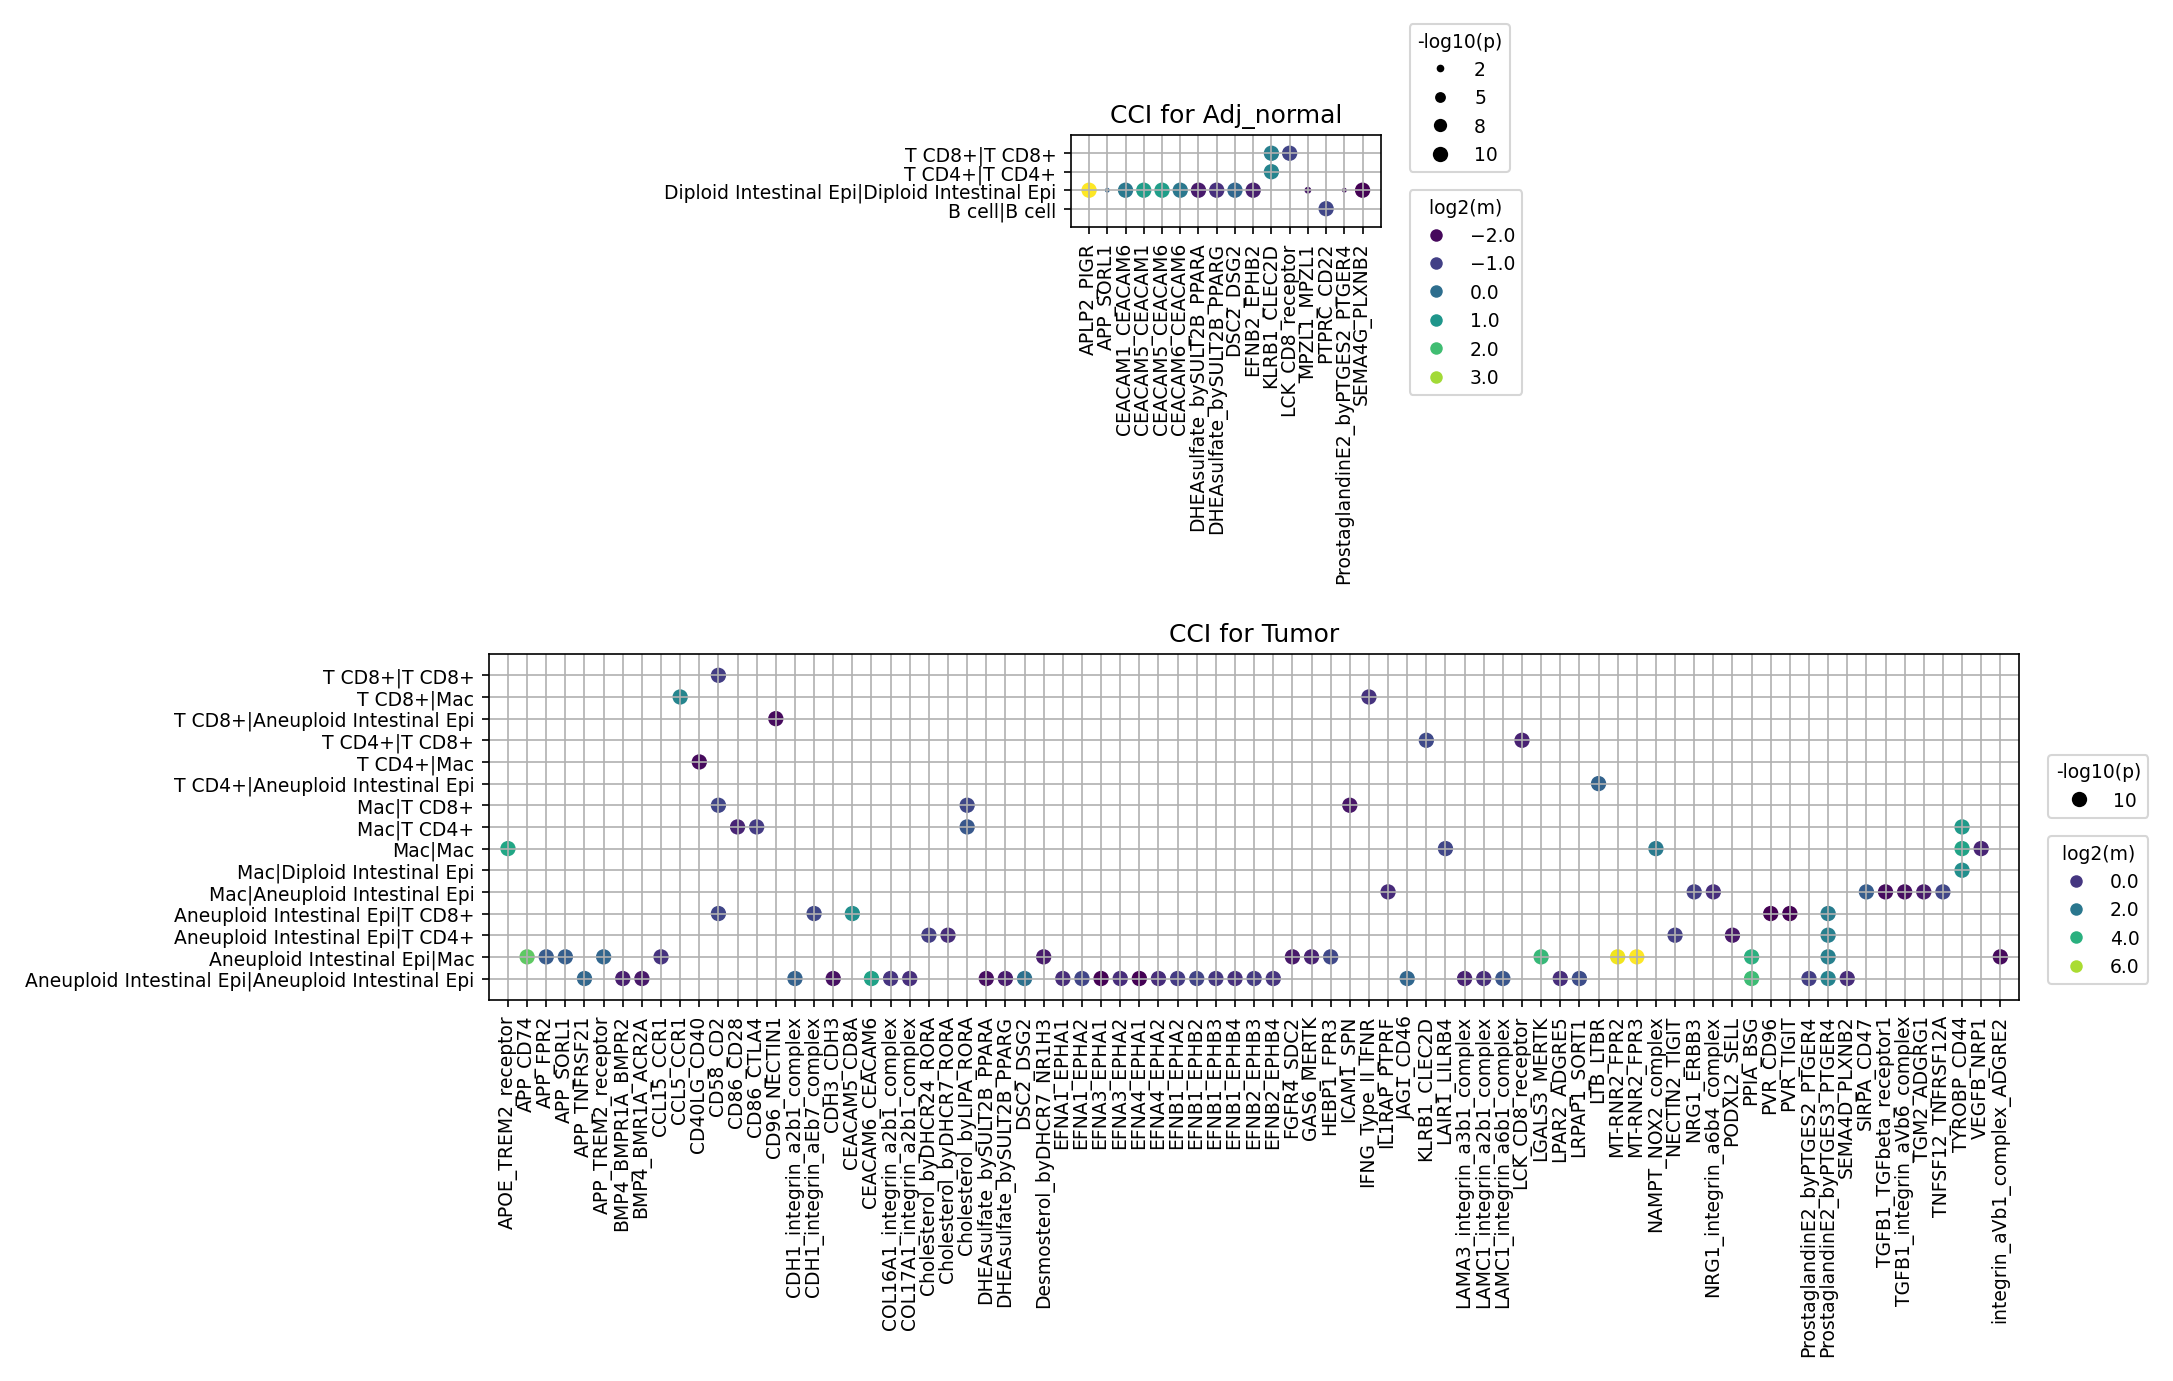
This analysis investigates cell-cell interaction (CCI) patterns using CellPhoneDB results, comparing 'Adj_normal' (adjacent normal) and 'Tumor' conditions within human Colon tissue single-cell RNA-seq data. The goal is to identify significant ligand-receptor interactions between key cell types, including Intestinal Epithelial cells, Fibroblasts, Macrophages, and various T cell subsets, among others. The results highlight how the cellular communication landscape changes dramatically in the colorectal tumor microenvironment compared to healthy tissue.
Visual Summary
The provided dot plots illustrate the strength (dot color, log2(m)) and statistical significance (dot size, -log10(p)) of cell-cell interactions for the top 80 significant pairs in both 'Adj_normal' and 'Tumor' conditions.
Adjacent Normal Condition
The plot for the 'Adj_normal' condition shows a relatively sparse interaction landscape, with fewer significant interactions compared to the tumor. The most prominent interactions are largely homotypic (within the same cell type), involving:
Diploid Intestinal Epi||Diploid Intestinal Epi
T CD8+||T CD8+
T CD4+||T CD4+
B cell||B cell
Key ligand-receptor pairs in the normal context include:
- APLP2_PIGR, CEACAM1_CEACAM1, CEACAM5_CEACAM6, CEACAM6_CEACAM1 within Diploid Intestinal Epi||Diploid Intestinal Epi, suggesting epithelial cell adhesion and mucosal immune regulation.
- KLRB1_CLEC2D and LCK_CD8_TCRcomplex for T cell homotypic interactions, reflecting T cell activation and recognition.
- MZL1_MPZL1 and MPTFRC_CD22 for B cell homotypic interactions, indicating B cell function.
Interaction strengths (log2(m)) are generally lower than those observed in the tumor.
Tumor Condition
The plot for the 'Tumor' condition reveals a significantly more complex and active cell-cell interaction network, characterized by a higher number of significant interactions and generally stronger interaction strengths. A clear shift from homotypic to diverse heterotypic interactions is observed, primarily involving the tumor-origin Aneuploid Intestinal Epi cells, Macrophages, and T cells.
Notable cell-cell pairs and ligand-receptor interactions in the tumor include:
- Aneuploid Intestinal Epi||Aneuploid Intestinal Epi: Shows numerous interactions, including CDH1_integrin_a2b1_complex, COL18A1_integrin_a2b1_complex, SPP1_integrin_a3b1_complex, and TGFB1_TGFBETA_receptor. These indicate enhanced cell adhesion, extracellular matrix (ECM) interactions, and autocrine growth factor signaling among tumor cells.
- Aneuploid Intestinal Epi||Mac: Exhibits strong heterotypic interactions such as APOE_TREM2_receptor, BMP4_BMPR1A_BMPR2, CD40LG_CD40, CXCL12_CXCR4, CCL19_CCR7, EFNA_EPHA family members, SPP1_integrin_aVb1_complex, and TGFB1_TGFBETA_receptor. These highlight extensive crosstalk between tumor cells and tumor-associated macrophages (TAMs), crucial for immune modulation, angiogenesis, and tumor progression.
- Mac||Mac: Demonstrates homotypic interactions like CCL19_CCR7, CCL20_CCR6, CXCL12_CXCR4, SPP1_integrin_aVb1_complex, and TGFB1_TGFBETA_receptor, suggesting macrophage recruitment, activation, and communication within the tumor microenvironment.
- Aneuploid Intestinal Epi||T CD4+ / T CD8+ and Mac||T CD4+ / T CD8+: Show interactions such as IFNG_IFNGR and MIF_CD74, indicating immune cell infiltration and complex immunomodulatory exchanges between tumor cells, macrophages, and T cells.
Overall, the tumor environment demonstrates a pronounced increase in the diversity and intensity of cell-cell communications, particularly involving tumor cells and immune components.
Biological Interpretation
The dramatic differences in CCI patterns between adjacent normal and tumor tissues underscore the extensive remodeling of the tumor microenvironment (TME) in colorectal cancer.
Remodeling of the Tumor Microenvironment
The shift from predominantly homotypic interactions in normal tissue to complex heterotypic interactions in the tumor signifies a profound reorganization of cellular communication. The high activity of Aneuploid Intestinal Epi cells (the identified tumor-origin cells) interacting with macrophages and T cells points to an active TME where diverse cell types engage in intricate crosstalk that supports tumor growth, survival, and progression.
Tumor Cell Adhesion, Migration, and Proliferation
The prominent involvement of integrin-mediated interactions (e.g., SPP1-integrin, CDH1-integrin, COL18A1-integrin) within tumor cells and between tumor cells and other cells suggests enhanced cellular adhesion, increased potential for migration, and interaction with the extracellular matrix—all hallmarks of cancer invasion and metastasis. SPP1 (Osteopontin) is a well-established driver of cancer progression, promoting cell survival, migration, and angiogenesis. GeneCards: SPP1 The frequent TGFB1_TGFBETA_receptor interactions, both autocrine for tumor cells and heterotypic with macrophages, highlight the crucial role of TGF-β signaling in cancer, which can promote proliferation, epithelial-mesenchymal transition, and immunosuppression depending on the context and stage.
Immune Cell Modulation
The extensive interactions involving Macrophages (TAMs) are particularly noteworthy. Ligand-receptor pairs such as CXCL12-CXCR4 and CCL19-CCR7 suggest the strong recruitment and retention of macrophages within the TME. These interactions are critical for polarizing TAMs towards pro-tumorigenic phenotypes that promote angiogenesis, immune evasion, and metastasis. PubMed search: CXCL12 CXCR4 TAM cancer The interplay between tumor cells, macrophages, and T cells, exemplified by interactions like IFNG-IFNGR and MIF_CD74, indicates ongoing immune responses. However, within the context of extensive pro-tumorigenic signaling, these interactions could also contribute to T cell exhaustion or suppression, which is common in the TME.
Clinical or Translational Implications
The identified cell-cell interaction patterns offer significant insights for therapeutic development and biomarker discovery in colorectal cancer:
- Therapeutic Targets: Several highly active ligand-receptor pairs in the tumor microenvironment could serve as attractive therapeutic targets.
- CXCL12-CXCR4 axis: Disrupting this interaction could inhibit the recruitment of pro-tumorigenic macrophages and impede tumor cell migration and metastasis. Strategies targeting CXCR4 have been explored in various cancers. PubMed search: CXCR4 inhibitor cancer therapy
- TGFB1-TGFBETA_receptor signaling: Inhibitors of the TGF-β pathway could be utilized to overcome immunosuppression and reduce tumor growth and invasion. PubMed search: TGFB1 inhibitor cancer therapy
- SPP1-integrin interactions: Modulating these interactions could limit tumor cell adhesion, invasion, and metastatic potential.
- CEACAM5/6: While also present in normal tissue, their increased and diversified interactions in tumor, especially among Aneuploid Intestinal Epi cells, reinforce their role as potential targets, especially given their established association with colorectal cancer. GeneCards: CEACAM5
- Biomarkers: The identified highly significant and tumor-specific cell-cell interactions, or the differential expression of their constituent ligands and receptors, could serve as prognostic or predictive biomarkers for disease progression, metastasis, or response to specific therapies. For instance, the activity of the SPP1-integrin or CXCL12-CXCR4 axes might correlate with metastatic potential.
- Experimental Validation: These findings provide strong hypotheses for further experimental validation. In vitro co-culture experiments can elucidate the functional consequences of specific ligand-receptor interactions on tumor cell behavior (e.g., proliferation, migration, invasion) and immune cell phenotypes (e.g., macrophage polarization, T cell activation/exhaustion). In vivo models or patient-derived organoids could then be used to confirm therapeutic efficacy of targeting these identified pathways.
13. Condition-Specific Cell-Cell Interaction Patterns in Colorectal Cancer
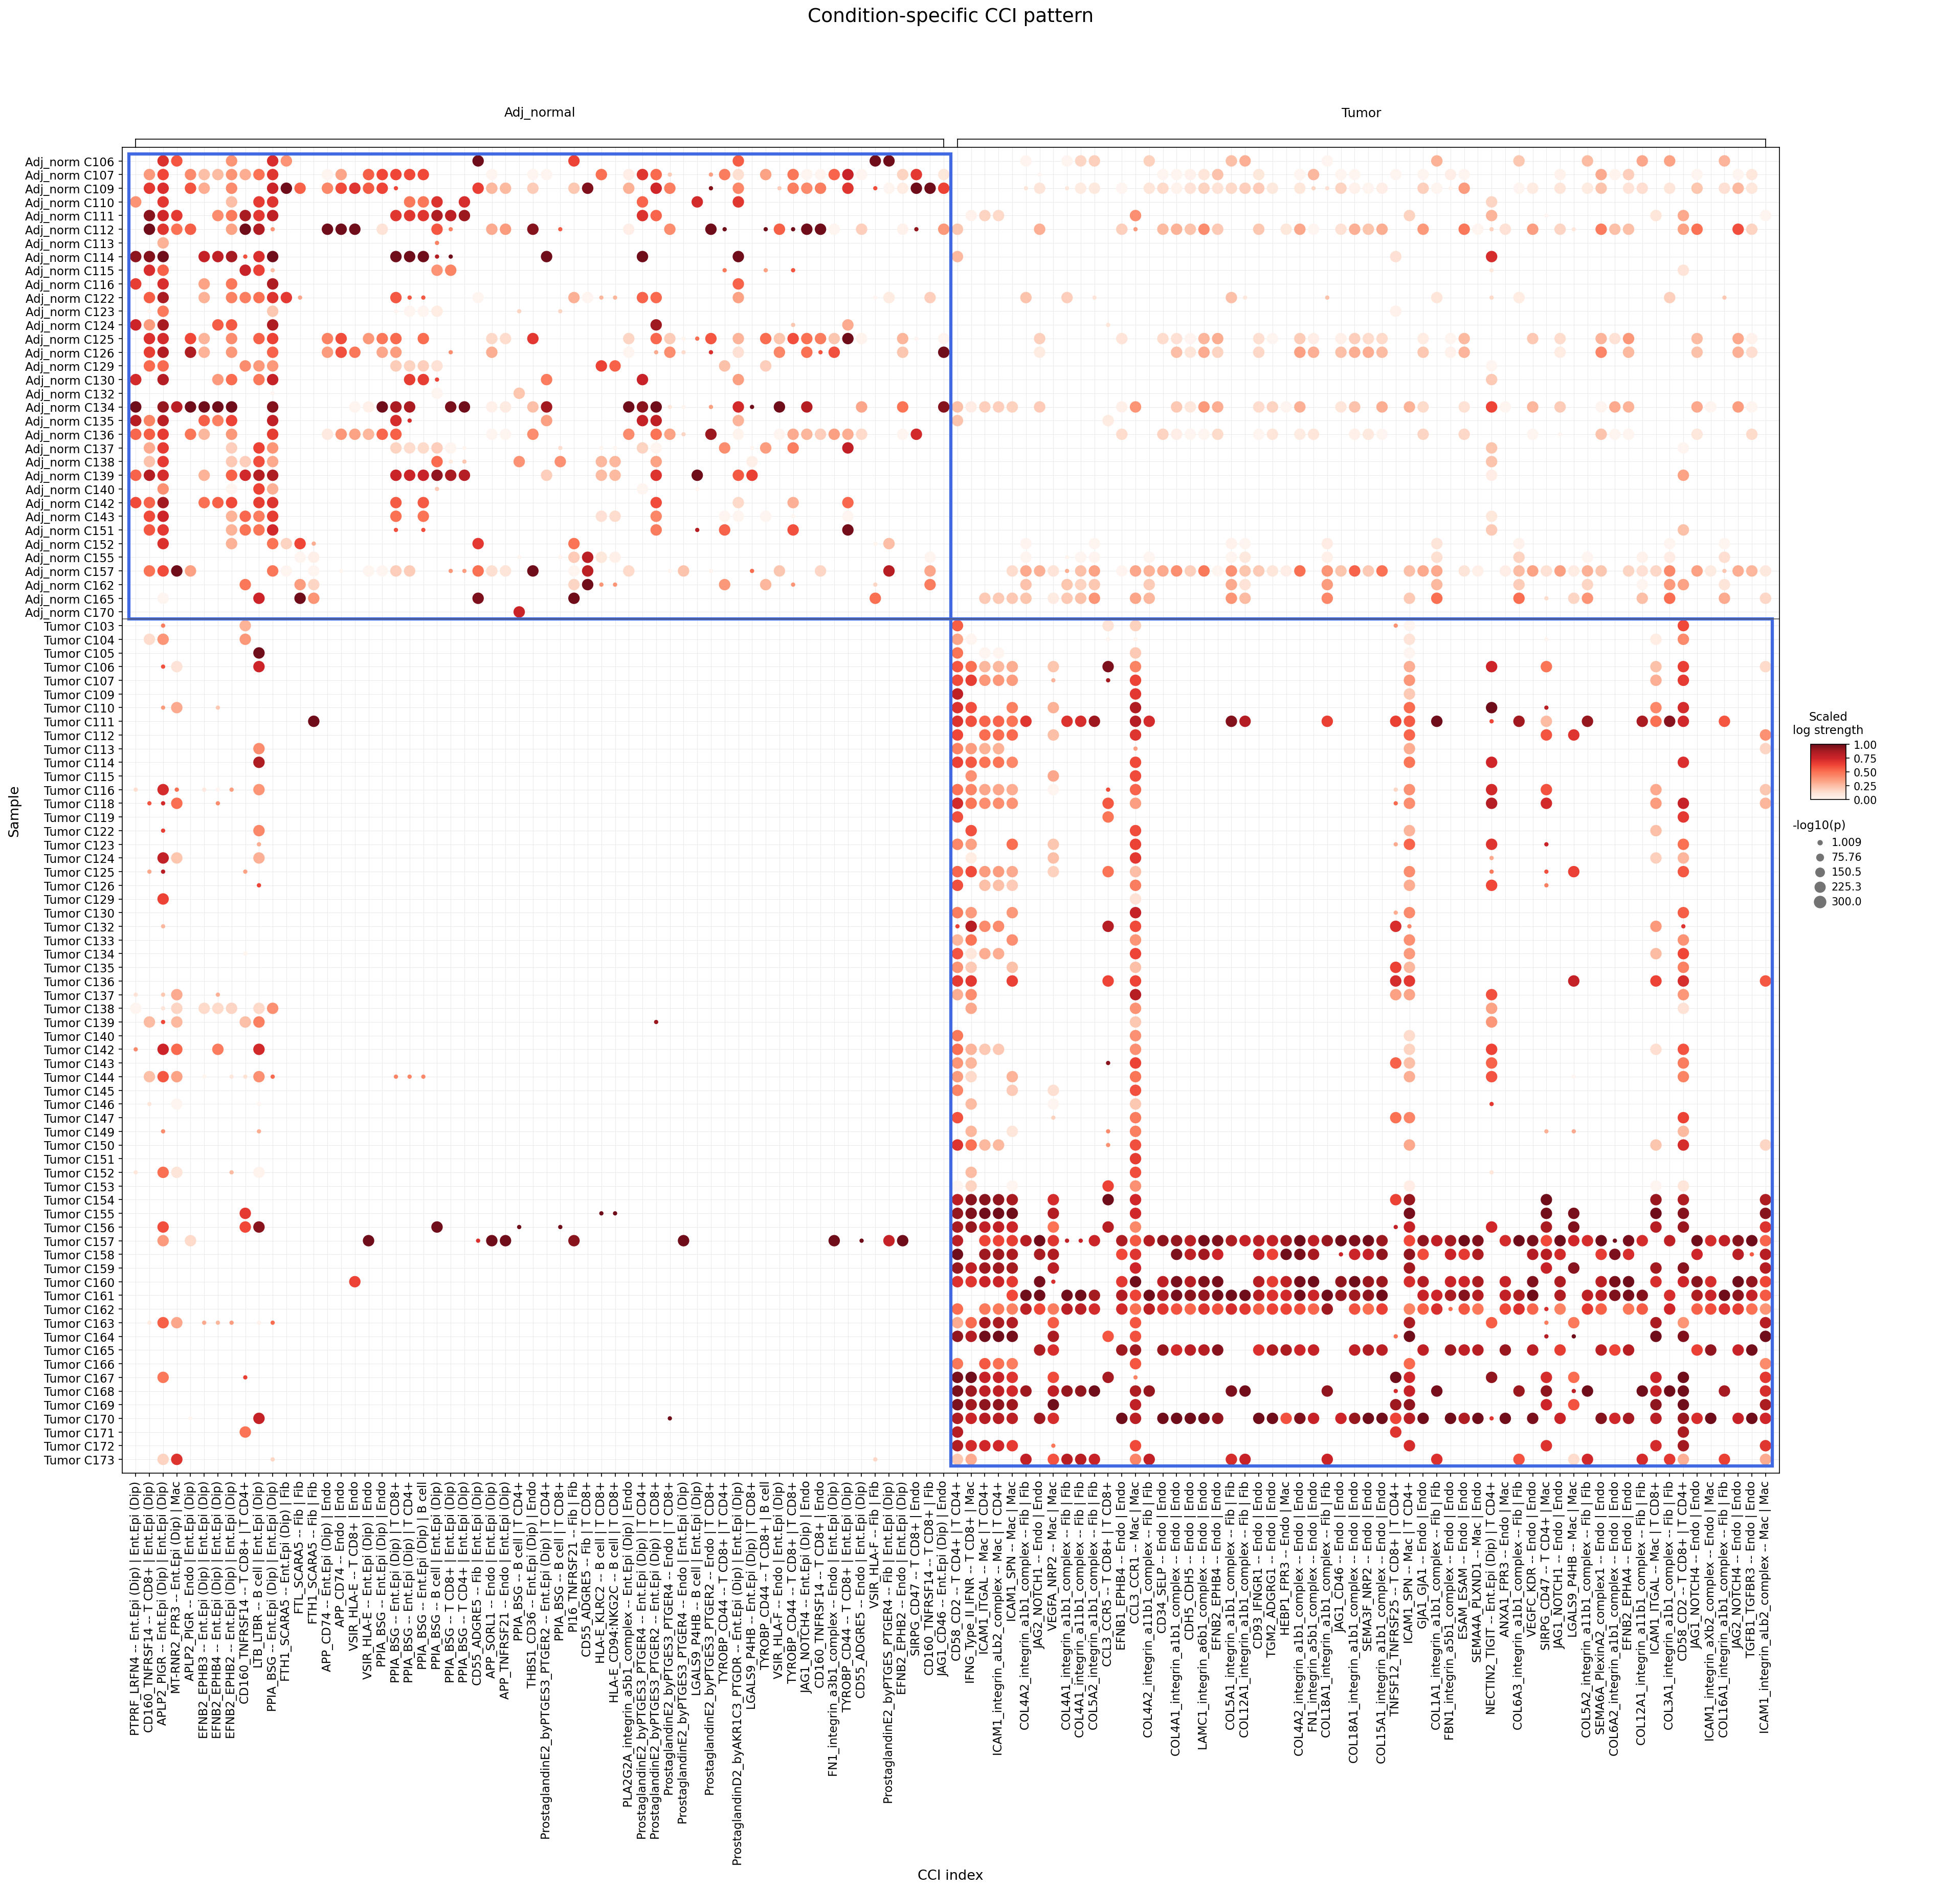
[Analysis Visualization Results]...
Analysis Overview
This analysis identifies cell-cell interactions (CCI) involving Intestinal Epithelial cells, major immune cells (Myeloid, T, Mast, B), and Stromal cells that significantly differ between colorectal tumor and adjacent normal (Adj_normal) tissues. The results are presented as a dot plot, where each dot represents the interaction strength and significance for a specific ligand-receptor pair between two cell types within individual samples. Dot color indicates the scaled log strength of the interaction, and dot size represents the -log10(p-value) of the interaction's significance, highlighting differences between conditions. The plot displays up to 60 significantly different interactions for each condition.
Visual Summary
The dot plot clearly segregates cell-cell interaction patterns between 'Adj_normal' and 'Tumor' conditions.
- Adj_normal Specific Interactions: The upper-left quadrant, representing interactions in 'Adj_normal' samples, shows a distinct set of highly significant and strong interactions. These interactions are largely absent or very weak in the 'Tumor' samples. Key interactions involve Intestinal Epithelial cells (denoted as Ent.Epi, some with Diploid (Dip) status), B cells, T cells (CD4+, CD8+), and Endothelial cells.
- Tumor Specific Interactions: The lower-right quadrant, representing interactions in 'Tumor' samples, displays a substantially different and more numerous set of strong and significant interactions. These interactions are largely absent or very weak in the 'Adj_normal' samples. A striking pattern is the enrichment of interactions involving Fibroblasts and Endothelial cells, particularly those mediated by various Collagen-integrin complexes, as well as interactions involving Macrophages and T cells.
- Condition-Specific Patterns: The clear separation of strong interactions between the 'Adj_normal' and 'Tumor' specific quadrants indicates profound remodeling of the cellular communication landscape in the tumor microenvironment. The sparsity of dots in the upper-right and lower-left quadrants further confirms that the identified interactions are largely specific to either the normal or tumor condition.
Biological Interpretation
The distinct cell-cell interaction profiles reveal how cellular communication is reprogrammed in colorectal cancer, affecting tissue homeostasis, immune responses, and the tumor microenvironment (TME).
Interactions Enriched in Adj_normal Tissue
Interactions prominent in adjacent normal tissue likely reflect homeostatic epithelial-immune-stromal communication crucial for healthy colon function, including immune surveillance and tissue maintenance.
- PPIA_BSG between Intestinal Epithelial cells and B cells:
- Signaling Pathway/Mechanism: Secreted Cyclophilin A (PPIA) can bind to Basigin (BSG, also known as CD147 or EMMPRIN) on the cell surface. This interaction is known to promote the secretion of matrix metalloproteinases (MMPs) and can influence cell migration, invasion, and inflammation. In the normal colon, this interaction might contribute to tissue remodeling, B cell activation, or maintenance of epithelial barrier integrity. GeneCards: PPIA, GeneCards: BSG
- Potential as Therapeutic Target & Agents: While specific to normal tissue here, dysregulation of PPIA-BSG in cancer generally promotes tumor progression. Modulating this axis might be considered in contexts where it contributes to immune suppression or matrix degradation within the TME, though direct targeting based on its normal function would need careful consideration.
- EPHB2_EPHB4 between Intestinal Epithelial cells and T cell CD4+:
- Signaling Pathway/Mechanism: Ephrin receptors (EphBs) and their ligands (ephrins) mediate cell-cell contact-dependent signaling, crucial for cell migration, axon guidance, angiogenesis, and cell-fate determination. EPHB2 and EPHB4 are both receptor tyrosine kinases, and their interaction plays roles in maintaining tissue architecture and cell positioning. In the normal colon, this could regulate epithelial cell dynamics and interactions with resident T cells for immune surveillance. GeneCards: EPHB2, GeneCards: EPHB4
- Potential as Therapeutic Target & Agents: Dysregulation of Ephrin-Eph signaling is implicated in various cancers. While high in normal tissue, understanding its disruption in cancer could point to therapeutic avenues.
- CD160_TNFRSF14 between T cell CD8+ and Endothelial cells:
- Signaling Pathway/Mechanism: CD160 is an activating or co-inhibitory receptor expressed on subsets of T cells, NK cells, and other immune cells. TNFRSF14 (HVEM) is a TNF receptor superfamily member, expressed on many cell types, including endothelial cells. This interaction can modulate T cell activation and adhesion, potentially impacting immune cell trafficking and vascular integrity in healthy tissue. GeneCards: CD160, GeneCards: TNFRSF14
- Potential as Therapeutic Target & Agents: This axis is involved in immune regulation. In cancer, similar immune checkpoints are targeted for immunotherapy. Understanding its role in normal tissue is crucial before considering modulation in disease.
Interactions Enriched in Tumor Tissue
Interactions significantly increased in tumor samples highlight mechanisms driving cancer progression, angiogenesis, immune evasion, and stromal remodeling, consistent with colorectal cancer pathogenesis.
- Collagen-Integrin Complexes (e.g., COL4A1_integrin_a1b1_complex, COL1A1_integrin_a1b1_complex) between Fibroblasts and Endothelial cells:
- Signaling Pathway/Mechanism: This is a major finding, with numerous collagen-integrin interactions dominating the tumor-specific landscape. Collagens are key components of the extracellular matrix (ECM), and integrins (heterodimeric cell surface receptors like integrin alpha1beta1) mediate cell adhesion to the ECM. This extensive interaction signifies profound remodeling of the TME, enhanced ECM deposition by Fibroblasts (which include Cancer-Associated Fibroblasts, CAFs), and altered adhesion/migration of Endothelial cells. This is critical for angiogenesis (new blood vessel formation), tumor cell invasion, and metastasis, creating a pro-tumorigenic niche. GeneCards: COL4A1, GeneCards: ITGA1, GeneCards: ITGB1, PubMed search: Collagen Integrin Cancer Microenvironment
- Potential as Therapeutic Target & Agents: Targeting specific collagen types or integrin subunits is a promising strategy. Integrin inhibitors (e.g., cilengitide targeting αvβ3/αvβ5 integrins) have been explored in clinical trials to inhibit angiogenesis and metastasis. Inhibiting collagen deposition or cross-linking (e.g., using anti-fibrotic agents) could also disrupt the pro-tumorigenic ECM.
- SPP1_integrin_a1b1_complex between Endothelial cells and Macrophages:
- Signaling Pathway/Mechanism: Secreted Phosphoprotein 1 (SPP1, also known as Osteopontin) is a multifunctional cytokine-like protein that binds to integrins (e.g., αvβ3, αvβ5, α4β1, and α1β1 identified here) and CD44. SPP1 promotes cell adhesion, migration, survival, and invasion, and is a potent stimulator of angiogenesis and macrophage recruitment/polarization. Its interaction with integrins on endothelial cells and macrophages indicates active crosstalk contributing to immune cell infiltration, inflammation, and vascularization within the TME, fostering tumor growth and metastasis. GeneCards: SPP1, PubMed search: SPP1 Integrin Cancer
- Potential as Therapeutic Target & Agents: SPP1 is a known cancer biomarker and therapeutic target. Monoclonal antibodies against SPP1 or integrins that bind SPP1 (e.g., αvβ3 integrin) could disrupt these pro-tumorigenic interactions.
- JAG1_NOTCH1 between Fibroblasts and Endothelial cells:
- Signaling Pathway/Mechanism: Jagged1 (JAG1) is a ligand for Notch receptors, and Notch1 (NOTCH1) is a key receptor in the Notch signaling pathway. This pathway is fundamental for cell fate determination, proliferation, differentiation, and stem cell maintenance. In the TME, JAG1-NOTCH1 signaling between fibroblasts and endothelial cells can promote angiogenesis, sustain cancer stem cells, and contribute to stromal activation, thus facilitating tumor growth and maintenance. GeneCards: JAG1, GeneCards: NOTCH1, PubMed search: Notch Signaling Cancer Angiogenesis
- Potential as Therapeutic Target & Agents: The Notch pathway is a well-established therapeutic target in cancer. Gamma-secretase inhibitors (GSIs) block Notch receptor cleavage and activation, and antibodies targeting Notch receptors or ligands (like JAG1) are under investigation as anti-cancer agents, particularly in combination therapies to inhibit angiogenesis and tumor growth.
- ProstaglandinE2_byPTGES3_PTGER4 between Macrophages and T cell CD4+:
- Signaling Pathway/Mechanism: Prostaglandin E2 (PGE2), synthesized by PTGES3 (Prostaglandin E Synthase 3), binds to its receptor PTGER4 (EP4 receptor) on target cells. Macrophages are a significant source of PGE2, which can act on T cells. This interaction is a potent immunosuppressive mechanism within the TME, promoting T cell exhaustion, inhibiting anti-tumor immunity, and fostering an inflammatory microenvironment conducive to tumor growth. PGE2 also supports angiogenesis and tumor cell proliferation. GeneCards: PTGES3, GeneCards: PTGER4, PubMed search: PGE2 Immunosuppression Cancer
- Potential as Therapeutic Target & Agents: Targeting the PGE2 pathway, particularly the EP4 receptor, is a promising strategy to reverse immune suppression in cancer. EP4 antagonists are being developed and tested in clinical trials as immunomodulatory agents, often in combination with checkpoint inhibitors.
Clinical or Translational Implications
The profound shift in cell-cell interactions from adjacent normal tissue to tumor tissue provides critical insights into the molecular mechanisms driving colorectal cancer progression and offers potential avenues for therapeutic intervention.
- Understanding TME Remodeling: The dominant presence of collagen-integrin interactions, particularly involving fibroblasts and endothelial cells, underscores the importance of the extracellular matrix and angiogenesis in shaping the colorectal TME. This suggests that targeting these interactions could disrupt tumor growth, invasion, and metastasis by normalizing the TME.
- Immune Evasion and Inflammation: Interactions like SPP1-integrin and PGE2-PTGER4 highlight key mechanisms of immune suppression and chronic inflammation within the tumor. Modulating these pathways could enhance anti-tumor immune responses, potentially sensitizing tumors to existing immunotherapies or forming the basis for novel immunotherapeutic approaches.
- Targeting Stromal-Epithelial/Endothelial Crosstalk: The prominence of interactions like JAG1-NOTCH1 between fibroblasts and endothelial cells points to crucial stromal-endothelial crosstalk in tumor development. Disrupting these pathways could inhibit tumor angiogenesis and impact cancer stem cell niches.
- Biomarker Identification: The identified condition-specific interactions could serve as potential diagnostic or prognostic biomarkers for colorectal cancer. For instance, increased expression of specific collagens, integrins, SPP1, or components of the Notch or PGE2 pathways in tumor biopsies could indicate disease progression or therapeutic response.
Therapeutic Strategies:
- ECM/Integrin Inhibitors: Therapies targeting specific integrin subunits (e.g., αvβ3, α1β1) or enzymes involved in collagen synthesis/cross-linking could reduce tumor stiffness, angiogenesis, and metastatic potential.
- SPP1/CD44 Blockade: Agents neutralizing SPP1 or blocking its receptors (integrins, CD44) could inhibit tumor invasion, metastasis, and immune modulation.
- Notch Pathway Inhibitors: Gamma-secretase inhibitors (GSIs) or specific antibody-based therapies could suppress angiogenesis and target cancer stem cells.
- PGE2/EP4 Receptor Antagonists: Blocking the EP4 receptor could reverse immune suppression, enhance T cell activity, and reduce pro-tumorigenic inflammation.
These findings highlight the complexity of the colorectal cancer microenvironment and provide a rational basis for exploring combination therapies that simultaneously target tumor cells and their supportive stromal and immune components.
14. Condition-Specific Cell-Cell Interaction Patterns of Immune Checkpoint and Cell Cycle Pathway Genes in Colorectal Cancer
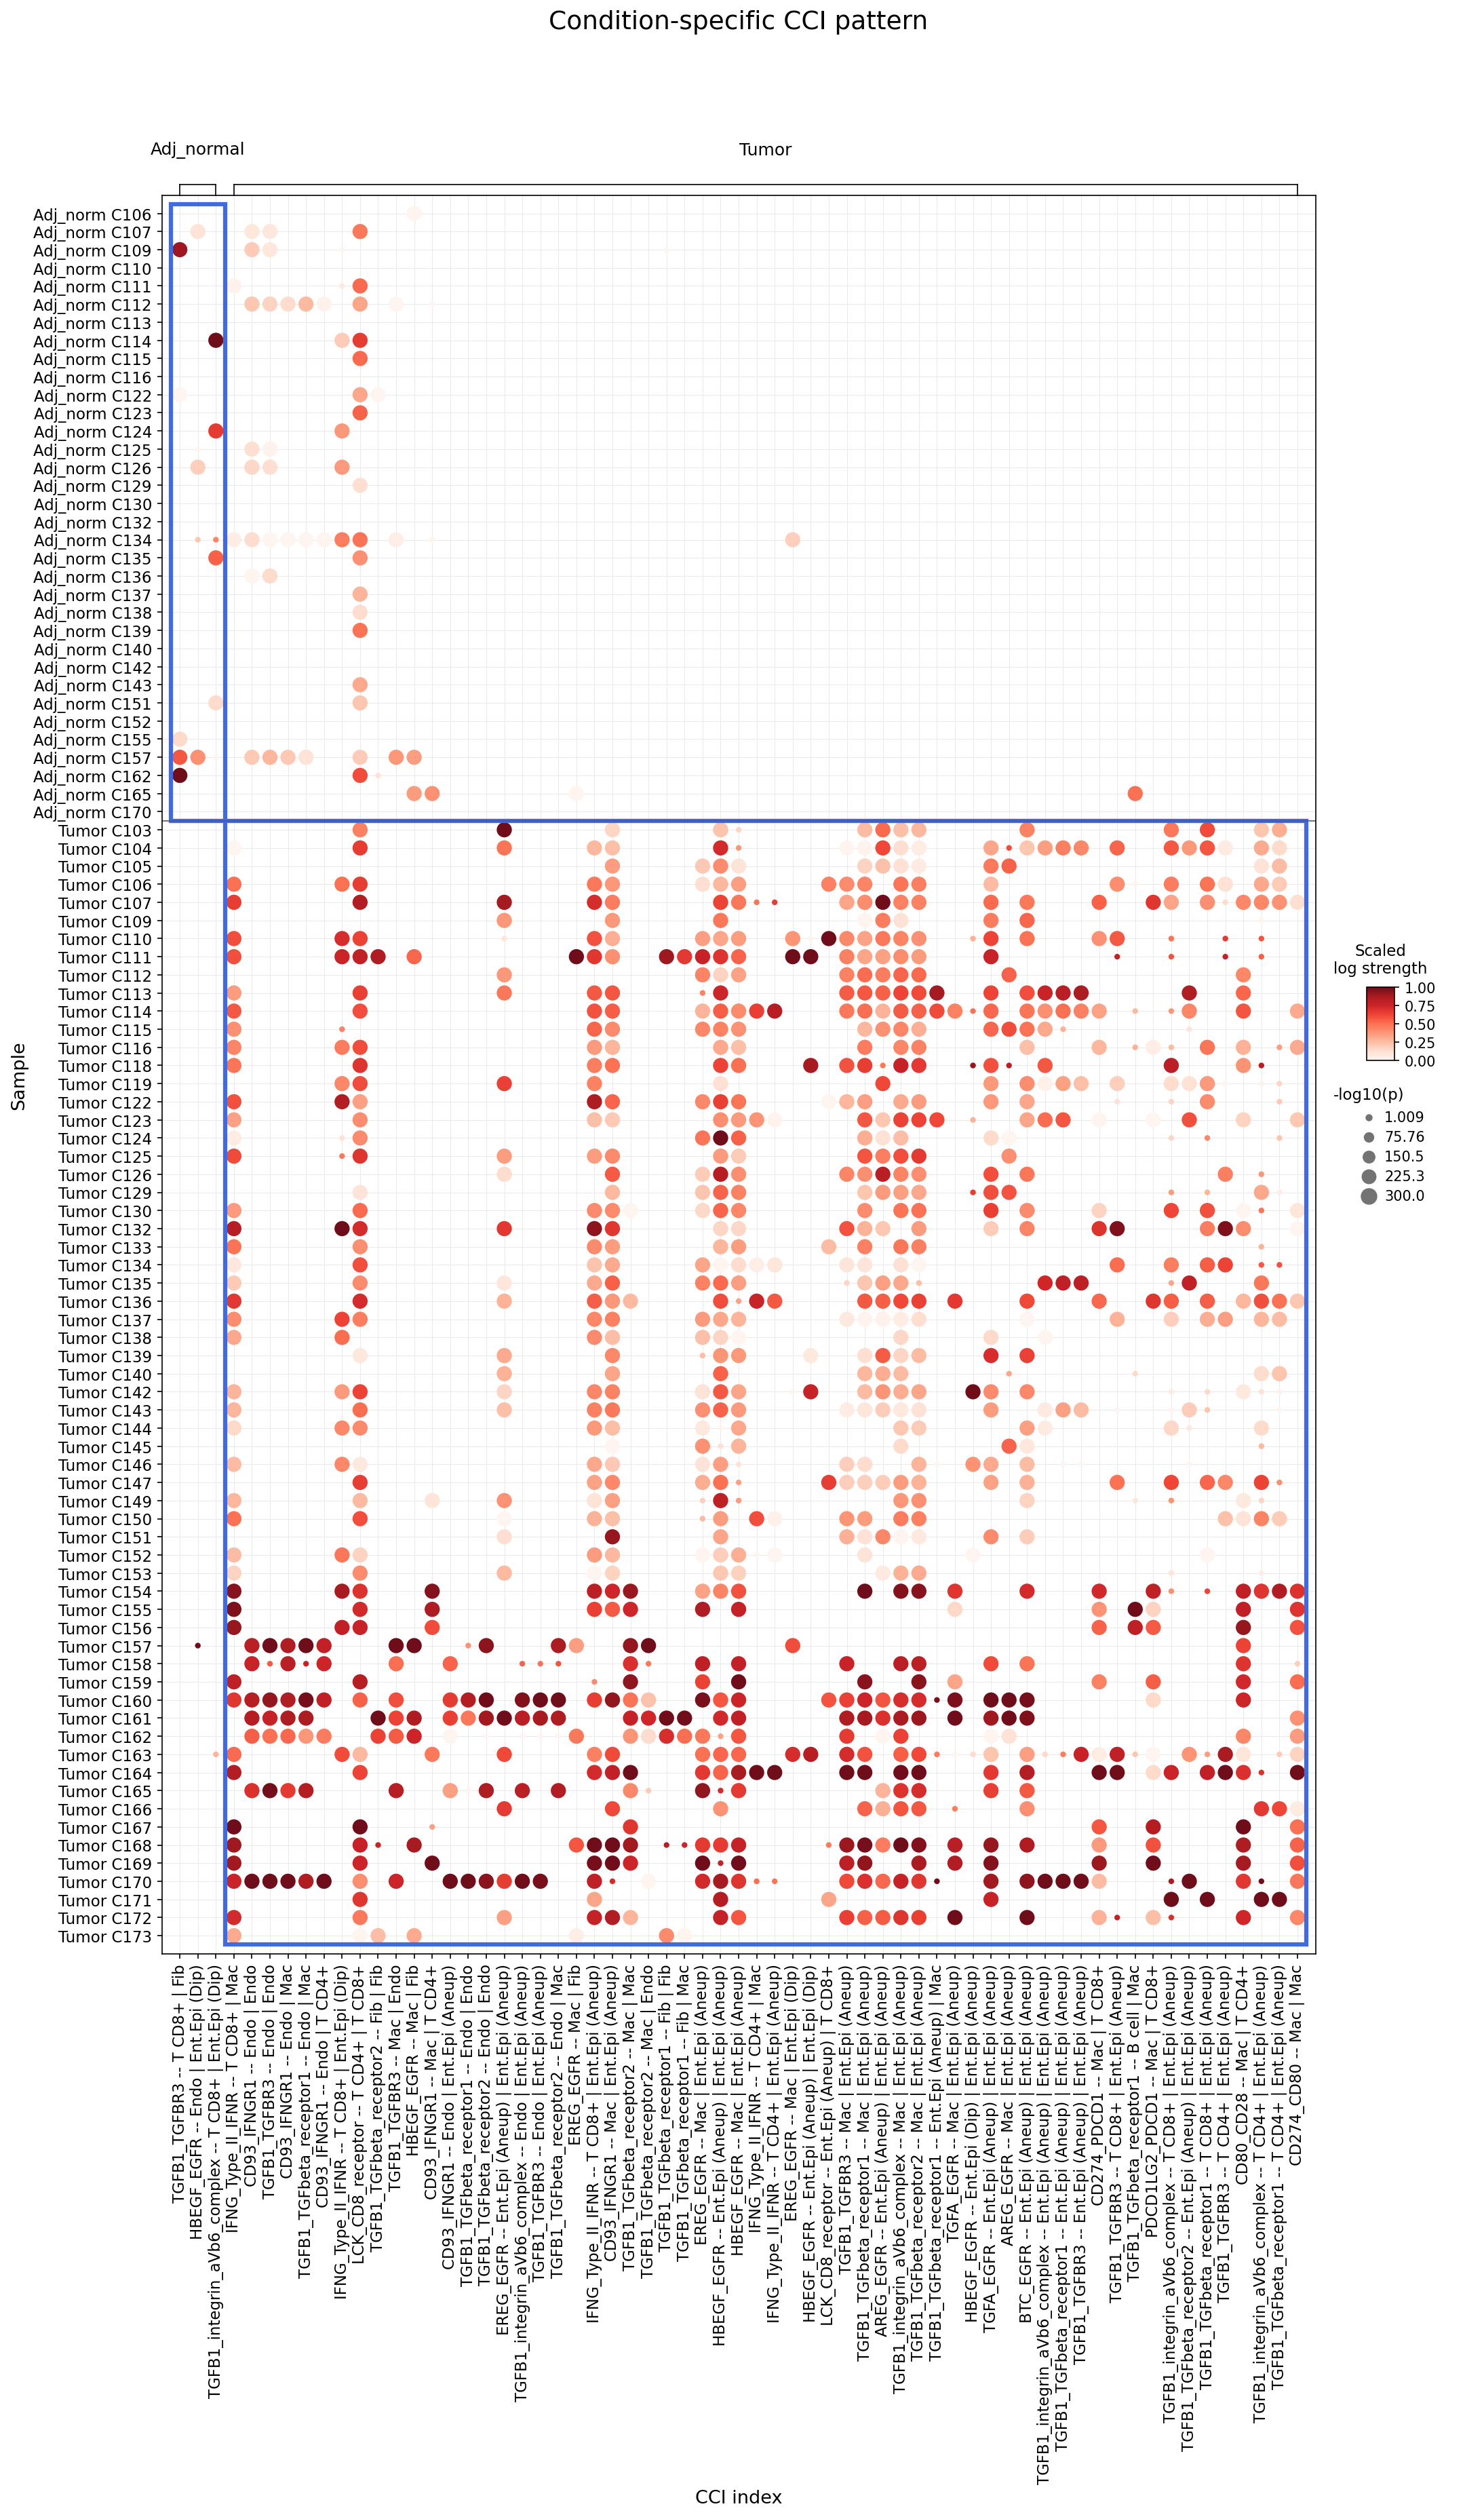
[Analysis Visualization Results]...
Analysis Overview
This analysis investigates condition-specific cell-cell interactions (CCI) within single-cell RNA-seq data from Colon tissue, comparing Tumor and Adjacent Normal ('Adj_normal') samples. The focus is on interactions involving Intestinal Epithelial cells, major immune cell types (Myeloid, T, Mast, B), and Stromal cells (Fibroblasts, Endothelial cells), with a specific emphasis on genes related to immune checkpoint regulation and cell cycle pathways. The plot_dot_for_cci_with_signif_difference tool was used to visualize significant differences in CCI strength and prevalence across individual samples for each condition. The results highlight key intercellular communication axes that are differentially activated in the colorectal tumor microenvironment.
Visual Summary
The dot plot visualizes the strength (color intensity, 'Scaled log strength') and statistical significance (dot size, '-log10(p)') of specific cell-cell interactions across individual samples.
- Striking Condition-Specific Difference: A stark difference in CCI patterns is observed between the Adj_normal and Tumor conditions. The Adj_normal samples exhibit very few significant interactions, indicating a relatively quiescent or homeostatic intercellular communication landscape for the selected gene set. In contrast, the Tumor samples display a dramatically increased number and strength of interactions, characterized by numerous large, dark red dots across multiple CCI indices. This strongly suggests an activated and reprogrammed cellular communication network within the tumor microenvironment.
- Dominant Interactions in Tumor: Several key cell-cell interactions are highly prevalent and strong in the Tumor samples:
- TGFB1 Signaling: Multiple interactions involving TGFB1 (Transforming Growth Factor Beta 1) and its receptors (TGFbeta_receptor1, TGFbeta_receptor2, TGFBR3) are highly active. These interactions span various cell types, including autocrine/paracrine loops within aneuploid Intestinal Epithelial cells (e.g., TGFB1_integrin_aVb6_complex -- Ent.Epi (Aneuploid) | Ent.Epi (Aneuploid)), and heterotypic interactions between aneuploid Intestinal Epithelial cells and Macrophages (e.g., TGFB1_TGFbeta_receptor1 -- Ent.Epi (Aneuploid) | Mac), as well as Fibroblasts (e.g., TGFB1_TGFbeta_receptor1 -- Fib | Ent.Epi (Aneuploid)).
- EGFR Signaling: Interactions involving various EGFR ligands (HBEGF, EREG, TGFA, BTC) and EGFR are prominently active, primarily in autocrine/paracrine fashion within aneuploid Intestinal Epithelial cells (e.g., HBEGF_EGFR -- Ent.Epi (Aneuploid) | Ent.Epi (Aneuploid)).
- Immune Checkpoint (PD-1/PD-L1): The interaction CD274_PDCD1 -- T CD8+ | Ent.Epi (Aneuploid) is highly active and strong across many tumor samples. This represents the interaction between PD-L1 (CD274) on aneuploid Intestinal Epithelial (tumor) cells and PD-1 (PDCD1) on CD8+ T cells.
- Co-stimulatory Interactions: The CD80_CD28 -- Mac | T CD4+ interaction, representing a co-stimulatory signal between Macrophages and CD4+ T cells, is also observed in several tumor samples.
- IFN Signaling: Interactions involving IFNG_Type_II_IFNR are present, notably between T cells (CD8+, CD4+) and Macrophages, indicating active interferon-gamma signaling within the tumor immune infiltrate.
- CD93-IFNGR1: Interactions of CD93_IFNGR1 are observed between Endothelial cells and Macrophages or Intestinal Epithelial cells, suggesting a role in endothelial-immune cell communication within the tumor.
Biological Interpretation
The observed CCI patterns reveal a highly dynamic and oncogenic intercellular communication network in colorectal cancer, largely absent in adjacent normal tissue.
- Tumor-Driving Signaling: The widespread activation of EGFR-ligand/EGFR autocrine/paracrine loops within aneuploid Intestinal Epithelial cells points to strong intrinsic proliferative and survival signaling in tumor cells. EGFR signaling is a well-established driver of colorectal cancer progression, promoting cell growth, survival, angiogenesis, and metastasis. GeneCards: EGFR
- TGF-beta in the Tumor Microenvironment: The strong and diverse TGFB1-related interactions are indicative of a complex role for TGF-beta signaling in colorectal cancer. TGFB1, a pleiotropic cytokine, is known to have both tumor-suppressive and tumor-promoting effects depending on the context and stage. In advanced cancer, TGFB1 often acts as a pro-oncogenic factor, promoting epithelial-mesenchymal transition (EMT), immune suppression, angiogenesis, and fibrosis. The interactions between tumor cells, macrophages, and fibroblasts via TGFB1 highlight its role in orchestrating the immunosuppressive and pro-metastatic tumor microenvironment. PubMed: TGFB1 cancer review
Immune Evasion and Activation:
- The prominent CD274_PDCD1 (PD-L1/PD-1) interaction between aneuploid Intestinal Epithelial cells and CD8+ T cells is a classic mechanism of immune evasion employed by cancer cells. Tumor cells upregulate PD-L1 to bind PD-1 on activated T cells, leading to T cell exhaustion and suppression of anti-tumor immunity. GeneCards: PDCD1
- The CD80_CD28 interaction between Macrophages and CD4+ T cells suggests an ongoing antigen presentation and co-stimulatory activity in the tumor microenvironment. While CD28 signaling is crucial for T cell activation, the overall immune context, especially the presence of PD-1/PD-L1 interactions, may dictate whether this leads to effective anti-tumor immunity or sustained chronic inflammation.
- IFNG Type II IFNR signaling involvement between T cells and Macrophages indicates an inflammatory response. While IFN-gamma can directly inhibit tumor growth and activate immune cells, it can also induce PD-L1 expression on tumor cells, contributing to a feedback loop that eventually promotes immune evasion.
- Endothelial-Immune Crosstalk: The CD93_IFNGR1 interactions involving Endothelial cells and Macrophages suggest endothelial cell involvement in immune regulation and inflammation within the tumor. CD93 is implicated in angiogenesis and inflammation, both critical processes in tumor progression.
Clinical or Translational Implications
The identified highly active cell-cell interactions in colorectal cancer samples represent significant pathways for potential therapeutic intervention.
- EGFR Inhibition: The widespread autocrine/paracrine EGFR signaling within tumor epithelial cells strongly supports the use of EGFR inhibitors (e.g., cetuximab, panitumumab) in appropriate colorectal cancer patients, particularly those with wild-type *KRAS*, *NRAS*, and *BRAF* genes. This analysis further reinforces the rationale for targeting EGFR as a primary driver.
- Immune Checkpoint Blockade: The prominent CD274_PDCD1 interaction is a direct indicator of immune evasion via the PD-1/PD-L1 axis. This provides strong support for PD-1 inhibitors (e.g., pembrolizumab, nivolumab) or PD-L1 inhibitors (e.g., atezolizumab, durvalumab) as therapeutic strategies, especially relevant for colorectal cancer patients with high microsatellite instability (MSI-H) or deficient mismatch repair (dMMR), where immune checkpoint inhibitors have shown significant efficacy. PubMed: MSI-H colorectal cancer immunotherapy
- TGF-beta Pathway Modulation: The extensive involvement of TGFB1 signaling in diverse cell interactions within the tumor microenvironment highlights its potential as a therapeutic target to overcome immunosuppression, reduce fibrosis, and inhibit EMT. TGF-beta inhibitors (e.g., galunisertib, fresolimumab, or small molecule inhibitors of TGF-beta receptor kinases) could be explored, possibly in combination with other agents, to reprogram the tumor microenvironment and enhance anti-tumor immunity. UniProt: TGFB1
- Targeting Macrophage-T cell Interactions: Modulating the CD80_CD28 and IFNG_Type_II_IFNR interactions, along with other macrophage-T cell crosstalk, could enhance anti-tumor immunity. Strategies could include agents that polarize macrophages towards an anti-tumor M1 phenotype or enhance T cell activation.
- Combined Therapies: Given the complex interplay of these pathways, combination therapies targeting multiple axes simultaneously (e.g., EGFR inhibitors with immune checkpoint inhibitors, or TGF-beta inhibitors with immune checkpoint inhibitors) may offer synergistic benefits in overcoming tumor resistance and improving patient outcomes in colorectal cancer.
15. Intestinal Epithelial Cell Condition-Specific Surfaceome Markers in Colorectal Cancer
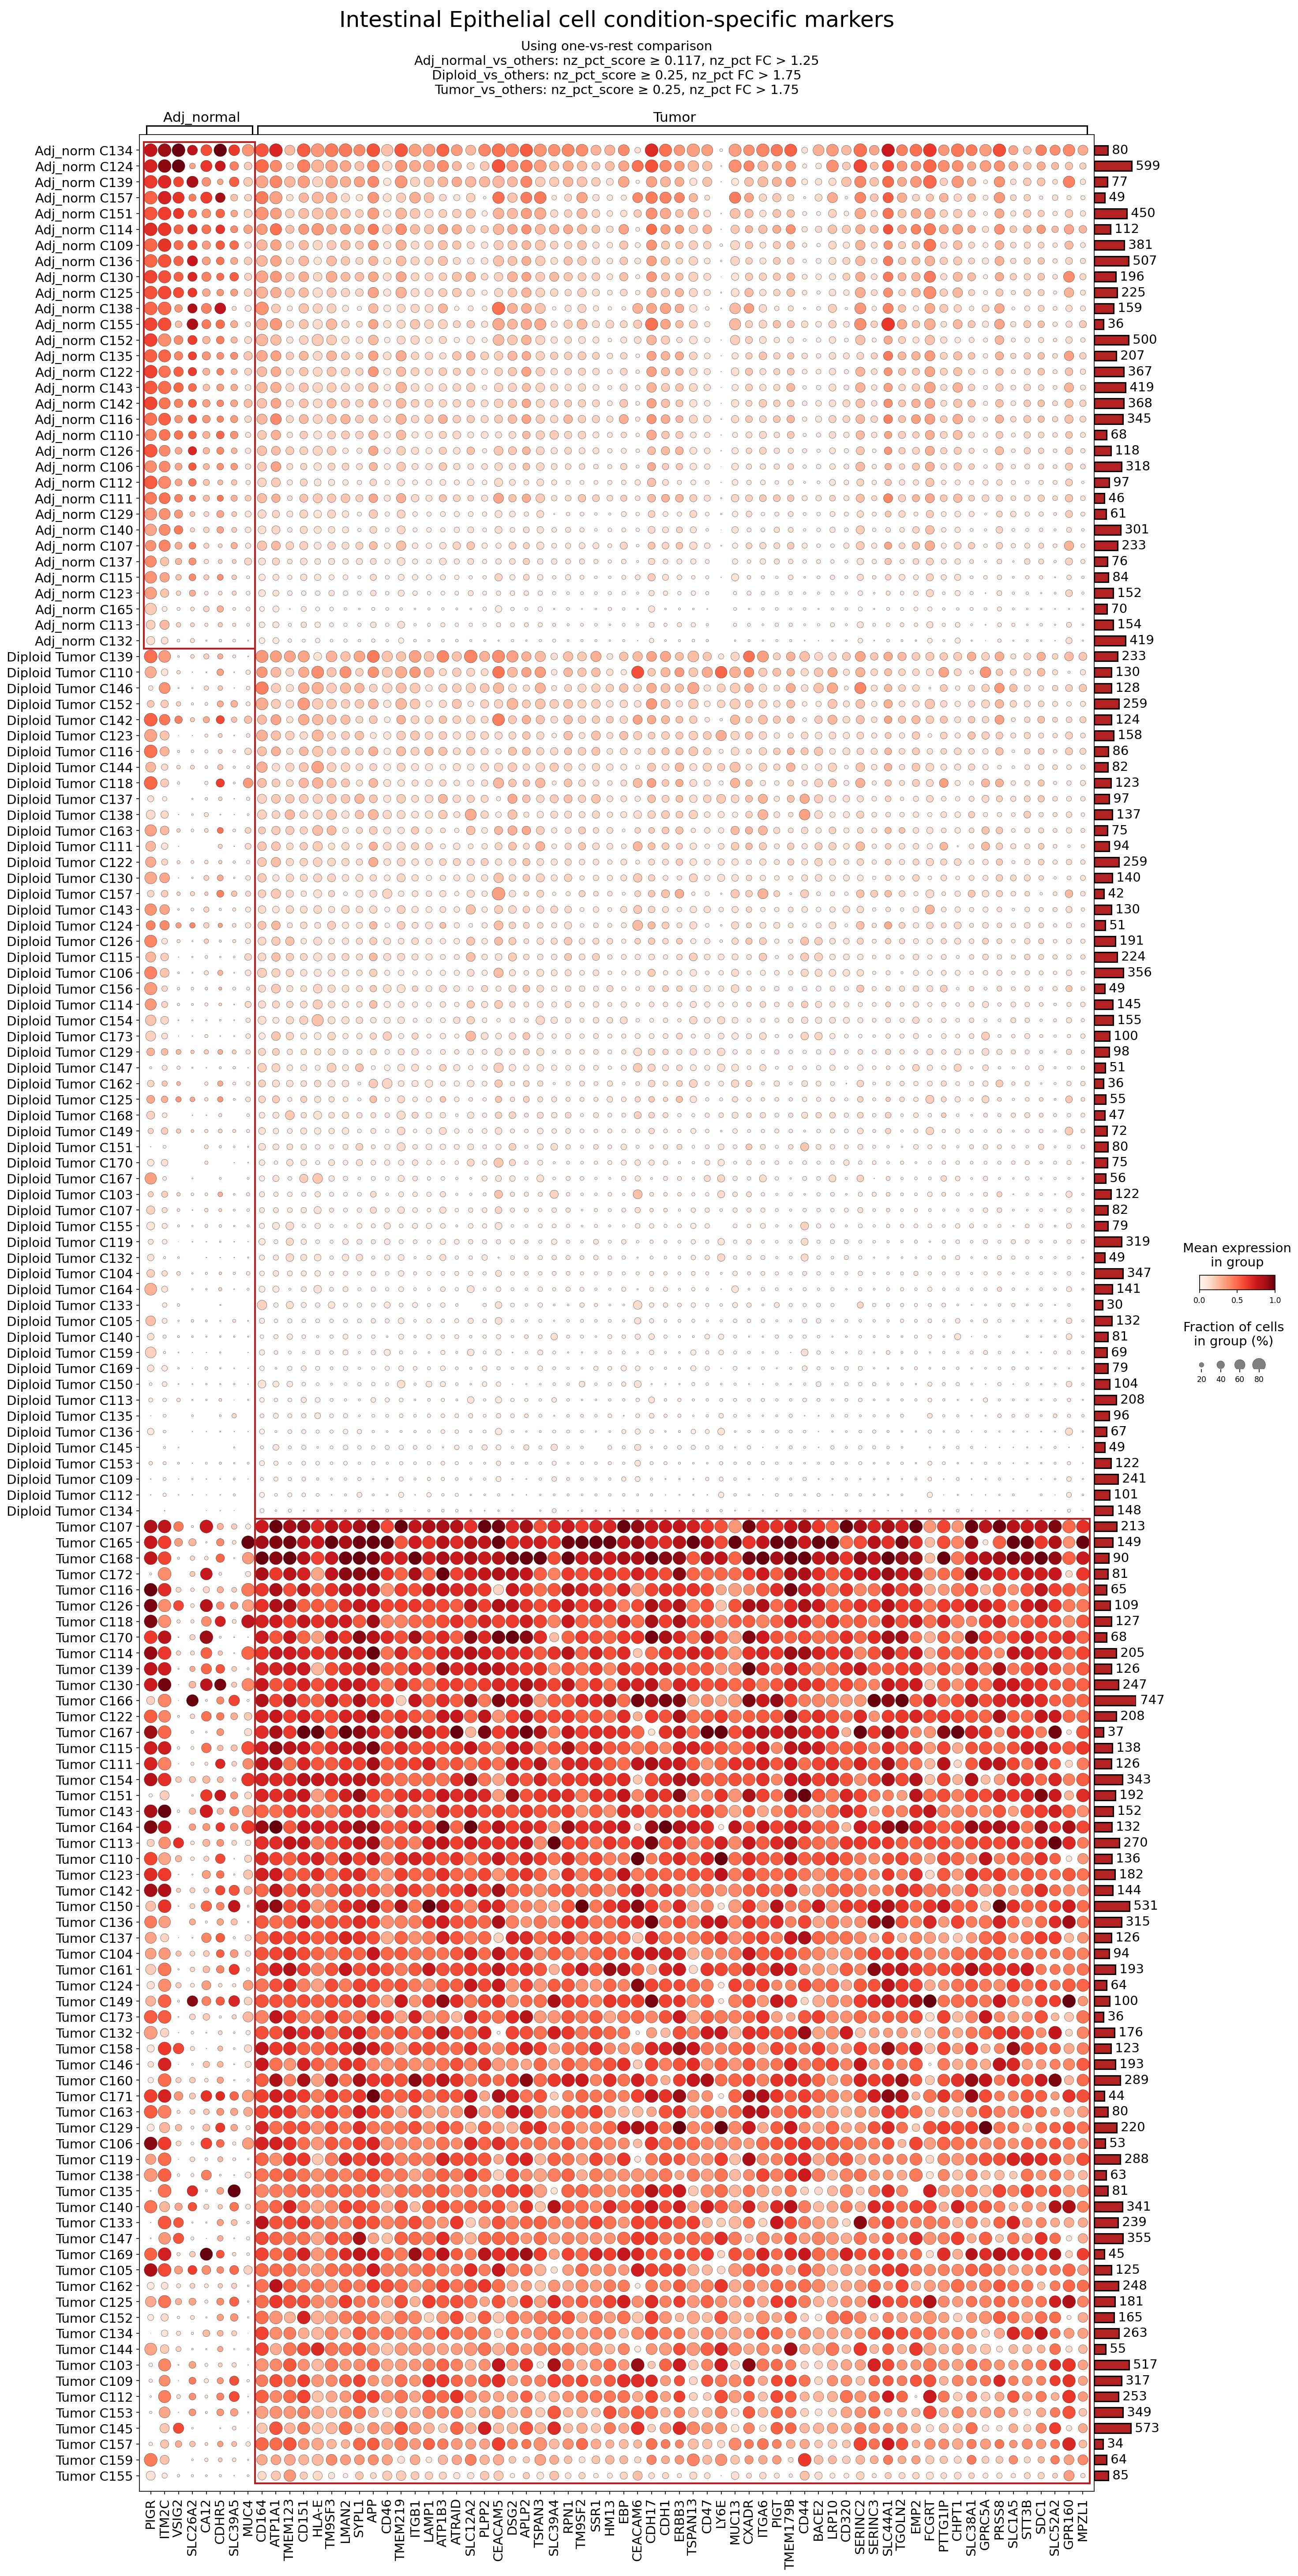
[Analysis Visualization Results]...
Analysis Overview
This analysis identifies and visualizes surfaceome marker gene expression patterns within Intestinal Epithelial cells, comparing "Adj_normal," "Diploid Tumor," and "Tumor" conditions in colorectal tissue. The objective is to identify cell surface markers that distinguish these conditions, particularly focusing on those upregulated in tumor cells, which could represent established or novel therapeutic targets for colorectal cancer. The dot plot displays the mean expression level (color intensity) and the fraction of cells expressing the gene (dot size) for a selected set of surfaceome markers across various individual samples grouped by their condition.
Visual Summary
The dot plot provides a comprehensive overview of surfaceome marker expression across different conditions of Intestinal Epithelial cells.
- Distinct Expression Profiles: Clear differences in gene expression patterns are observed between the "Adj_normal" group and the "Tumor" group, with the "Diploid Tumor" group often showing an intermediate or distinct profile.
- Markers Enriched in Adj_normal Cells: Genes on the left side of the plot, such as PIGR, ITM2C, and VSIG2, demonstrate high mean expression and prevalence primarily within the "Adj_normal" Intestinal Epithelial cells, with significantly lower levels in "Diploid Tumor" and "Tumor" cells. This suggests their role in normal intestinal epithelial function or differentiation, which may be lost during tumorigenesis.
- Markers Highly Upregulated in Tumor Cells: A large cluster of genes towards the right side of the plot shows consistently high mean expression and prevalence across most "Tumor" samples. Notable examples include EPCAM, CEACAM5, CDH17, ERBB3, CD47, LY6E, MUC13, ITGA6, CD44, GPRC5A, and SDC1. This pattern indicates a strong association with the malignant phenotype of Intestinal Epithelial cells in colorectal cancer.
- Diploid Tumor vs. Tumor: While "Diploid Tumor" cells originate from tumor samples, they often exhibit lower expression levels of these tumor-associated markers compared to the "Tumor" group, which likely includes aneuploid malignant cells, suggesting a spectrum of cellular transformation or distinct tumor subpopulations.
- Consistency Across Samples: Within the "Tumor" group, there is relatively consistent high expression and prevalence for many identified markers, indicating common oncogenic processes or adaptations across different tumor samples.
Biological Interpretation
The analysis highlights several surfaceome markers in Intestinal Epithelial cells that are differentially expressed in colorectal cancer, providing insights into tumor biology and potential therapeutic avenues.
Markers Enriched in Adjacent Normal Intestinal Epithelial Cells
- PIGR (Polymeric Immunoglobulin Receptor)
- Associated Signaling/Mechanism: PIGR is a transmembrane protein responsible for translocating polymeric immunoglobulins (IgA and IgM) from the basolateral to the apical surface of epithelial cells, secreting them into the gut lumen. It is critical for mucosal immunity.
- Relevance in Colorectal Cancer: In normal intestinal epithelia, PIGR expression is high. Its significant downregulation in tumor cells (as observed in the plot) can lead to impaired mucosal immunity, potentially contributing to an immune-suppressive tumor microenvironment or a loss of epithelial differentiation.
- Therapeutic Relevance: Not a direct therapeutic target for cancer, but its differential expression serves as a useful marker for distinguishing normal epithelial cells from cancerous ones.
- Supporting Evidence: GeneCards: PIGR
Markers Upregulated in Colorectal Tumor Cells: Established/Emerging Therapeutic Targets
- EPCAM (Epithelial Cell Adhesion Molecule)
- Associated Signaling/Mechanism: EPCAM is a cell surface glycoprotein involved in cell adhesion, proliferation, and differentiation. It can activate Wnt signaling, promoting cell growth and survival, and is implicated in cancer stem cell self-renewal.
- Relevance in Colorectal Cancer: Widely and highly expressed on the surface of most epithelial cancers, including colorectal adenocarcinoma. It serves as a pan-carcinoma marker and is often associated with tumor progression and metastasis.
- Relevant Therapeutic Agents: EPCAM has been an established target for therapeutic antibodies (e.g., catumaxomab for malignant ascites in other cancers). Antibody-drug conjugates (ADCs) and CAR-T cell therapies targeting EPCAM are actively being investigated for various solid tumors.
- Supporting Evidence: GeneCards: EPCAM
- CEACAM5 (Carcinoembryonic Antigen-related Cell Adhesion Molecule 5)
- Associated Signaling/Mechanism: CEACAM5, also known as CEA, is a glycosylphosphatidylinositol (GPI)-anchored cell adhesion molecule. It mediates cell adhesion, can modulate immune responses, and promotes tumor growth, invasion, and metastasis through various pro-survival signaling pathways.
- Relevance in Colorectal Cancer: CEACAM5 is one of the most well-known and widely used tumor markers for monitoring colorectal cancer recurrence, prognosis, and treatment response. Its overexpression is a hallmark of CRC.
- Relevant Therapeutic Agents: Antibody-drug conjugates (ADCs) specifically targeting CEACAM5 (e.g., tusamitamab ravtansine) are in advanced clinical development for CRC and other CEA-positive cancers.
- Supporting Evidence: GeneCards: CEACAM5
- ERBB3 (Erb-B2 Receptor Tyrosine Kinase 3)
- Associated Signaling/Mechanism: ERBB3 (HER3) is a receptor tyrosine kinase and a member of the epidermal growth factor receptor (EGFR) family. While possessing weak intrinsic kinase activity, it forms potent heterodimers with other HER family members (e.g., HER2, EGFR) to activate crucial downstream pathways like PI3K/Akt and MAPK/ERK, driving cell survival, proliferation, and drug resistance.
- Relevance in Colorectal Cancer: Overexpression or activation of ERBB3 is observed in a subset of colorectal cancers and can contribute to tumor growth, progression, and resistance to standard therapies, including EGFR inhibitors.
- Relevant Therapeutic Agents: Anti-HER3 monoclonal antibodies (e.g., patritumab, seribantumab) and HER3-targeting ADCs (e.g., patritumab deruxtecan) are under active clinical investigation for various solid tumors, including CRC.
- Supporting Evidence: GeneCards: ERBB3
- CD47 (Integrin Associated Protein)
- Associated Signaling/Mechanism: CD47 is a transmembrane protein that binds to SIRPα on phagocytic cells (macrophages, dendritic cells), delivering a "don't eat me" signal. This interaction inhibits phagocytosis and allows cancer cells to evade immune surveillance.
- Relevance in Colorectal Cancer: CD47 is frequently overexpressed on the surface of many cancer cells, including those in CRC, serving as a key immune checkpoint by promoting immune evasion and tumor survival.
- Relevant Therapeutic Agents: Anti-CD47 antibodies (e.g., magrolimab) are in clinical trials for solid tumors and hematological malignancies, aiming to block the "don't eat me" signal and stimulate anti-tumor immunity.
- Supporting Evidence: GeneCards: CD47
- CD44 (CD44 Molecule)
- Associated Signaling/Mechanism: CD44 is a multi-functional cell surface glycoprotein involved in cell-cell adhesion, cell-matrix interactions (binding to hyaluronic acid), cell migration, and lymph node homing. It is a well-established marker for cancer stem cells and plays a critical role in tumor initiation, progression, metastasis, and drug resistance by influencing various signaling pathways.
- Relevance in Colorectal Cancer: CD44 and its variant isoforms are frequently overexpressed in CRC, particularly on cancer stem-like cells, and are associated with tumor aggressiveness and metastatic potential.
- Relevant Therapeutic Agents: Targeting CD44 or its interactions is an active area of research. Inhibitors of CD44-hyaluronan interaction and CD44-specific antibodies are being explored as anti-cancer agents.
- Supporting Evidence: GeneCards: CD44
Markers Upregulated in Colorectal Tumor Cells: Novel Therapeutic Target Candidates
- CDH17 (Cadherin 17)
- Associated Signaling/Mechanism: CDH17 is a non-classical cadherin that mediates calcium-dependent cell-cell adhesion. It plays roles in intestinal development and epithelial cell migration. In cancer, its overexpression can promote epithelial-mesenchymal transition (EMT), cell invasion, and metastasis through interactions with various signaling molecules.
- Relevance in Colorectal Cancer: Frequently upregulated in gastrointestinal cancers, including a significant proportion of colorectal cancers. Its overexpression often correlates with advanced disease stages and poor prognosis.
- Therapeutic Potential: Its cell surface localization and oncogenic role make it an attractive candidate for antibody-based therapies or antibody-drug conjugates (ADCs) to specifically target CRC cells.
- Supporting Evidence: GeneCards: CDH17
- MUC13 (Mucin 13, Cell Surface Associated)
- Associated Signaling/Mechanism: MUC13 is a transmembrane mucin that can interact with various signaling proteins through its cytoplasmic tail. It has been shown to promote cancer cell proliferation, survival, migration, and invasion by activating pathways such as MAPK/ERK and PI3K/Akt.
- Relevance in Colorectal Cancer: Overexpressed in a variety of adenocarcinomas, including colorectal cancer, where it is associated with tumor progression and metastasis. Its extracellular domain is accessible for binding by targeting agents.
- Therapeutic Potential: Given its cell surface location and pro-oncogenic functions, MUC13 is being investigated as a target for antibody-based therapies or ADCs to selectively deliver cytotoxic agents to MUC13-positive tumor cells.
- Supporting Evidence: GeneCards: MUC13
- LY6E (Lymphocyte Antigen 6E)
- Associated Signaling/Mechanism: LY6E is a glycosylphosphatidylinositol (GPI)-anchored protein. While its precise signaling mechanisms are still being elucidated, it has been implicated in cell proliferation, survival, and drug resistance. It may play a role in lipid raft-mediated signaling and cell-surface interactions that support tumor growth.
- Relevance in Colorectal Cancer: Elevated expression of LY6E has been observed in various cancers, including CRC, where it is often linked to aggressive tumor phenotypes, metastasis, and poor patient outcomes.
- Therapeutic Potential: Its consistent upregulation on the cell surface of tumor cells makes LY6E a promising candidate for antibody-based targeting, potentially for ADCs or as a novel immunotherapeutic target.
- Supporting Evidence: GeneCards: LY6E
- ITGA6 (Integrin Alpha 6)
- Associated Signaling/Mechanism: ITGA6 is an alpha integrin subunit that forms heterodimers (most commonly with ITGB1 or ITGB4) to create cell surface receptors that bind to laminins in the extracellular matrix. These interactions are crucial for cell adhesion, migration, proliferation, and survival, and play a significant role in cancer stem cell biology, epithelial-mesenchymal transition, and angiogenesis.
- Relevance in Colorectal Cancer: Overexpression and activation of ITGA6-containing integrins are associated with increased tumor aggressiveness, metastasis, and resistance to therapy in various cancers, including CRC.
- Therapeutic Potential: Integrin inhibitors are a class of drugs under development, and specifically targeting ITGA6 could impede tumor growth, block metastatic spread, and potentially sensitize tumor cells to other therapies.
- Supporting Evidence: GeneCards: ITGA6
- SDC1 (Syndecan-1)
- Associated Signaling/Mechanism: SDC1 is a transmembrane heparan sulfate proteoglycan that interacts with growth factors, chemokines, and extracellular matrix components. It modulates various signaling pathways (e.g., FGF, Wnt, HGF) involved in cell proliferation, adhesion, migration, and angiogenesis. Shed SDC1 can also act as a soluble factor.
- Relevance in Colorectal Cancer: Overexpression of SDC1 is common in various cancers, including CRC, where it promotes tumor cell proliferation, survival, angiogenesis, and metastasis. It also plays a role in remodeling the tumor microenvironment.
- Therapeutic Potential: Its pervasive role in tumor biology and cell surface localization makes SDC1 a promising therapeutic target for antibody-based strategies to block its pro-tumorigenic functions or deliver cytotoxic payloads.
- Supporting Evidence: GeneCards: SDC1
Clinical or Translational Implications
The identification of these differentially expressed surfaceome markers in Intestinal Epithelial cells carries significant clinical and translational implications for colorectal cancer:
- Diagnostic and Prognostic Biomarkers: Markers like EPCAM, CEACAM5, and CDH17 could serve as refined diagnostic markers, potentially in liquid biopsies for circulating tumor cells, or as prognostic indicators to predict disease progression and patient outcomes. The combination of multiple surface markers might offer higher specificity and sensitivity.
- Therapeutic Target Identification: The robust upregulation of several surface proteins (EPCAM, CEACAM5, ERBB3, CD47, CD44, CDH17, MUC13, LY6E, ITGA6, SDC1) on tumor-derived Intestinal Epithelial cells highlights them as promising candidates for targeted therapies.
Development of Targeted Therapies:
- Antibody-Drug Conjugates (ADCs): Markers like EPCAM, CEACAM5, ERBB3, CDH17, MUC13, LY6E, SDC1 are ideal candidates for ADCs, which can selectively deliver cytotoxic drugs to tumor cells while sparing healthy tissues.
- Monoclonal Antibodies (mAbs): Therapeutic antibodies targeting CD47 can block immune evasion, while antibodies against other receptors could interfere with pro-tumorigenic signaling or cell adhesion.
- CAR-T Cell Therapy: Highly expressed and tumor-specific surface markers, such as EPCAM, could be utilized as targets for Chimeric Antigen Receptor (CAR) T-cell therapies, enabling immune cells to specifically recognize and eliminate cancer cells.
- Understanding Tumor Heterogeneity: The distinct expression patterns observed between "Diploid Tumor" and "Tumor" (likely aneuploid) cells suggest that different subpopulations within a tumor may exist, requiring varied therapeutic approaches or informing future stratification strategies.
- Personalized Medicine: Characterizing the surfaceome profile of a patient's tumor could guide treatment decisions, allowing for a more personalized approach by selecting therapies that target the specific markers expressed on their tumor cells.
- Monitoring Treatment Response and Relapse: Changes in the expression of these markers could potentially be monitored over time to assess treatment efficacy and detect minimal residual disease or early signs of relapse.
16. Macrophage Surfaceome Markers in Colorectal Cancer
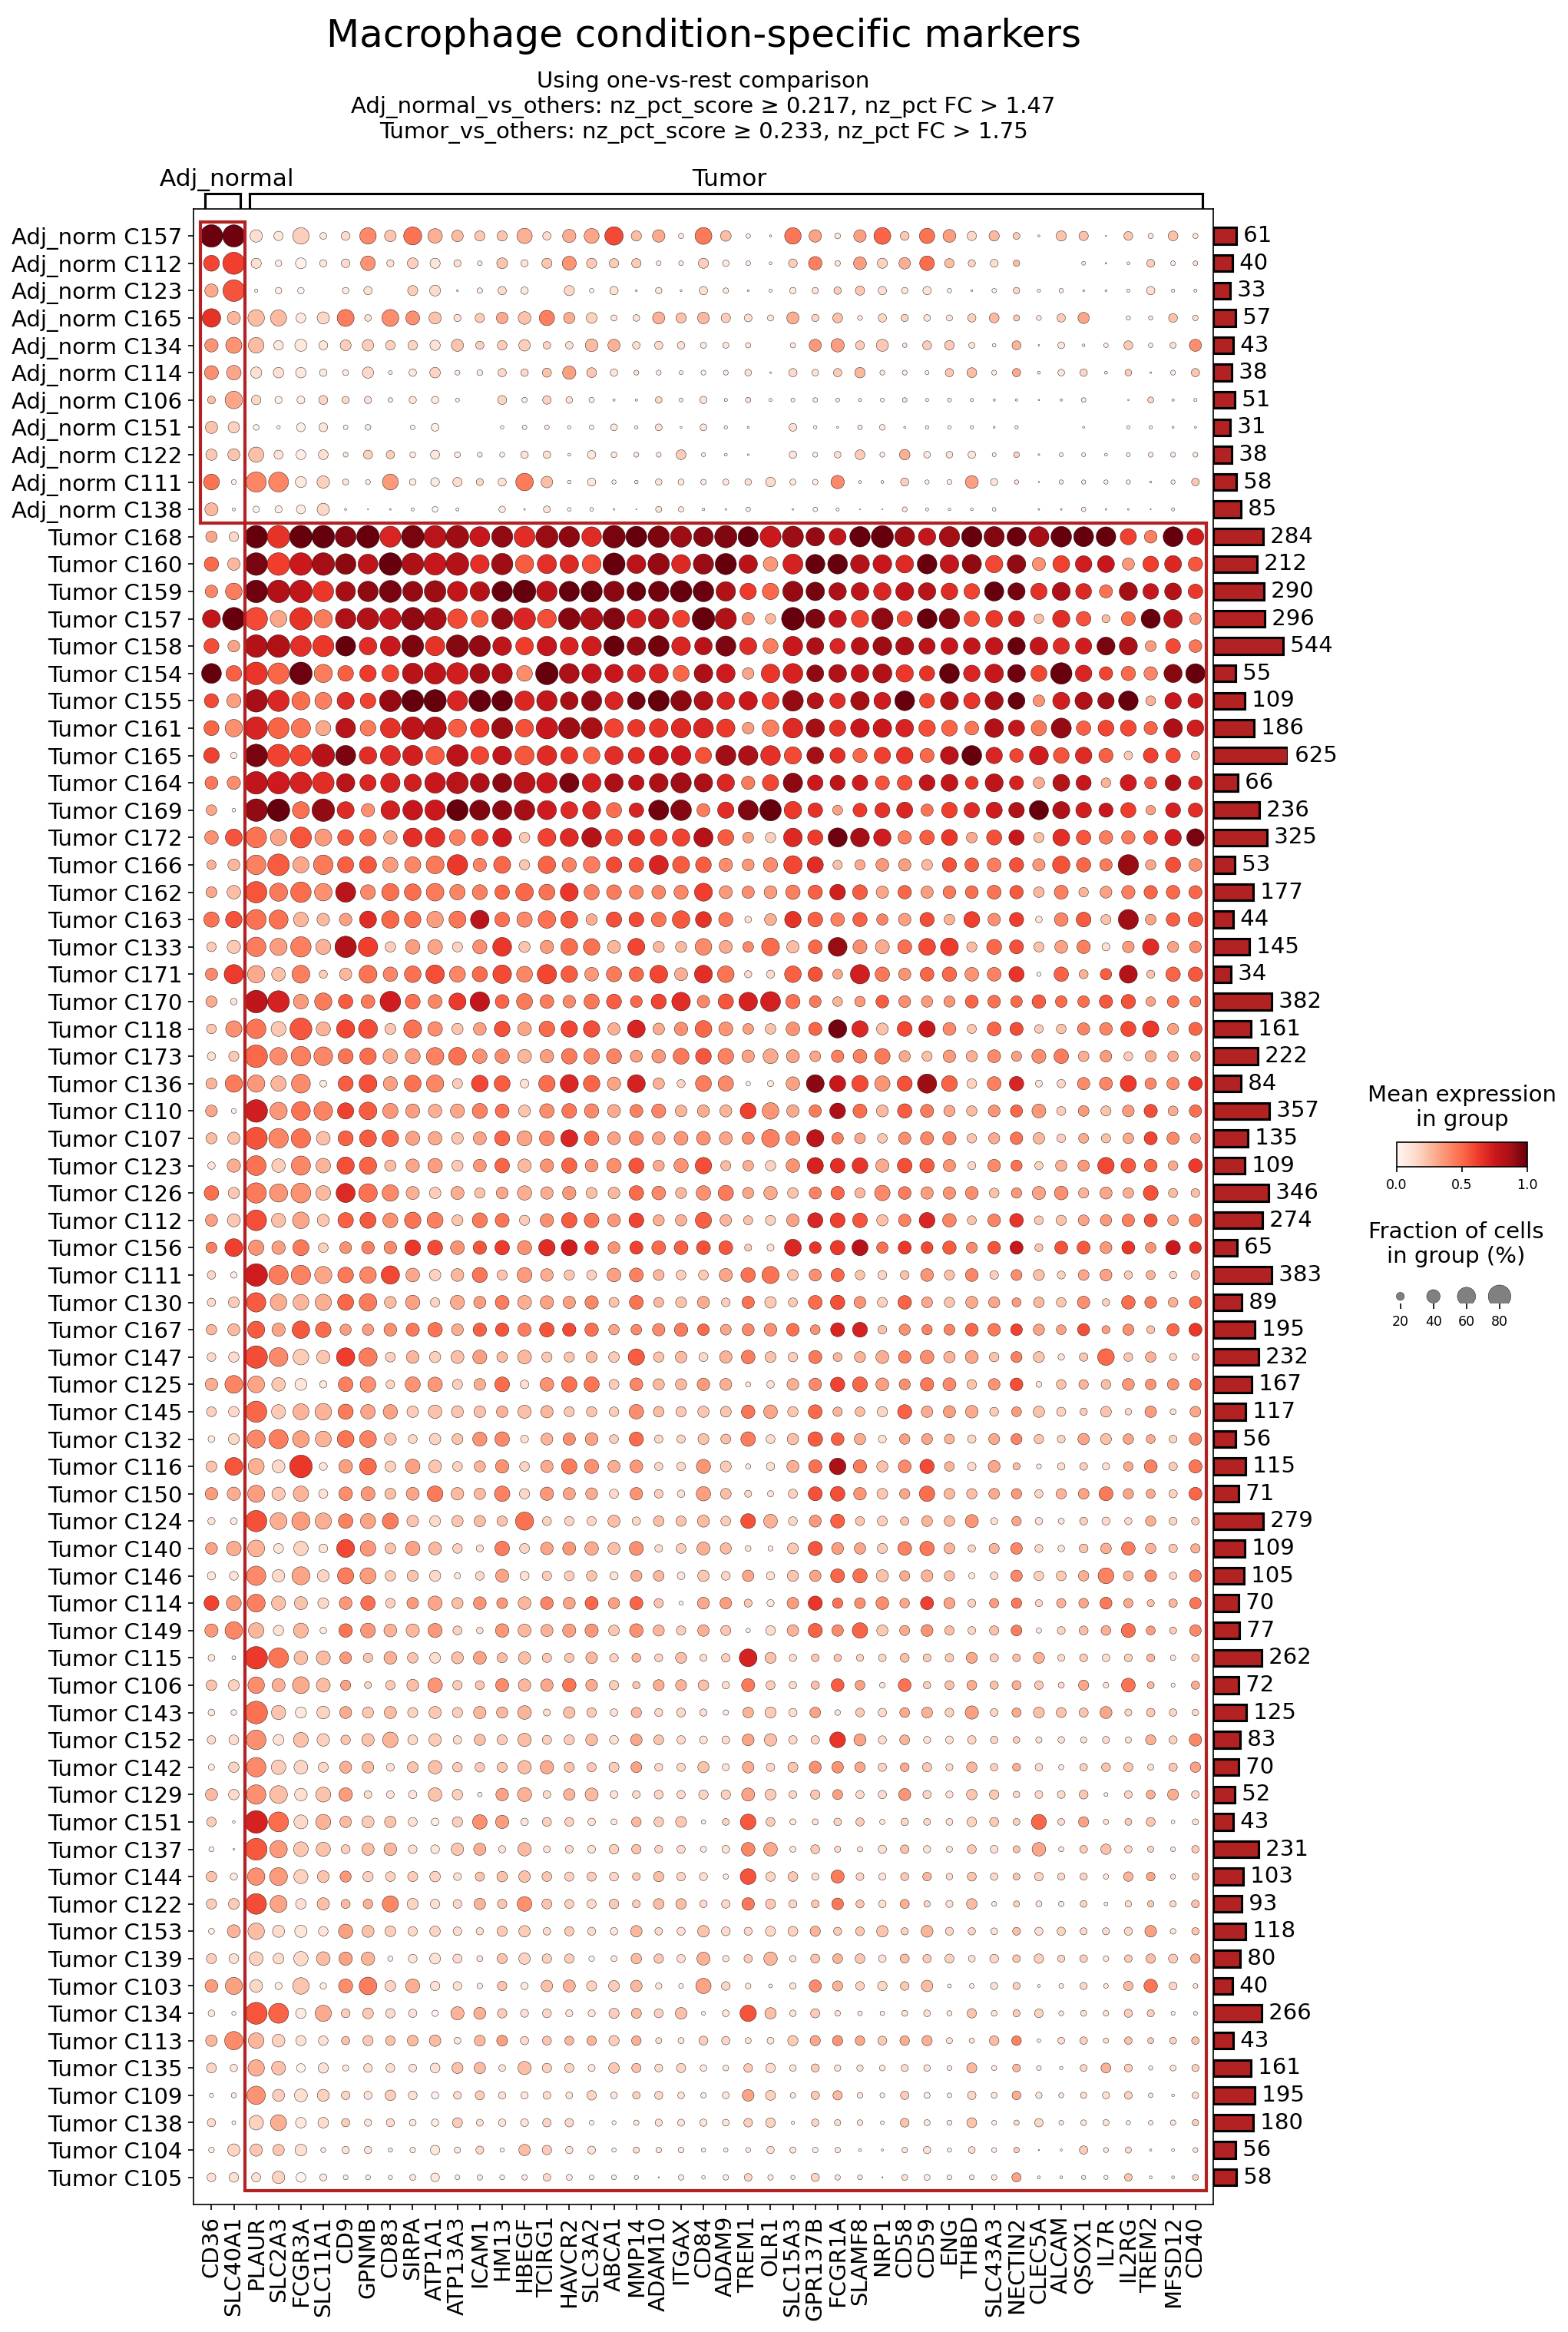
[Analysis Visualization Results]...
Analysis Overview
This analysis identifies condition-specific surfaceome markers for Macrophages in colorectal cancer, comparing cells from tumor tissue (Tumor) to those from adjacent normal tissue (Adj_normal). The goal is to highlight differences in cell surface protein expression that may indicate altered macrophage functions within the tumor microenvironment (TME) and potentially serve as therapeutic targets. The dot plot visualizes the mean expression level (color intensity) and the fraction of cells expressing the marker (dot size) for approximately 40 selected surfaceome markers across individual patient samples.
Visual Summary
The dot plot clearly differentiates macrophage surfaceome marker expression patterns between Adj_normal and Tumor samples.
- Adj_normal Samples: Macrophages from adjacent normal tissue (top section of the plot) generally show low expression (light red or white dots) and a smaller fraction of expressing cells (small or absent dots) for most of the displayed markers. This suggests a relatively quiescent or baseline phenotype for macrophages in healthy colon tissue.
- Tumor Samples: In stark contrast, macrophages from tumor tissue (bottom section of the plot) exhibit significantly higher mean expression (darker red dots) and a larger fraction of expressing cells (larger dots) for a substantial number of markers. This pattern is consistent across many individual tumor samples, indicating a robust and widespread shift in macrophage phenotype within the colorectal cancer TME.
- Highly Expressed Tumor Markers: Several markers, including CD36, PLAUR, GPNMB, HM13, HBEGF, ITGAX (CD11c), CD84, TREM1, OLR1, CD59, THBD, NECTIN2, CLEC5A, and CD40, show particularly strong and widespread expression in tumor macrophages compared to adjacent normal macrophages. These markers represent potential candidates for further investigation due to their pronounced differential expression.
- Heterogeneity within Tumor Samples: While a general trend of elevated expression in tumor macrophages is evident, there is also some heterogeneity among individual tumor samples. Some samples show higher overall expression for a wider array of markers, while others display more restricted patterns, suggesting patient-specific variations in the tumor-associated macrophage (TAM) phenotype.
- Cell Counts: The bar plot on the right indicates the number of macrophage cells per sample, showing that most tumor samples have a sufficient number of cells (often several hundreds) to reliably assess marker expression, while adjacent normal samples tend to have fewer macrophages.
Biological Interpretation
Macrophages are critical components of the tumor microenvironment (TME) and undergo extensive reprogramming in cancer, becoming tumor-associated macrophages (TAMs). This shift from anti-tumor (M1-like) to pro-tumor (M2-like) phenotypes is often characterized by the expression of specific surface markers. The observed upregulation of numerous surfaceome markers in macrophages from colorectal cancer samples suggests a prominent TAM phenotype associated with tumor progression.
The inferred disease context of Colorectal Cancer further emphasizes the importance of understanding TAM biology. In CRC, TAMs promote tumor growth, angiogenesis, immune suppression, invasion, and metastasis, often correlating with poor patient prognosis. The differentially expressed markers identified here likely play roles in these pro-tumorigenic functions.
Let's delve into some notable markers highly expressed in tumor macrophages:
CD36
- Signaling Pathways: CD36 is a scavenger receptor involved in lipid metabolism, particularly fatty acid uptake and transport. It can interact with various ligands, including oxidized low-density lipoproteins (oxLDL) and thrombospondin-1 (TSP-1). Signaling through CD36 can activate downstream pathways like MAPK and Akt, influencing cell survival and differentiation.
- Role in TME: In the TME, CD36-expressing macrophages are often associated with an immunosuppressive, pro-tumorigenic phenotype. CD36 promotes lipid accumulation in TAMs, which can fuel their metabolic reprogramming and suppress anti-tumor immune responses. It also contributes to angiogenesis and metastasis. In colorectal cancer, high CD36 expression on TAMs can drive tumor progression.
- Therapeutic Potential: Targeting CD36 could inhibit lipid metabolism in TAMs, thereby reducing their pro-tumorigenic functions and potentially sensitizing tumors to other therapies.
- Therapeutic Agents: Small molecule inhibitors targeting CD36 are under investigation, aiming to disrupt fatty acid metabolism in cancer cells and associated immune cells.
- Other Information: CD36 expression is also found on endothelial cells and some tumor cells, where it mediates lipid uptake critical for tumor growth and metastasis. GeneCards: CD36
PLAUR (uPAR)
- Signaling Pathways: PLAUR (Urokinase-type Plasminogen Activator Receptor) binds to uPA (urokinase-type plasminogen activator), initiating a cascade that converts plasminogen to plasmin. This leads to the degradation of extracellular matrix (ECM) components. PLAUR also interacts with integrins, triggering signaling pathways that influence cell adhesion, migration, and proliferation.
- Role in TME: Upregulation of PLAUR on TAMs promotes tissue remodeling, ECM degradation, and facilitates cell migration and invasion, which are crucial for tumor dissemination and metastasis. It also contributes to angiogenesis by promoting endothelial cell migration.
- Therapeutic Potential: Inhibiting PLAUR/uPA signaling could reduce TAM-mediated ECM degradation and tumor cell invasion, hindering metastasis and angiogenesis.
- Therapeutic Agents: Antibodies and small molecule inhibitors targeting uPA or uPAR have been developed to block this pro-tumorigenic axis.
- Other Information: PLAUR expression is highly correlated with aggressive tumor phenotypes and poor prognosis in various cancers, including CRC. GeneCards: PLAUR
GPNMB
- Signaling Pathways: Glycoprotein Non-metastatic B (GPNMB) is a transmembrane glycoprotein that can be cleaved and released as a soluble factor. It contains an integrin-binding RGD motif and can modulate cell adhesion and motility. Its intracellular domain can interact with various signaling molecules, influencing cellular growth and survival, potentially through pathways like Akt/mTOR.
- Role in TME: GPNMB is often expressed by immunosuppressive TAMs and has been linked to immune evasion, angiogenesis, and metastasis. It can promote the M2 polarization of macrophages and suppress T cell responses. In CRC, GPNMB expression in TAMs might contribute to an immunosuppressive environment.
- Therapeutic Potential: GPNMB is an attractive target due to its restricted expression in normal tissues and high expression in various tumors and TAMs. An antibody-drug conjugate (ADC) targeting GPNMB has shown efficacy in melanoma.
- Therapeutic Agents: Glembatumumab vedotin is an ADC targeting GPNMB.
- Other Information: GPNMB overexpression is observed in multiple cancers, including melanoma, glioblastoma, and breast cancer, and often correlates with advanced disease. GeneCards: GPNMB
HBEGF
- Signaling Pathways: Heparin-binding EGF-like growth factor (HBEGF) is a member of the epidermal growth factor (EGF) family. It binds to and activates EGF receptor (EGFR) and ERBB4, leading to the activation of downstream pathways such as RAS/MAPK, PI3K/Akt, and STAT pathways, which are critical for cell proliferation, survival, migration, and angiogenesis.
- Role in TME: HBEGF expressed by TAMs can act as a potent paracrine growth factor, stimulating the proliferation and survival of tumor cells and endothelial cells, thereby promoting tumor growth and angiogenesis. It also contributes to tissue repair and wound healing processes that can be hijacked by tumors.
- Therapeutic Potential: Targeting HBEGF or its receptors (EGFR) could inhibit tumor growth and angiogenesis driven by TAM-secreted factors.
- Therapeutic Agents: EGFR inhibitors (e.g., cetuximab, panitumumab) are standard treatments for CRC, and targeting HBEGF directly could be another strategy to block EGFR signaling.
- Other Information: HBEGF is also involved in cardiac hypertrophy, gastric acid secretion, and cell migration during development. GeneCards: HBEGF
CD40
- Signaling Pathways: CD40 is a co-stimulatory receptor belonging to the TNF receptor superfamily. Its ligation by CD40L (CD154) on T cells or other immune cells activates downstream signaling through TRAF proteins, leading to NF-κB activation and subsequent gene expression related to inflammation, immune cell activation, and antigen presentation.
- Role in TME: While CD40 activation on antigen-presenting cells (APCs) generally promotes anti-tumor immunity, its role on TAMs can be complex. CD40 expression on TAMs can indicate their potential to be reprogrammed towards an M1-like phenotype or to interact with T cells. However, in an immunosuppressive TME, CD40 signaling on TAMs might also contribute to chronic inflammation or mediate interactions that ultimately promote tumor growth. Its high expression suggests a state of activation or interaction within the TME.
- Therapeutic Potential: Agonistic anti-CD40 antibodies are being investigated as immunotherapeutic agents to activate anti-tumor immune responses, particularly in combination with checkpoint inhibitors or chemotherapy. Activating CD40 on TAMs could potentially shift them towards an anti-tumor phenotype.
- Therapeutic Agents: Several CD40 agonist antibodies (e.g., sotiga, selicrelumab) are in clinical trials for various cancers.
- Other Information: CD40 is broadly expressed on various immune cells, including B cells, dendritic cells, and macrophages. GeneCards: CD40
Other noteworthy markers:
- ITGAX (CD11c): An integrin subunit often associated with dendritic cells and a subset of macrophages, involved in cell adhesion and migration. Its high expression in tumor macrophages might reflect their migratory potential or interaction with other ECM components. GeneCards: ITGAX
- TREM1: A receptor expressed on myeloid cells, typically amplifying inflammatory responses. Its presence on TAMs could indicate a pro-inflammatory component that is co-opted by the tumor to promote growth and immune evasion. GeneCards: TREM1
- CD59: A complement regulatory protein that protects host cells from complement-mediated lysis. Overexpression on TAMs could contribute to immune evasion by protecting them from complement attack. GeneCards: CD59
The overall pattern of increased surface marker expression in tumor-associated macrophages points towards their active engagement in diverse pro-tumor functions within the colorectal cancer microenvironment.
Clinical or Translational Implications
The distinct surfaceome expression profile of macrophages in colorectal cancer compared to adjacent normal tissue offers several clinical and translational opportunities:
- Biomarker Discovery: These differentially expressed surface markers could serve as diagnostic or prognostic biomarkers for colorectal cancer, potentially reflecting the infiltration and activation state of TAMs.
- Therapeutic Targeting: Markers highly and specifically expressed on TAMs, such as CD36, PLAUR, GPNMB, HBEGF, and CD40, represent promising therapeutic targets. Strategies could involve:
- Antibody-drug conjugates (ADCs): Delivering cytotoxic agents directly to TAMs expressing these markers (e.g., GPNMB-targeting ADCs).
- Blocking antibodies: Inhibiting the pro-tumorigenic functions of these receptors (e.g., PLAUR inhibition to reduce invasion, HBEGF inhibition to reduce growth factor signaling).
- Immunomodulatory antibodies: Reprogramming TAMs to an anti-tumor phenotype (e.g., CD40 agonists to activate anti-tumor immunity).
- Targeting Macrophage Infiltration/Survival: Understanding the signaling pathways associated with these markers could lead to strategies to inhibit macrophage recruitment to the tumor or reduce their survival within the TME.
- Combination Therapies: Targeting TAMs through these markers could synergize with existing immunotherapies (e.g., checkpoint inhibitors) or chemotherapy, potentially overcoming resistance mechanisms mediated by the TME.
- Patient Stratification: Heterogeneity in marker expression across tumor samples suggests that therapeutic approaches targeting specific TAM phenotypes might be more effective in subsets of patients, necessitating further investigation into patient stratification.
These findings underscore the importance of TAMs as a therapeutic target in colorectal cancer and provide specific surfaceome markers as candidates for the development of novel anti-cancer agents.
17. Fibroblast Condition-Specific Surfaceome Markers in Colorectal Cancer
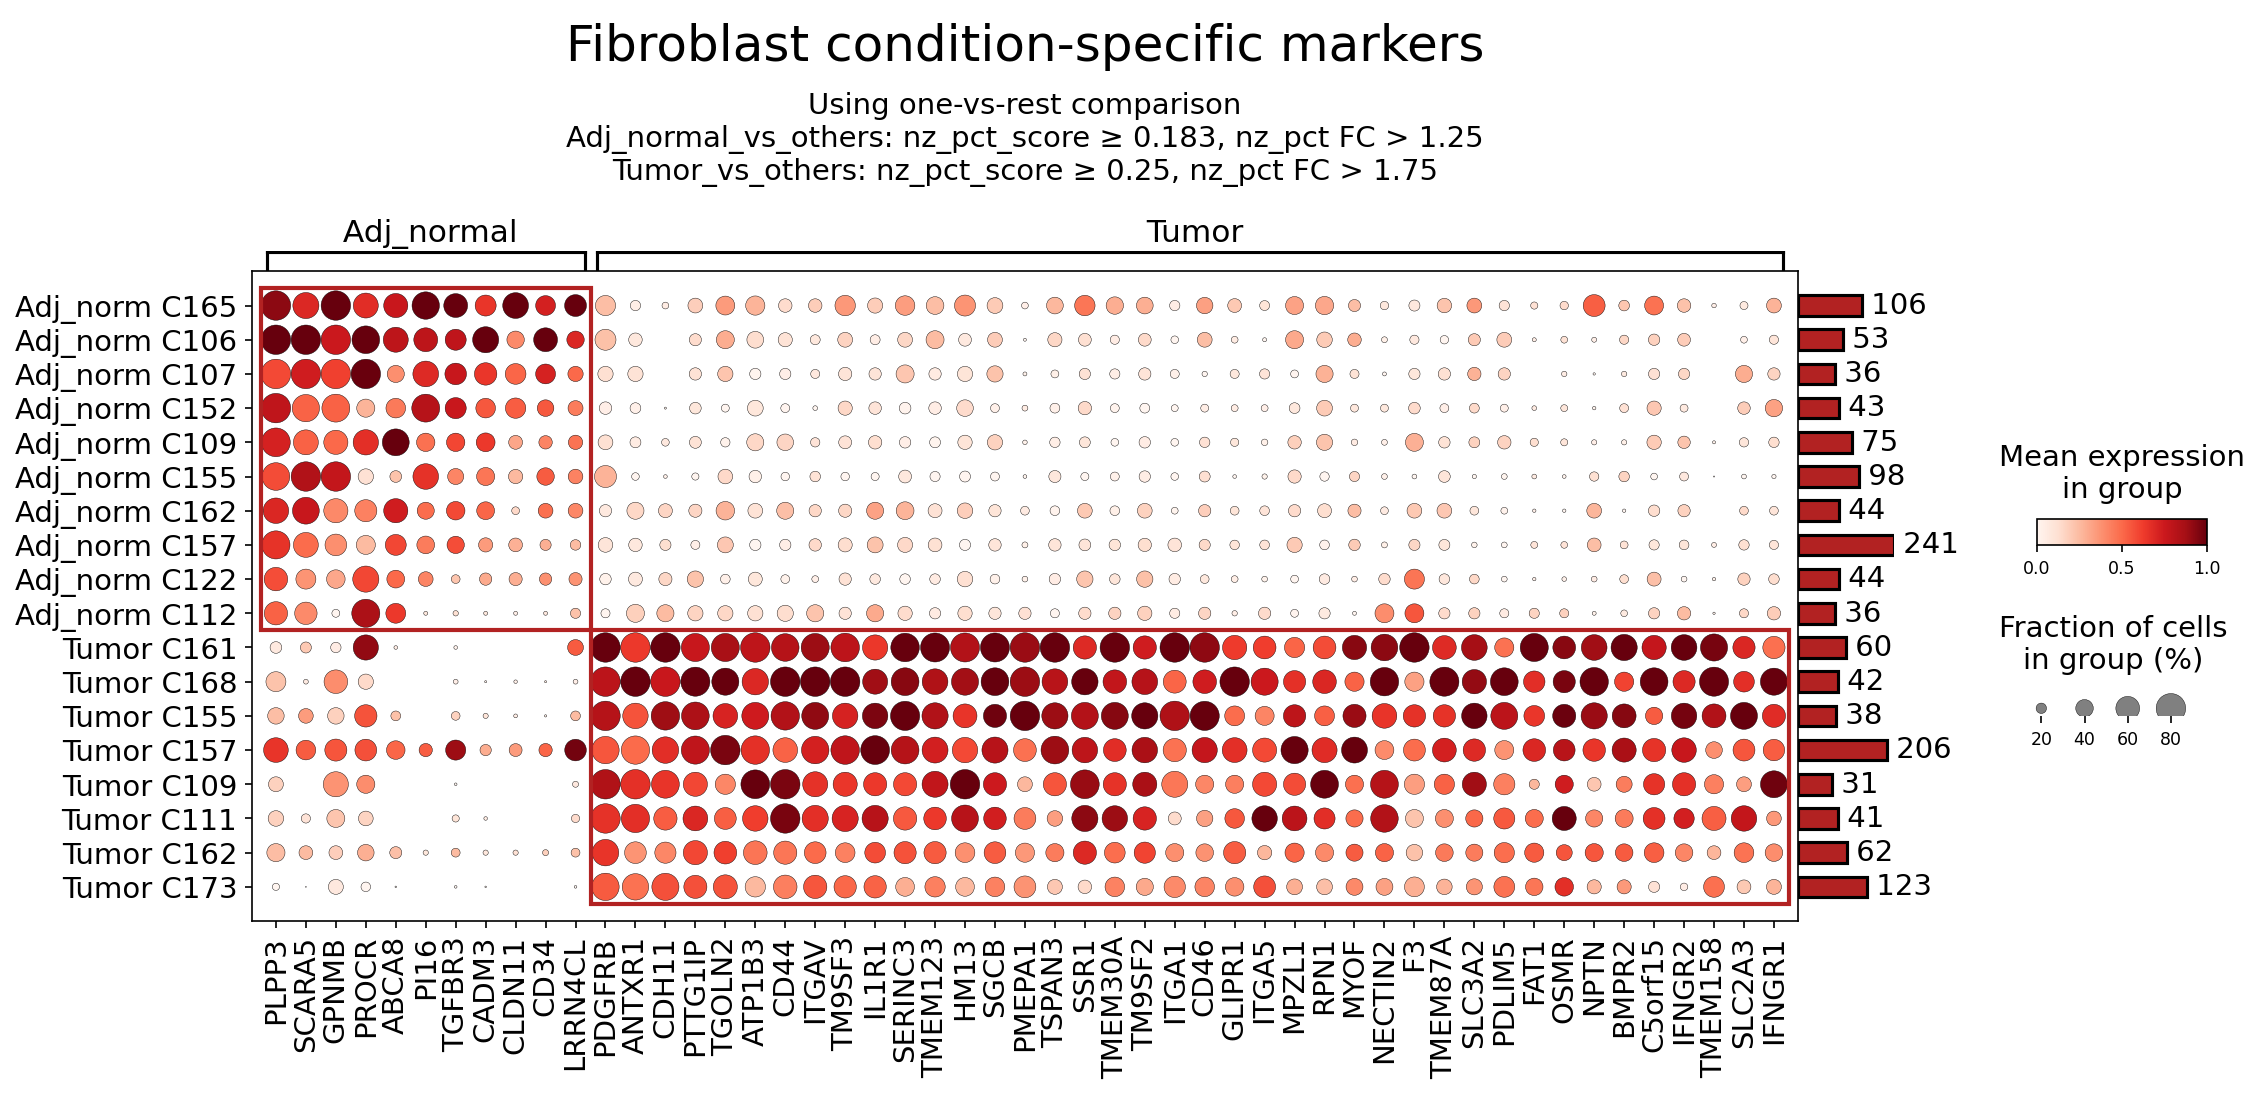
[Analysis Visualization Results]...
Analysis Overview
This analysis identifies surfaceome markers differentially expressed in Fibroblasts from colorectal cancer 'Tumor' tissue compared to 'Adj_normal' tissue. The dot plot visualizes the expression of these markers across various patient samples within each condition. This approach helps to distinguish normal fibroblasts from cancer-associated fibroblasts (CAFs) based on their surface protein profiles, offering potential insights into CAF biology and therapeutic targeting. The analysis focused on surfaceome markers, prioritizing those with a strong presence and high expression in one condition relative to the other.
Visual Summary
The dot plot displays the mean expression (color intensity) and fraction of cells expressing (dot size) for selected surfaceome markers within Fibroblast populations from individual 'Adj_normal' and 'Tumor' samples.
- Distinct Marker Profiles: There is a clear segregation of marker expression patterns between 'Adj_normal' and 'Tumor' fibroblasts.
- Adj_normal Fibroblasts: A set of markers, including PLPP3, SCARA5, PROCR, ABCA8, GPNMB, PI16, CD34, CLDN11, LRRN4CL, TGFBR3, CADM3, show high mean expression and high prevalence (large, dark red dots) predominantly in the 'Adj_normal' samples. These markers are largely absent or expressed at very low levels in 'Tumor' fibroblasts.
- Tumor Fibroblasts: A much larger and distinct set of markers is highly expressed and prevalent in 'Tumor' samples. Prominent examples include PDGFRB, ANTXR1, CDH11, PTTG1IP, TGOLN2, ATP1B3, CD44, ITGAV, IL1R1, SERINC3, TMEM123, SGCB, PMEPA1, TSPAN3, SSR1, TMEM30A, ITGA1, CD46, GLIPR1, ITGA5, MPZL1, RPN1, MYOF, NECTIN2, F3, TMEM87A, SLC3A2, PDLIM5, FAT1, OSMR, NPTN, BMPR2, C5orf15, IFNGR2, TMEM158, SLC2A3, and IFNGR1. These markers show strong expression (dark red dots) and widespread presence (large dots) across most 'Tumor' samples, while being largely absent in 'Adj_normal' samples.
- Consistency Across Samples: Within each condition, the expression patterns for the identified markers are largely consistent across different patient samples, indicating robust condition-specific signatures.
- Quantitative Metrics: The red bar plots on the right indicate the total number of cells analyzed for each sample. The color scale indicates mean expression from 0 to 1, and the dot size indicates the fraction of cells expressing from 20% to 80%.
Biological Interpretation
The distinct surfaceome profiles of Fibroblasts in 'Adj_normal' versus 'Tumor' contexts reflect the profound phenotypic changes associated with their activation into cancer-associated fibroblasts (CAFs) within the colorectal tumor microenvironment.
Markers Enriched in Adj_normal Fibroblasts
These markers are indicative of quiescent or homeostatic fibroblast functions. Their downregulation in the tumor setting suggests a loss of normal tissue identity or function during CAF activation.
- PLPP3 (Phospholipid Phosphatase 3): This lipid phosphatase is involved in sphingolipid metabolism, particularly the hydrolysis of lysophosphatidic acid (LPA) and sphingosine-1-phosphate (S1P). By reducing bioactive lipid signaling molecules, PLPP3 can suppress cell proliferation, migration, and angiogenesis. Its robust expression in normal fibroblasts suggests a role in maintaining tissue homeostasis and potentially suppressing pro-tumorigenic lipid signaling pathways in the non-malignant context. GeneCards: PLPP3
- SCARA5 (Scavenger Receptor Class A Member 5): A transmembrane scavenger receptor that mediates cell adhesion and can modulate cell growth. SCARA5 has been implicated as a tumor suppressor in various cancers, often inhibiting cell proliferation and migration. Its presence on normal fibroblasts suggests a role in maintaining tissue integrity and potentially preventing uncontrolled growth, functions that may be lost in CAFs. GeneCards: SCARA5
- PROCR (Protein C Receptor, Endothelial): While primarily known as an endothelial protein C receptor involved in coagulation and inflammation, PROCR can also be expressed on mesenchymal stem cells and fibroblasts, where it may contribute to stemness or tissue repair. In normal fibroblasts, it could play a role in regulating inflammation or maintaining progenitor-like characteristics. GeneCards: PROCR
- CLDN11 (Claudin-11): A component of tight junctions, Claudin-11 is essential for maintaining cell polarity and barrier function in epithelial tissues, but also in some mesenchymal cells. Its expression in normal fibroblasts implies a role in maintaining tissue architecture and cell-cell adhesion, characteristics that are often disrupted as fibroblasts become activated into CAFs. GeneCards: CLDN11
Markers Enriched in Tumor Fibroblasts
The upregulation of these markers in tumor fibroblasts signifies their activated state (CAFs) and their active participation in remodeling the tumor microenvironment (TME), supporting tumor growth, angiogenesis, and metastasis.
- PDGFRB (Platelet-Derived Growth Factor Receptor Beta): A receptor tyrosine kinase that is a hallmark of activated fibroblasts and pericytes. Upon binding PDGF ligands (often secreted by tumor cells or other TME cells), PDGFRB signaling drives fibroblast proliferation, migration, extracellular matrix (ECM) production, and angiogenesis. It is a critical mediator of desmoplasia and fibrotic responses in cancer. GeneCards: PDGFRB
- CDH11 (Cadherin-11): Also known as OB-cadherin, CDH11 is a type II classical cadherin involved in homophilic cell-cell adhesion. In CAFs, CDH11 promotes cell migration and invasion, contributing to the invasive front of tumors and facilitating metastasis. It can also modulate mechanosensing and ECM remodeling. GeneCards: CDH11
- CD44: A widely expressed cell surface glycoprotein that acts as a primary receptor for hyaluronic acid (HA), a major component of the ECM. CD44 engagement is crucial for cell adhesion, migration, proliferation, and survival. In CAFs, CD44 contributes to ECM remodeling, modulates growth factor signaling (e.g., interaction with EGFR), and is often associated with pro-tumorigenic properties and stemness. GeneCards: CD44
- ITGAV (Integrin Subunit Alpha V): Integrins are heterodimeric cell surface receptors that mediate cell-ECM and cell-cell adhesion, and bidirectional signaling. ITGAV, in complex with various beta subunits (e.g., ITGB1, ITGB3, ITGB5, ITGB6), recognizes RGD motifs in ECM proteins (like fibronectin, vitronectin, osteopontin). In CAFs, ITGAV-containing integrins are vital for sensing and remodeling the stiff tumor ECM, regulating CAF migration, proliferation, and secretion of pro-tumorigenic factors. GeneCards: ITGAV
- F3 (Coagulation Factor III / Tissue Factor): The primary initiator of the extrinsic coagulation cascade, F3 is often aberrantly expressed by tumor cells and CAFs. Beyond its role in hemostasis, F3 contributes to tumor biology by promoting angiogenesis, inflammation, and metastasis through activation of protease-activated receptors (PARs) and cross-talk with other signaling pathways. GeneCards: F3
- OSMR (Oncostatin M Receptor): The receptor for Oncostatin M (OSM), a cytokine of the IL-6 family. Activation of OSMR in CAFs leads to downstream signaling (e.g., JAK/STAT, MAPK, PI3K), driving inflammation, ECM deposition, and pro-tumorigenic processes such as angiogenesis and immunosuppression within the TME. GeneCards: OSMR
- IL1R1 (Interleukin 1 Receptor Type 1): The receptor for IL-1α and IL-1β, which are potent pro-inflammatory cytokines. Upregulation of IL1R1 on CAFs indicates their responsiveness to inflammatory signals from the tumor and immune cells. IL-1R1 signaling activates NF-κB and MAPK pathways, promoting the secretion of chemokines, cytokines, and matrix metalloproteinases, thereby fueling inflammation and driving CAF activation and tumor progression. GeneCards: IL1R1
Clinical or Translational Implications
The identification of distinct surfaceome marker profiles for 'Adj_normal' versus 'Tumor' fibroblasts provides valuable insights for diagnostic, prognostic, and therapeutic strategies in colorectal cancer.
Diagnostic and Prognostic Biomarkers
- CAF-specific markers such as PDGFRB, CDH11, CD44, ITGAV, F3, OSMR, and IL1R1 could serve as diagnostic markers for identifying and quantifying CAFs in colorectal cancer biopsies, potentially aiding in tumor staging and prognosis. High levels of CAF infiltration and specific CAF phenotypes (indicated by these markers) are often associated with aggressive disease and poor patient outcomes in various cancers, including colorectal cancer.
- The relative abundance of Adj_normal fibroblast markers versus Tumor fibroblast markers might indicate the extent of stromal reprogramming and could be developed into prognostic indicators.
Therapeutic Targets
The surface localization of these markers makes them highly accessible for targeted therapies.
- PDGFRB: Given its critical role in CAF activation and desmoplasia, PDGFRB is an attractive therapeutic target. Multi-kinase inhibitors (e.g., imatinib, sunitinib) that target PDGFR have been explored in various cancers. More specific PDGFRB inhibitors could be developed to deplete or reprogram CAFs, thereby reducing stromal support for tumor growth and improving drug delivery by modulating ECM density. PubMed search: PDGFRB CAF therapy
- CDH11: Targeting CDH11 could inhibit CAF migration and tumor invasion. Monoclonal antibodies against CDH11 are under investigation for fibrotic diseases and may translate to cancer therapy by disrupting CAF-mediated remodeling of the TME. PubMed search: CDH11 cancer therapy
- CD44: As a receptor involved in multiple pro-tumorigenic pathways and often associated with cancer stem cells, CD44 is a promising target. Antibodies against CD44 are being investigated to block its pro-adhesive and signaling functions, potentially inhibiting CAF activity and cancer stemness. PubMed search: CD44 cancer therapy
- ITGAV: Inhibitors targeting αv integrins (e.g., cilengitide) have been developed, aiming to disrupt cell-ECM interactions crucial for tumor cell and CAF migration, invasion, and angiogenesis. While clinical success has been mixed, combination therapies or novel integrin-targeting approaches could prove beneficial. PubMed search: ITGAV integrin cancer therapy
- F3 (Tissue Factor): Inhibition of F3, which plays a role in coagulation and non-hemostatic pro-tumorigenic signaling, could reduce tumor-associated thrombosis, angiogenesis, and metastasis. Therapeutic agents like anti-F3 antibodies are being explored. PubMed search: F3 cancer therapy
- OSMR and IL1R1: Targeting inflammatory pathways mediated by OSMR and IL1R1 could dampen the pro-inflammatory TME, inhibit CAF activation, and potentially reduce tumor growth and metastasis. Small molecule inhibitors or blocking antibodies against OSM, IL-1, or their receptors could be considered. PubMed search: OSMR cancer therapy; PubMed search: IL1R1 cancer therapy
Experimental Validation
These identified markers represent excellent candidates for further experimental validation.
- _in vitro_ studies: Using patient-derived CAFs or fibroblast cell lines, the functional impact of modulating these markers (e.g., using siRNA, CRISPR, or specific inhibitors/agonists) on CAF proliferation, migration, ECM production, and interaction with tumor cells could be investigated.
- _in vivo_ models: Employing genetically engineered mouse models of colorectal cancer or patient-derived xenograft (PDX) models, the therapeutic efficacy of targeting these markers on CAFs could be assessed, including effects on tumor growth, metastasis, and response to standard therapies.
- Spatial transcriptomics/proteomics: Further studies could investigate the spatial localization of these markers within the colorectal TME to understand their precise roles in different anatomical regions of the tumor.
18. T cell CD4+ Condition-Specific Surfaceome Markers in Colorectal Cancer
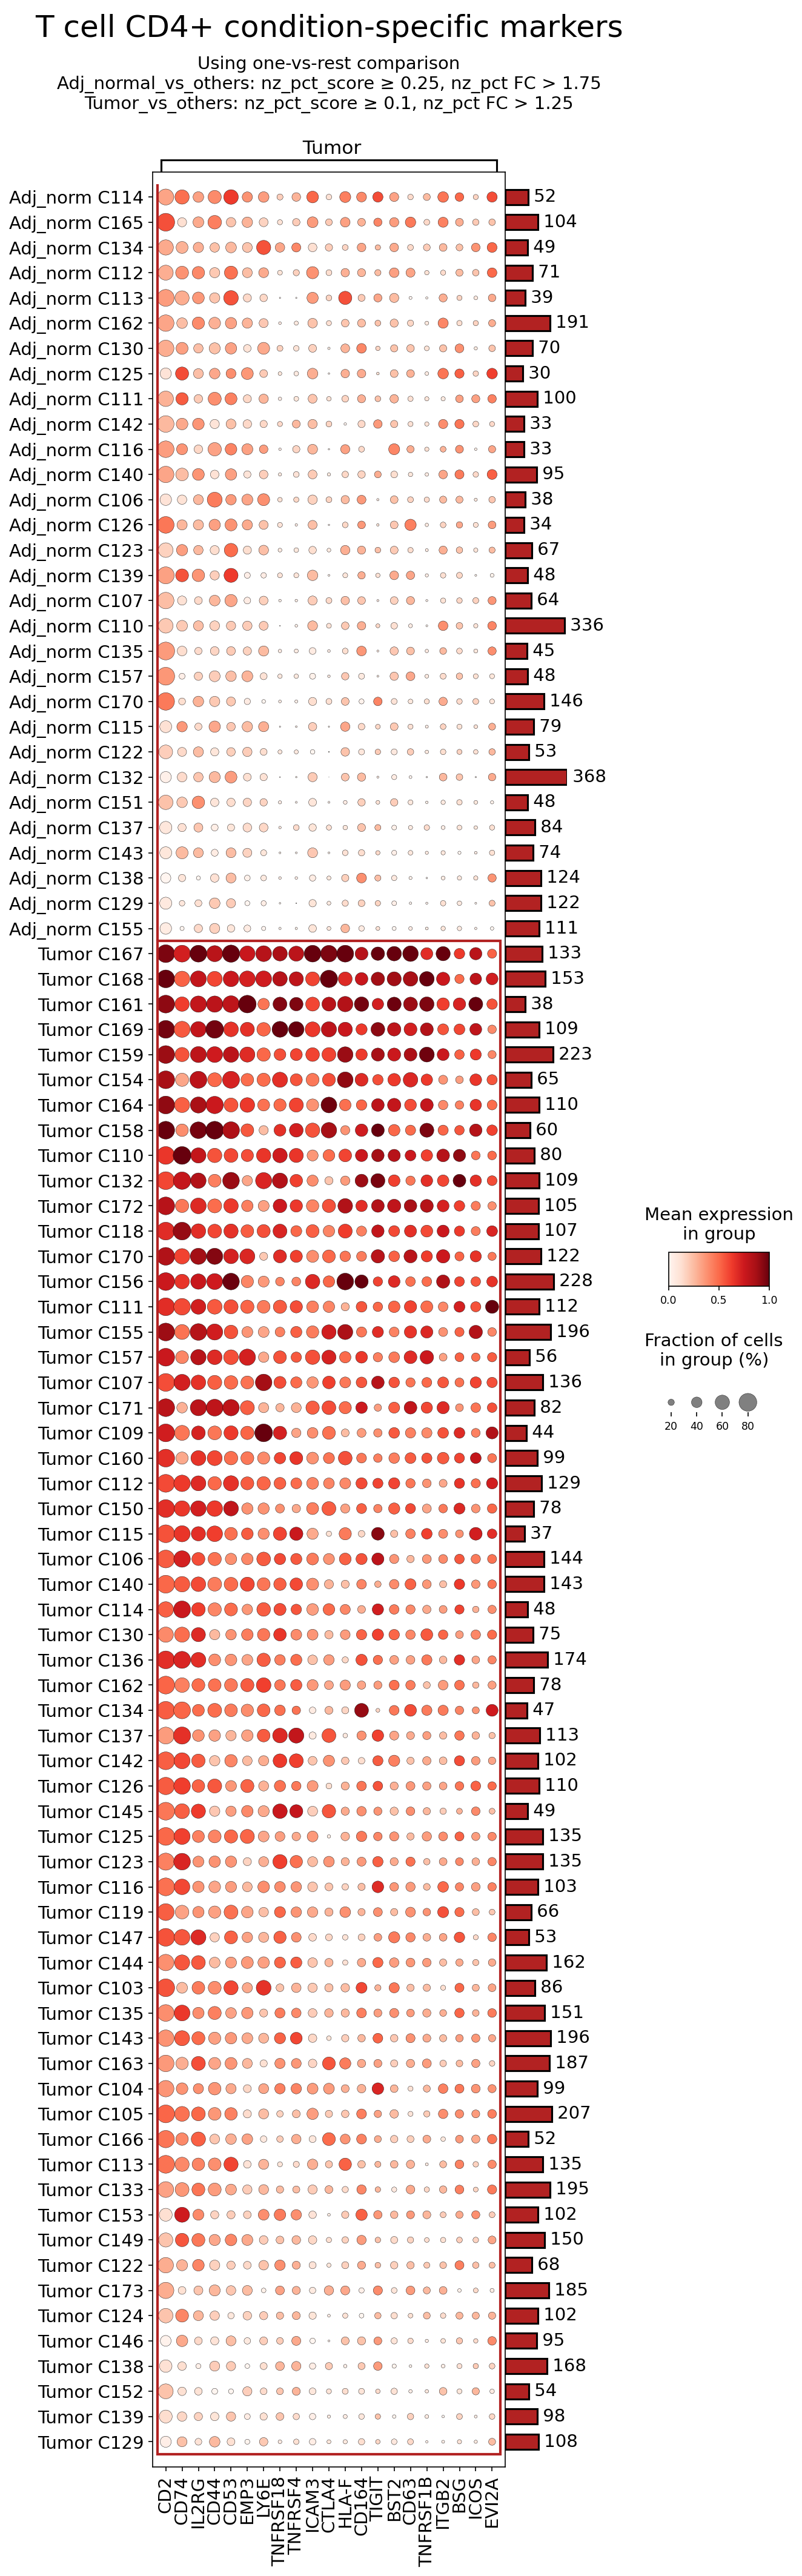
[Analysis Visualization Results]...
Analysis Overview
This analysis identifies and visualizes surfaceome markers specifically expressed by CD4+ T cells in both tumor and adjacent normal (Adj_normal) colon tissue samples from colorectal cancer patients. The dot plot displays the mean expression level (color intensity) and the fraction of cells expressing each marker (dot size) across individual samples, grouped by condition. The markers were selected based on differential expression criteria (one-vs-rest comparison) with specified thresholds for non-zero percentage score and fold change. The primary goal is to identify potential condition-specific biomarkers and therapeutic targets within the CD4+ T cell population in the colorectal tumor microenvironment.
Visual Summary
The dot plot shows the expression patterns of 25 surfaceome markers across various CD4+ T cell samples from "Adj_normal" and "Tumor" conditions.
- Clear Condition-Specific Patterns: A striking visual distinction is observed between the "Adj_normal" and "Tumor" groups. CD4+ T cells from tumor samples generally exhibit much higher mean expression (darker red color) and a higher fraction of expressing cells (larger dot size) for a substantial number of markers compared to their counterparts in adjacent normal tissue. This indicates a significant immunological alteration within the tumor microenvironment affecting CD4+ T cell phenotypes.
- Prominent Tumor-Associated Markers: Markers such as CTLA4, TIGIT, CD44, ICOS, CD74, TNFRSF4, and BSG show particularly strong and consistent upregulation in CD4+ T cells from most tumor samples. For these markers, the dots are frequently large and dark red, indicating both high expression levels and high prevalence within the CD4+ T cell population of tumor tissues.
- Heterogeneity within Conditions: While general trends are observed, there is also some sample-to-sample variability within both the "Adj_normal" and "Tumor" groups. For instance, some tumor samples show exceptionally high expression for specific markers (e.g., Tumor C161, C169, C159 for many markers), while others show more moderate levels.
- Low/Absent Expression in Adj_normal: Many of the markers highly expressed in tumor samples show very low or absent expression in most "Adj_normal" samples (small, pale dots or no dots), reinforcing their potential as tumor-associated immunomodulatory targets.
- Total Cell Counts: The bar plot on the right indicates the number of CD4+ T cells detected in each sample, ranging from a few tens to several hundreds. This variability in cell numbers per sample should be considered when interpreting overall trends, although the dot plot normalizes for expression and fraction.
Biological Interpretation
The differential expression of surfaceome markers on CD4+ T cells in colorectal cancer tissues highlights significant changes in T cell activation, regulation, and functional states within the tumor microenvironment (TME). Several key markers stand out as highly expressed in CD4+ T cells from tumor samples.
Key Tumor-Associated Markers in CD4+ T cells:
- CTLA4 (Cytotoxic T-Lymphocyte Associated Protein 4)
- Expression Pattern: Consistently highly expressed with high mean expression and fraction of cells in Tumor CD4+ T cells, very low in Adj_normal.
- Signaling Pathways: CTLA4 is an immune checkpoint molecule that acts as a potent negative regulator of T cell activation. It competes with CD28 for binding to B7 ligands (CD80/CD86) on antigen-presenting cells (APCs), delivering an inhibitory signal that dampens T cell proliferation and cytokine production.
- Role in CRC TME: Upregulation of CTLA4 on CD4+ T cells, particularly regulatory T cells (Tregs), is a hallmark of immune suppression in the TME. These CTLA4-expressing Tregs can suppress anti-tumor immune responses, promoting tumor growth and immune evasion in colorectal cancer.
- Therapeutic Target Potential: CTLA4 is a well-established immune checkpoint target. Blocking CTLA4 can enhance T cell activation and anti-tumor immunity by releasing the inhibitory brake on T cells.
- Relevant Therapeutic Agents: Ipilimumab (Yervoy) is an anti-CTLA4 monoclonal antibody approved for melanoma and is being investigated in various other cancers, including colorectal cancer, often in combination with anti-PD-1 therapy. PubMed Search: CTLA4 colorectal cancer immunotherapy
- Other Information: High CTLA4 expression on tumor-infiltrating lymphocytes often correlates with poor prognosis in some cancers, but its blockade has shown clinical benefit.
- TIGIT (T-cell Immunoreceptor with Ig and ITIM domains)
- Expression Pattern: Highly expressed in Tumor CD4+ T cells, with high mean expression and fraction of cells, and minimal expression in Adj_normal.
- Signaling Pathways: TIGIT is another immune checkpoint receptor expressed on T cells and NK cells. It binds to poliovirus receptor (PVR/CD155) and nectin-2 (CD112) on APCs and tumor cells. TIGIT signaling delivers an inhibitory signal, suppressing T cell activation, proliferation, and cytokine production, similar to PD-1 and CTLA4.
- Role in CRC TME: TIGIT expression on tumor-infiltrating CD4+ T cells, including effector T cells and Tregs, contributes to T cell exhaustion and immune evasion within the colorectal cancer TME, limiting anti-tumor responses.
- Therapeutic Target Potential: TIGIT is an emerging immune checkpoint target. Blocking TIGIT can restore anti-tumor immunity, often synergizing with PD-1 blockade.
- Relevant Therapeutic Agents: Several anti-TIGIT monoclonal antibodies (e.g., tiragolumab, vibostolimab) are in clinical trials for various solid tumors, including colorectal cancer. PubMed Search: TIGIT colorectal cancer immunotherapy
- ICOS (Inducible T-cell COStimulator)
- Expression Pattern: Notably upregulated in Tumor CD4+ T cells, with high mean expression and fraction of cells, compared to Adj_normal.
- Signaling Pathways: ICOS is a co-stimulatory receptor belonging to the CD28 family, expressed primarily on activated T cells. It binds to ICOSL (ICOS ligand) on APCs. Unlike CD28, ICOS signaling is critical for sustained T cell activation, differentiation, and survival, particularly for follicular helper T cells (Tfh) and regulatory T cells (Treg), and for the production of certain cytokines (e.g., IL-10).
- Role in CRC TME: ICOS expression can indicate activated T cells. While ICOS can promote effector T cell functions, its high expression on Tregs can also contribute to immune suppression, making its role complex in the TME. In CRC, ICOS+ Tregs are often enriched and contribute to an immunosuppressive environment.
- Therapeutic Target Potential: ICOS is a complex target. Agonistic antibodies targeting ICOS aim to enhance anti-tumor effector T cell responses, while antagonistic antibodies might be considered to deplete or inhibit ICOS-expressing Tregs.
- Relevant Therapeutic Agents: Both ICOS agonists and antagonists are in various stages of clinical development for cancer immunotherapy. GeneCards: ICOS
- CD44 (Cluster of Differentiation 44)
- Expression Pattern: Highly and broadly expressed across Tumor CD4+ T cells, with strong signals in most samples, and generally lower in Adj_normal.
- Signaling Pathways: CD44 is a transmembrane glycoprotein that functions as a cell adhesion molecule and a receptor for hyaluronic acid (HA), osteopontin, and other ligands. It plays roles in cell migration, proliferation, and survival. Its splice variants (CD44v) are often associated with stemness and aggressive tumor phenotypes.
- Role in CRC TME: High CD44 expression on CD4+ T cells, especially specific isoforms, can be involved in T cell trafficking, interaction with the extracellular matrix, and potentially influencing T cell activation and differentiation within the TME. It can also be expressed by tumor cells and cancer stem cells, contributing to their survival and metastasis.
- Therapeutic Target Potential: CD44, particularly specific isoforms like CD44v6, has been explored as a therapeutic target in cancer due to its role in tumor progression and metastasis. Blocking CD44 might disrupt tumor-stroma interactions and T cell trafficking.
- Relevant Therapeutic Agents: Anti-CD44 antibodies are under investigation, particularly those targeting specific CD44 variants, to inhibit tumor growth and metastasis. UniProt: P16070 (CD44_HUMAN)
- CD74 (HLA class II histocompatibility antigen gamma chain)
- Expression Pattern: Upregulated in Tumor CD4+ T cells compared to Adj_normal.
- Signaling Pathways: CD74 acts as an invariant chain in the endoplasmic reticulum, facilitating the assembly and transport of MHC class II molecules to the cell surface. Beyond this, cell surface CD74 can act as a receptor for macrophage migration inhibitory factor (MIF), initiating signaling cascades (e.g., MAPK, NF-κB) that promote cell proliferation, survival, and inflammation.
- Role in CRC TME: Upregulation of CD74 on CD4+ T cells, or other immune cells, can contribute to the inflammatory and pro-tumorigenic environment by mediating MIF signaling. MIF-CD74 axis is implicated in immune evasion and angiogenesis in various cancers.
- Therapeutic Target Potential: Targeting CD74 or its interaction with MIF could disrupt pro-tumorigenic signaling pathways and suppress inflammation in the TME.
- Relevant Therapeutic Agents: Anti-CD74 antibodies are being explored, especially in hematological malignancies. For solid tumors, targeting the MIF-CD74 axis is an area of active research. PubMed Search: CD74 MIF colorectal cancer
- TNFRSF4 (OX40, Tumor Necrosis Factor Receptor Superfamily Member 4)
- Expression Pattern: Shows higher expression and prevalence in Tumor CD4+ T cells compared to Adj_normal.
- Signaling Pathways: OX40 is a co-stimulatory receptor primarily expressed on activated CD4+ and CD8+ T cells. Its ligand, OX40L, is found on APCs. Engagement of OX40 by OX40L provides a potent secondary co-stimulatory signal, promoting T cell proliferation, survival, cytokine production (e.g., IL-2, IFN-γ), and memory T cell development.
- Role in CRC TME: OX40 signaling can enhance anti-tumor immune responses by sustaining effector T cell function. However, it can also promote the proliferation and survival of Tregs, which could be immunosuppressive. The balance depends on the specific context and T cell subsets. In CRC, its expression suggests activated T cells, and harnessing this pathway could boost anti-tumor immunity.
- Therapeutic Target Potential: Agonistic antibodies targeting OX40 are under investigation to enhance T cell-mediated anti-tumor immunity.
- Relevant Therapeutic Agents: OX40 agonists (e.g., MEDI6469, BMS-986178) are in clinical trials for solid tumors, aiming to enhance anti-tumor T cell responses. PubMed Search: OX40 colorectal cancer therapy
- BSG (Basigin, CD147)
- Expression Pattern: Upregulated in Tumor CD4+ T cells compared to Adj_normal.
- Signaling Pathways: BSG (CD147) is a transmembrane glycoprotein involved in various cellular processes including cell adhesion, migration, proliferation, and differentiation. It is a critical regulator of matrix metalloproteinases (MMPs), thereby promoting ECM degradation and tumor invasion. It also plays a role in lactate transport, supporting aerobic glycolysis (Warburg effect).
- Role in CRC TME: Elevated BSG expression on immune cells, including T cells, and tumor cells is associated with tumor progression, metastasis, and immune modulation. In the TME, it can impact T cell function and interaction with tumor cells, contributing to an immunosuppressive or pro-invasive environment.
- Therapeutic Target Potential: BSG is considered a therapeutic target due to its role in tumor progression, angiogenesis, and metastasis. Inhibiting BSG could impair tumor invasion and suppress tumor growth.
- Relevant Therapeutic Agents: Anti-CD147 antibodies and small molecule inhibitors are being investigated for their anti-cancer properties. GeneCards: BSG
The observed differential expression profiles suggest that CD4+ T cells in the colorectal tumor microenvironment undergo significant phenotypic changes, often acquiring characteristics associated with activation, exhaustion, or regulatory functions (e.g., high CTLA4, TIGIT, ICOS). This implies an ongoing immune response that is simultaneously being regulated or suppressed.
Clinical or Translational Implications
The identification of these highly expressed surfaceome markers on CD4+ T cells within colorectal tumor samples has several important clinical and translational implications:
- Biomarker Potential: Markers such as CTLA4, TIGIT, ICOS, CD44, CD74, TNFRSF4, and BSG could serve as biomarkers to characterize the immune status of the colorectal TME. Their expression levels on tumor-infiltrating CD4+ T cells might correlate with patient prognosis, response to therapy, or disease progression. For instance, high expression of immune checkpoints like CTLA4 and TIGIT could indicate a more immunosuppressive environment.
- Therapeutic Targets: The significant upregulation of immune checkpoint molecules (CTLA4, TIGIT) strongly supports their potential as therapeutic targets for immune checkpoint blockade in colorectal cancer. Combination therapies targeting multiple checkpoints (e.g., anti-CTLA4 with anti-PD-1 or anti-TIGIT) could potentially overcome resistance and enhance anti-tumor immunity.
- Stratification for Immunotherapy: The specific expression profiles of these markers might allow for patient stratification, helping to identify subsets of patients who are more likely to respond to particular immunotherapies. For example, patients with high TIGIT expression on their CD4+ T cells might benefit from anti-TIGIT therapy.
- Novel Immunomodulatory Strategies: Beyond checkpoint blockade, markers like ICOS and TNFRSF4 (OX40) represent co-stimulatory pathways that could be targeted with agonistic antibodies to boost anti-tumor effector T cell responses. CD44, CD74, and BSG, while not classical immune checkpoints, are involved in T cell trafficking, cell survival, inflammation, and tumor invasion, making them intriguing targets for novel immunomodulatory strategies that address broader aspects of the TME.
- Drug Development: These findings provide a rationale for further research and development of targeted therapies that specifically modulate the function of CD4+ T cells in colorectal cancer, aiming to shift the balance from an immunosuppressive to an anti-tumorigenic environment. Experimental validation in preclinical models and clinical trials would be crucial to confirm the therapeutic utility of targeting these markers.
19. Dysregulation of Cell Cycle Pathway Genes in Intestinal Epithelial Cells of Colorectal Cancer
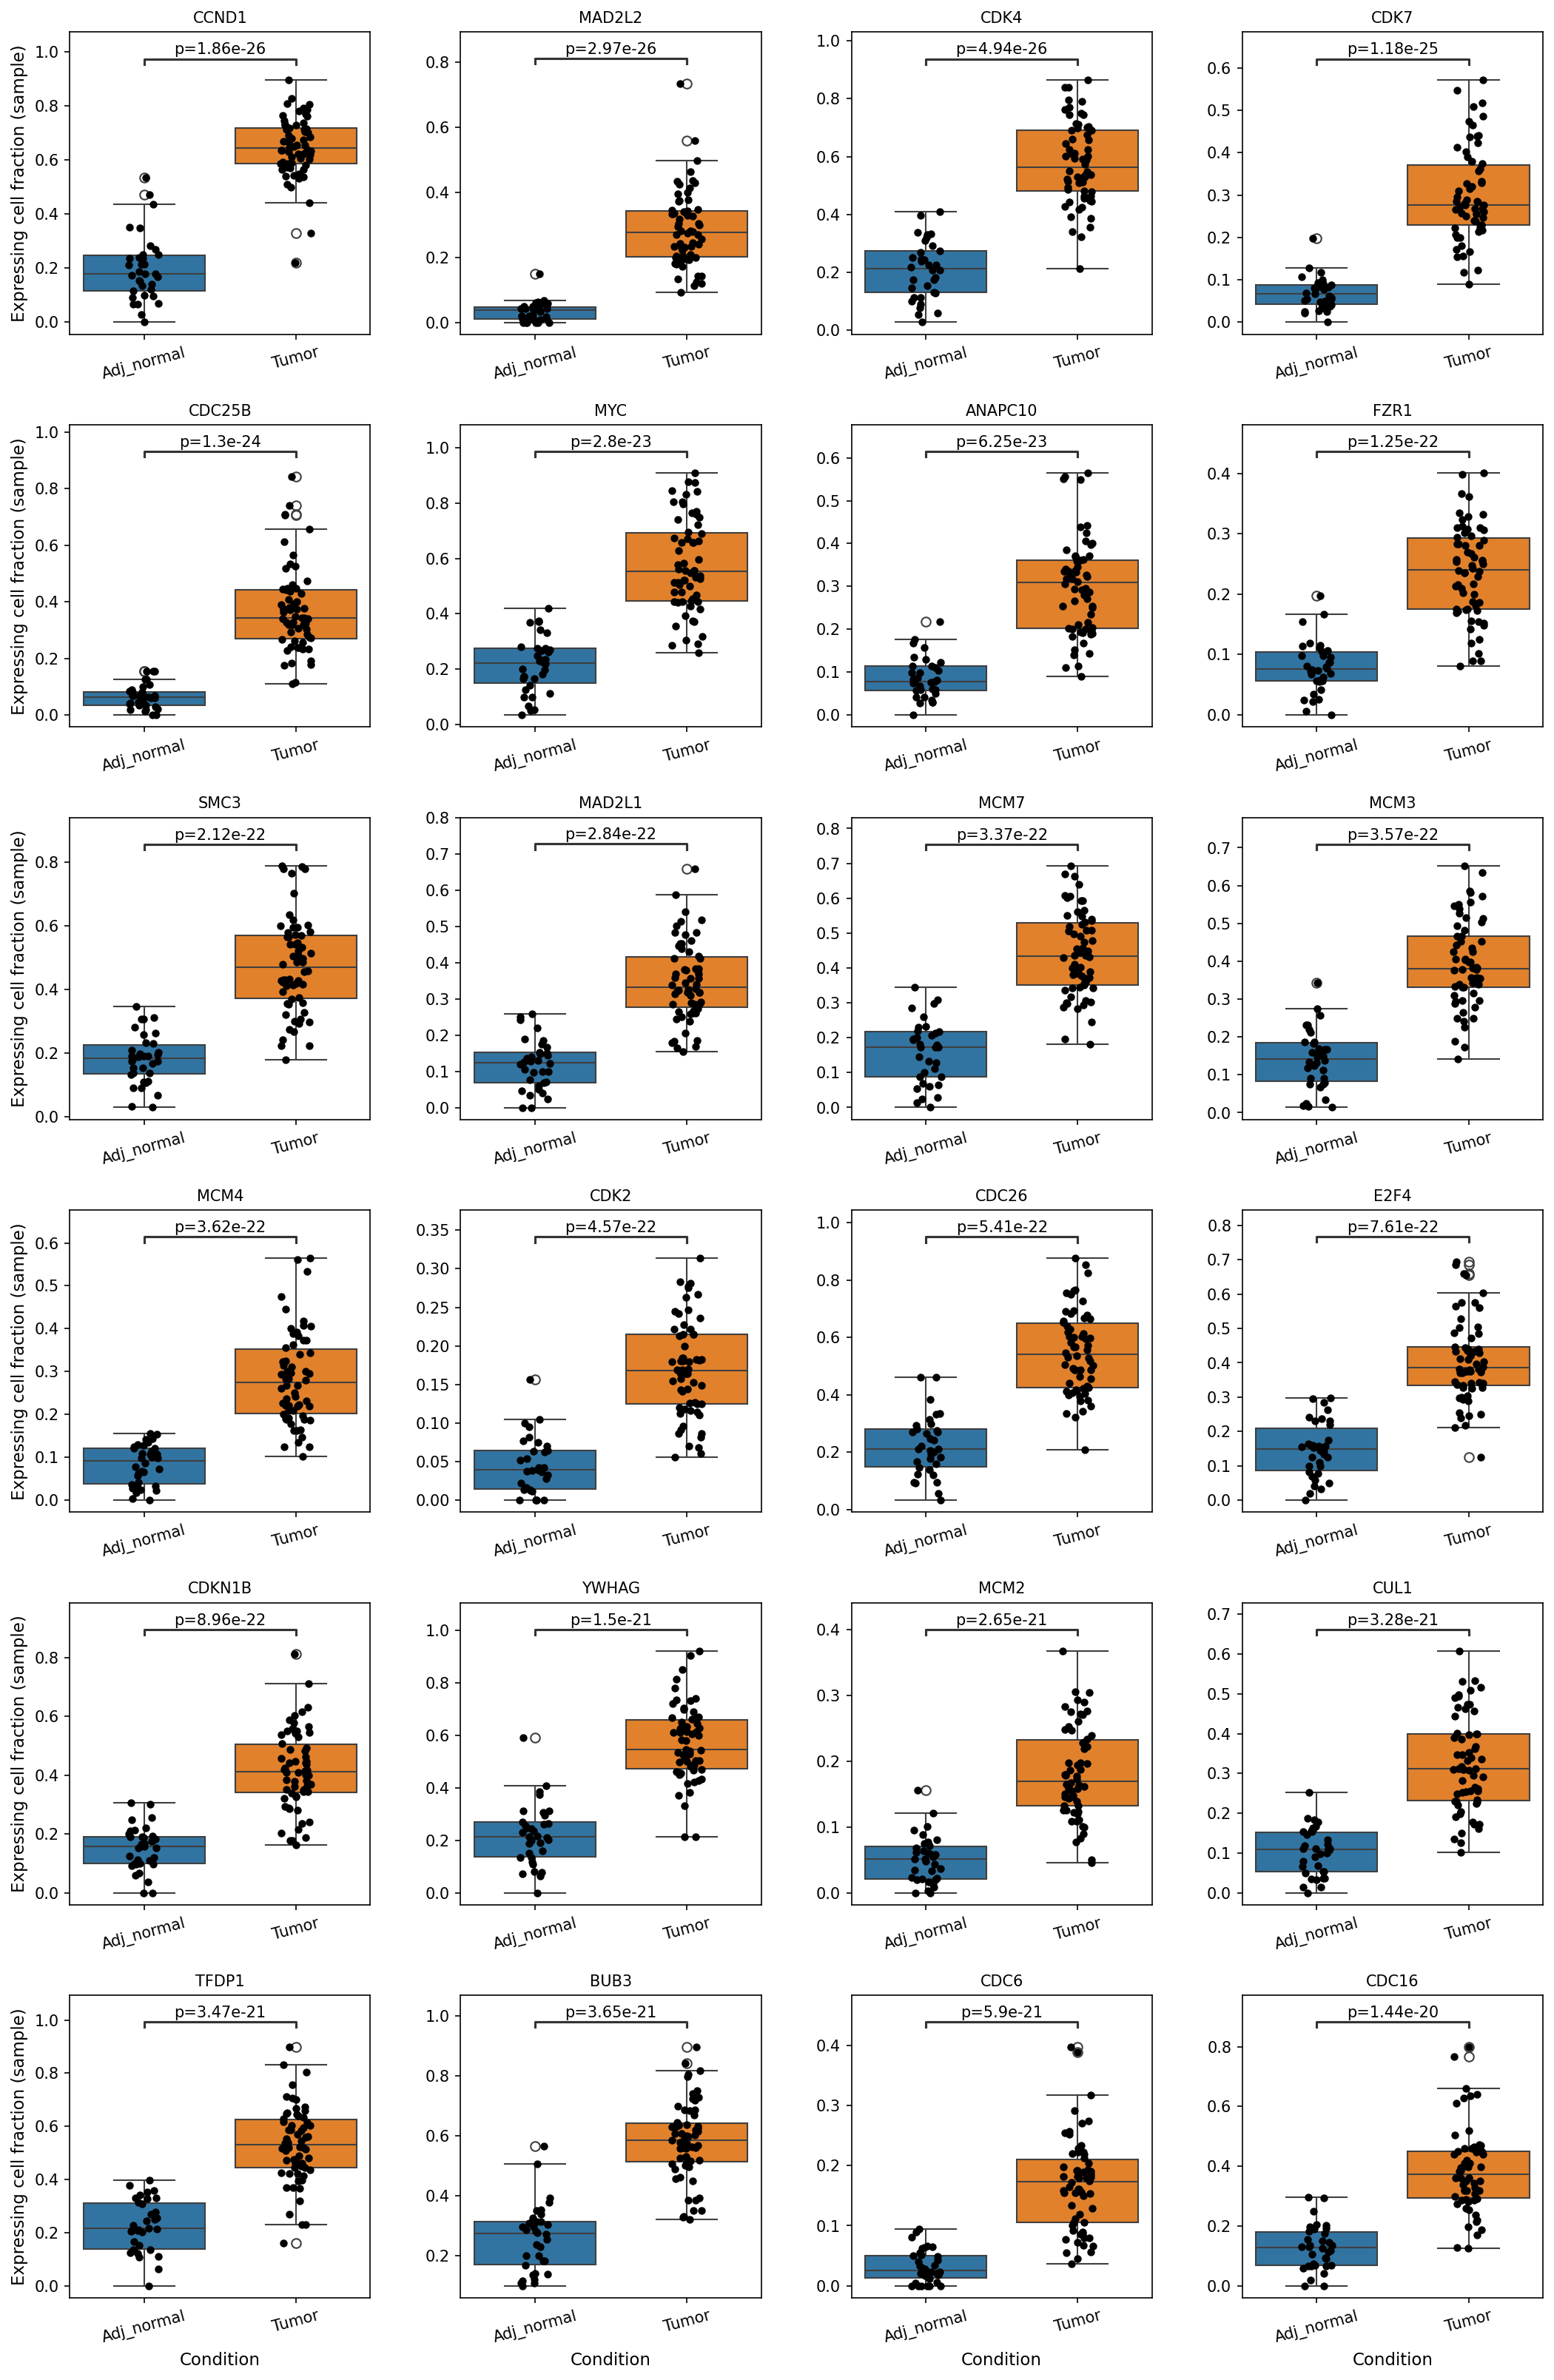
[Analysis Visualization Results]...
Analysis Overview
This analysis investigates the "expressing cell fraction" of a curated set of cell cycle pathway genes in Intestinal Epithelial cells, comparing cells from "Tumor" samples against "Adj_normal" samples. The purpose is to identify cell cycle genes that exhibit statistically significant differences in the proportion of cells expressing them between these two conditions, providing insights into the proliferative state and regulatory mechanisms within the tumor microenvironment. The analysis specifically focuses on the Intestinal Epithelial cell population, which is identified as the resolved tumor-origin cell type in this colorectal cancer dataset.
Visual Summary
The visualization presents 24 box plots, each representing a distinct cell cycle-related gene. For every gene, the "Expressing cell fraction (sample)" is plotted across "Adj_normal" and "Tumor" conditions. A stripplot overlay shows individual sample data points.
Key observations from the plots include:
- Consistent Upregulation in Tumor: For all 24 displayed genes, the median "Expressing cell fraction (sample)" is markedly higher in the "Tumor" condition compared to the "Adj_normal" condition. This indicates that a significantly larger proportion of Intestinal Epithelial cells in tumor samples are actively expressing these cell cycle genes.
- High Statistical Significance: All observed differences are highly statistically significant, as indicated by the extremely low p-values (e.g., 1.86e-26 for CCND1, 2.97e-26 for MAD2L2, 4.94e-26 for CDK4), far below the typical 0.05 significance threshold.
- Increased Variability in Tumor: While the fraction of expressing cells is generally higher in tumors, there appears to be a wider spread (larger interquartile range and greater scatter of individual data points) in the "Tumor" group for many genes compared to the "Adj_normal" group, suggesting heterogeneity in cell cycle activity among different tumor samples.
- Prominent Genes: Genes such as CCND1, CDK4, MYC, MCM2, MCM3, MCM4, MCM7, CDC25B, and E2F4 show particularly strong and consistent increases in the fraction of expressing cells in tumor samples. These genes are well-known for their roles in promoting cell cycle progression and proliferation.
Biological Interpretation
The observed widespread and statistically significant increase in the fraction of Intestinal Epithelial cells expressing key cell cycle genes in tumor samples provides strong biological evidence of enhanced cellular proliferation and uncontrolled cell division, which are hallmarks of cancer. This finding is highly consistent with the inferred disease context of Colorectal cancer, where Intestinal Epithelial cells are the primary neoplastic component.
- Cell Cycle Progression: The upregulation of cyclins (CCND1), cyclin-dependent kinases (CDK4, CDK7, CDK2), and their activators (CDC25B) directly signifies an accelerated progression through the cell cycle. For instance, CCND1 and CDK4 are critical for the G1 to S phase transition, suggesting that tumor cells are rapidly exiting quiescence and entering the proliferative cycle. GeneCards: CCND1, GeneCards: CDK4
- DNA Replication Machinery: Genes like MCM2, MCM3, MCM4, and MCM7, which are core components of the minichromosome maintenance complex, are essential for initiating and elongating DNA replication. Their increased expression fraction points to a higher number of cells actively undergoing DNA synthesis (S-phase), a prerequisite for cell division. GeneCards: MCM2
- Mitotic Regulators: Genes involved in mitosis and cell division, such as MAD2L1, MAD2L2, BUB3 (components of the spindle assembly checkpoint), and ANAPC10, FZR1, CDC16, CDC26 (components or regulators of the Anaphase-Promoting Complex/Cyclosome, APC/C), also show increased expression fractions. This suggests a higher proportion of cells are actively navigating and completing mitosis. GeneCards: MAD2L1
- Oncogenic Drivers: The consistent upregulation of MYC and E2F4 (a transcription factor often linked to cell cycle regulation and proliferation, especially in oncogenesis) further reinforces the notion of an activated oncogenic program driving cell cycle machinery. MYC is a well-known proto-oncogene that plays a central role in promoting cell growth and division. GeneCards: MYC
- Concordance with Aneuploidy: The observation of significantly higher fractions of cells expressing these cell cycle genes in tumors aligns with the reported 13.4% aneuploid cells in the dataset. Dysregulated cell cycle progression, particularly during mitosis, often leads to chromosomal instability and aneuploidy, a common feature of cancer cells.
Together, these findings strongly suggest that Intestinal Epithelial cells in colorectal tumors exhibit a robust and sustained activation of the cell cycle machinery, driving uncontrolled proliferation, which is a fundamental characteristic of tumor development and progression.
Clinical or Translational Implications
The pervasive upregulation of cell cycle pathway genes in tumor-derived Intestinal Epithelial cells carries significant clinical and translational implications for colorectal cancer:
- Biomarkers for Proliferation: The genes identified in this analysis (e.g., CCND1, CDK4, MCMs, MYC) could serve as valuable biomarkers for assessing tumor cell proliferation. High expression levels or a high fraction of expressing cells could indicate more aggressive disease, potentially aiding in prognosis and risk stratification of colorectal cancer patients.
- Therapeutic Targets: Many of these genes and their associated pathways are established or emerging targets for anti-cancer therapies. CDK4/6 inhibitors are already approved for other cancers (e.g., breast cancer), and targeting these pathways in colorectal cancer could be a viable therapeutic strategy. Inhibitors of MYC, MCMs, or components of the mitotic machinery could also be explored. PubMed search: CDK4/6 inhibitors colorectal cancer
- Drug Resistance Mechanisms: Understanding the specific cell cycle genes that are highly active in colorectal cancer cells might also shed light on potential mechanisms of resistance to existing therapies or inform the development of combination therapies.
- Monitoring Treatment Response: Changes in the expression fraction of these genes could potentially be used to monitor the efficacy of anti-proliferative therapies, with a decrease indicating a positive treatment response.
- Targeted Therapies for Epithelial Tumors: Given that these proliferative changes are specifically observed in the tumor-originating Intestinal Epithelial cells, therapies targeting these pathways could be particularly effective against the cancerous epithelial component of colorectal tumors.
20. Gene Ontology (GSA) Enrichment in Intestinal Epithelial Cells Across Different Conditions in Colorectal Cancer
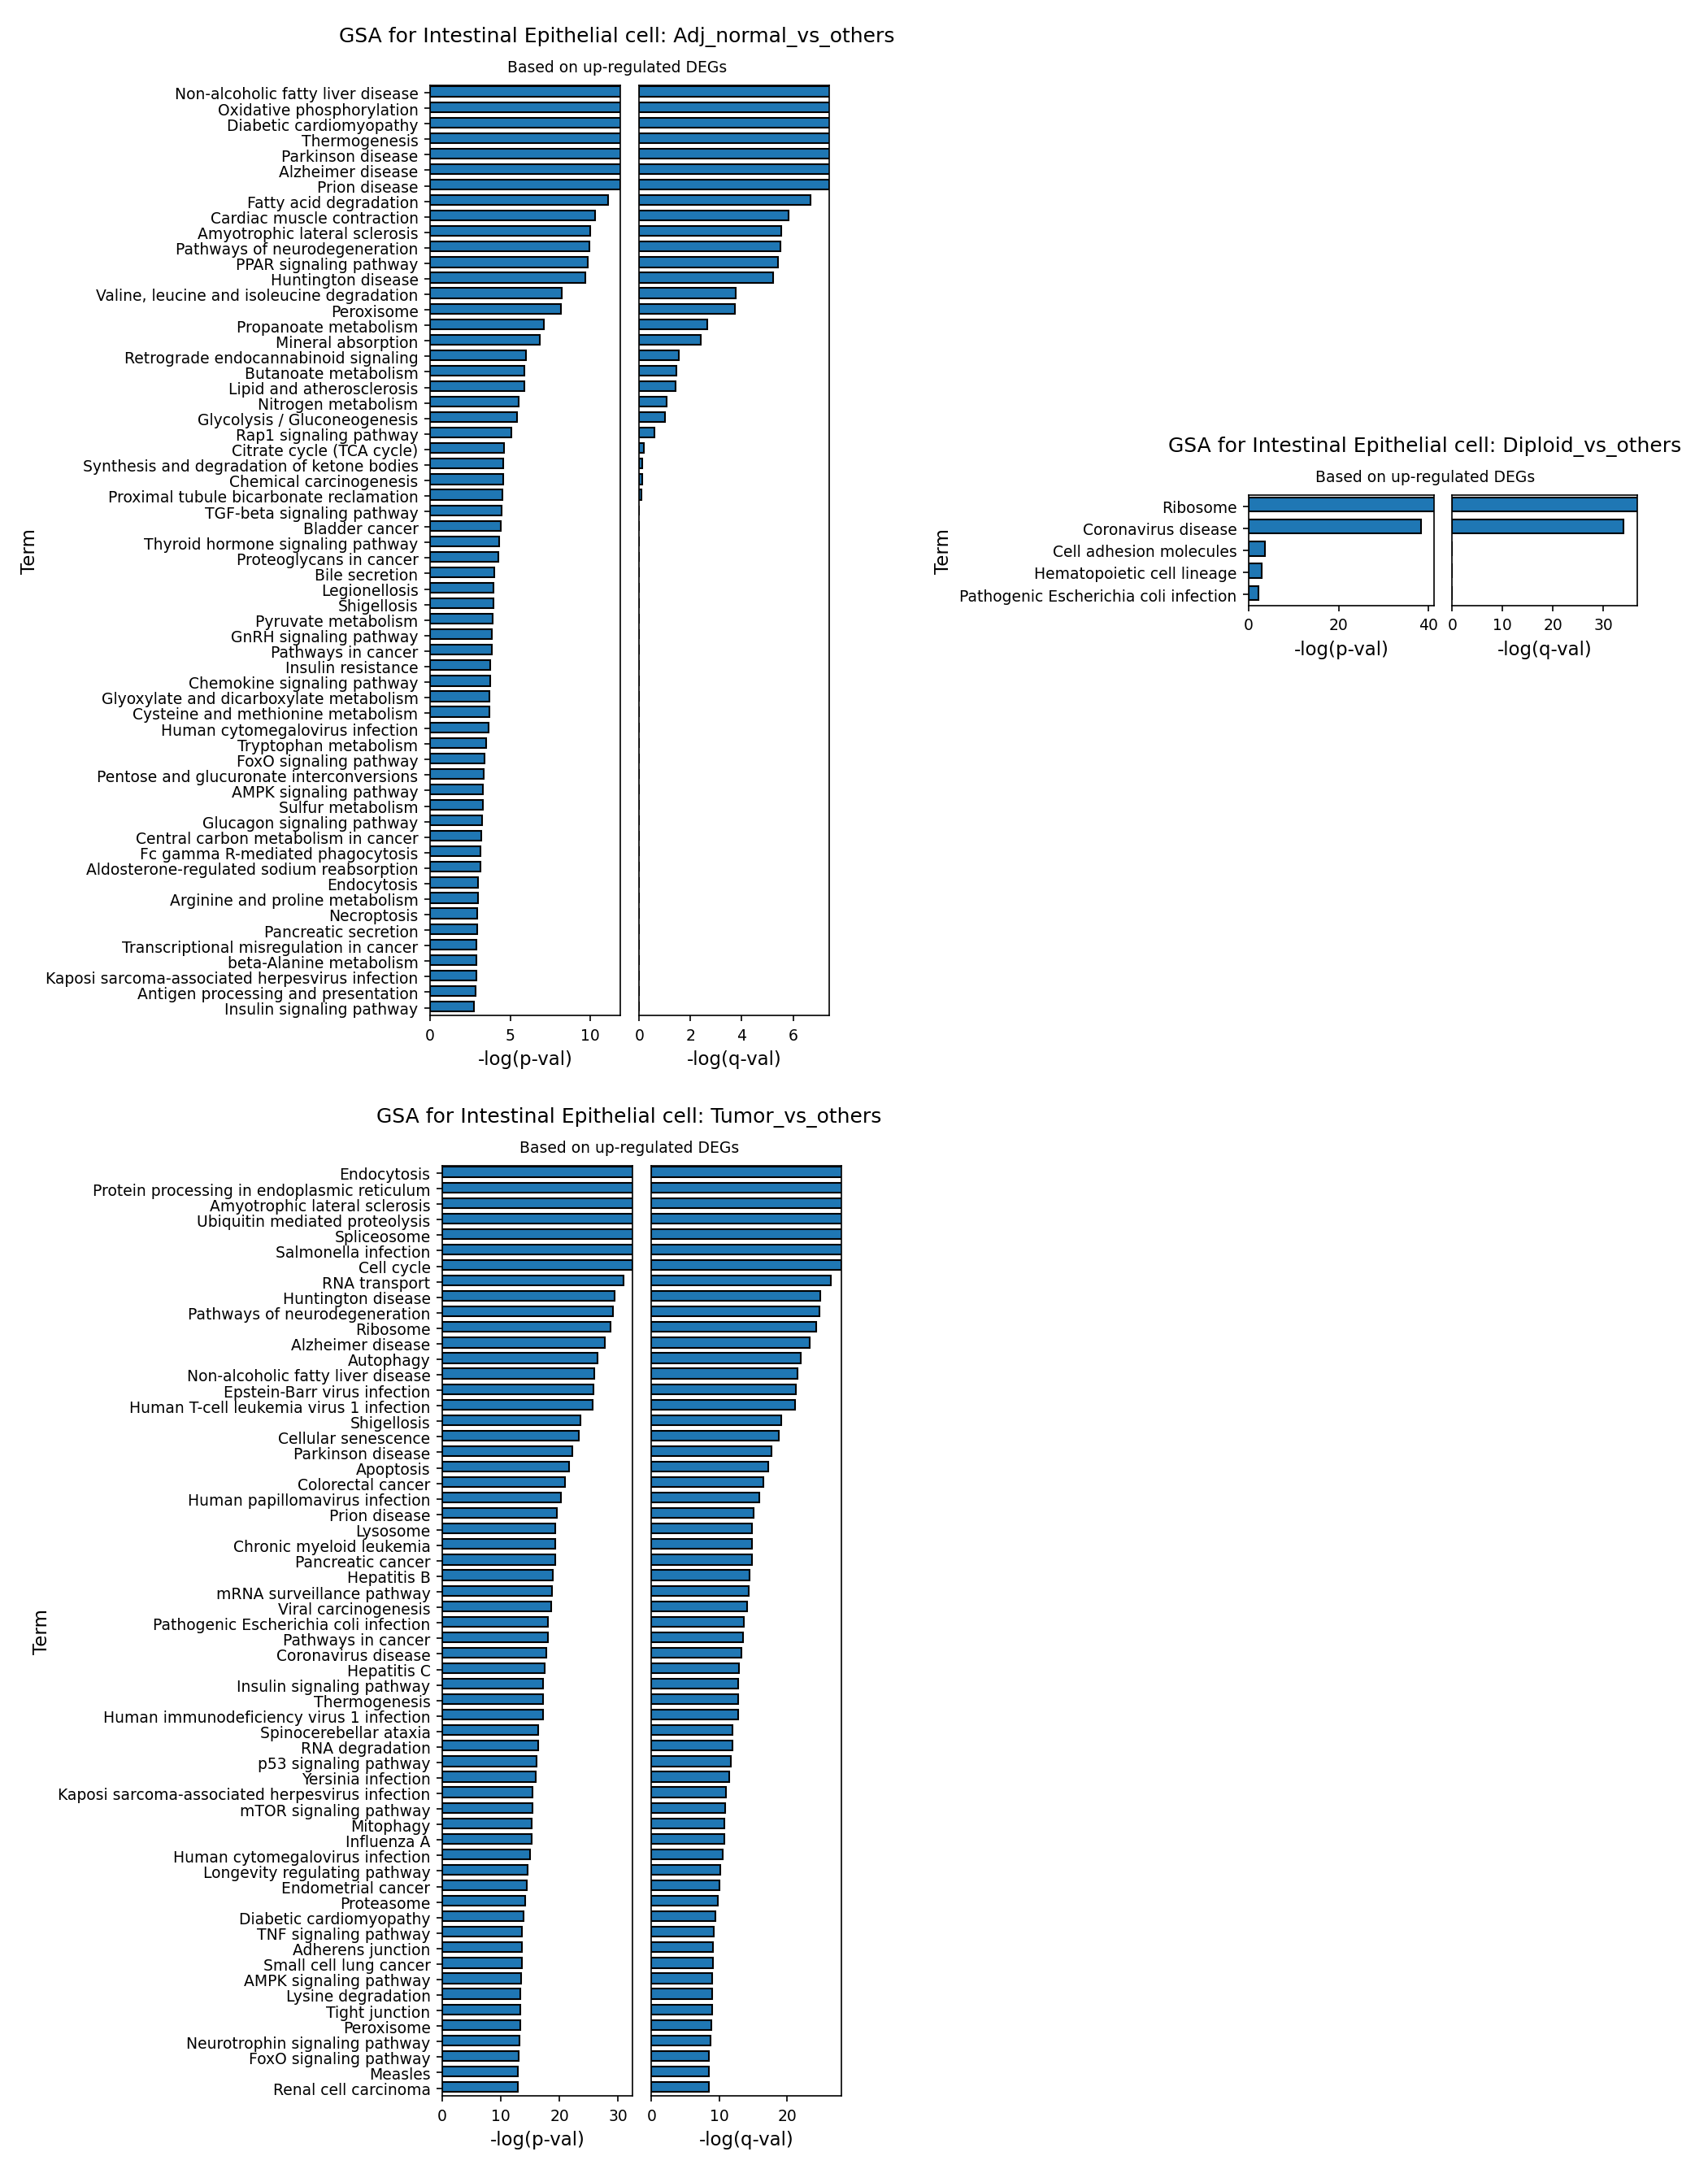
[Analysis Visualization Results]...
Analysis Overview
This analysis utilizes Gene Ontology (GSA) to identify biological pathways and processes significantly enriched in Intestinal Epithelial cells. The enrichment was determined based on up-regulated differentially expressed genes (DEGs) for three comparative conditions: 'Adj_normal' versus all other cells, 'Diploid' versus all other cells, and 'Tumor' versus all other cells. The primary objective is to delineate the distinct functional states and biological activities of Intestinal Epithelial cells in the context of colorectal cancer, comparing their characteristics in adjacent normal tissue, diploid cells, and tumor cells.
Visual Summary
GSA for Intestinal Epithelial cell: Adj_normal_vs_others
The bar plot for adjacent normal Intestinal Epithelial cells reveals a strong enrichment of pathways primarily associated with metabolism and energy production. Highly significant terms include 'Oxidative phosphorylation', 'Fatty acid degradation', 'Valine, leucine and isoleucine degradation', 'Peroxisome', 'Propanoate metabolism', 'PPAR signaling pathway', 'Lipid and atherosclerosis', 'Butanoate metabolism', 'Mineral absorption', and 'Thermogenesis'. Intriguingly, several pathways linked to neurodegenerative diseases such as 'Non-alcoholic fatty liver disease', 'Diabetic cardiomyopathy', 'Parkinson Disease', 'Alzheimer Disease', 'Prion disease', 'Cardiac muscle contraction', 'Amyotrophic lateral sclerosis', 'Pathways of neurodegeneration', and 'Huntington disease' also show high enrichment, suggesting shared fundamental cellular processes or stress responses.
GSA for Intestinal Epithelial cell: Diploid_vs_others
Diploid Intestinal Epithelial cells exhibit significant enrichment in pathways related to fundamental cellular machinery and host defense. The most prominent term is 'Ribosome', indicating active protein synthesis. 'Coronavirus disease' and 'Cell adhesion molecules' are also highly enriched. Other terms include 'Hematopoietic cell lineage' and 'Pathogenic Escherichia coli infection', suggesting roles in maintaining cellular structure and responding to pathogens.
GSA for Intestinal Epithelial cell: Tumor_vs_others
The plot for tumor-derived Intestinal Epithelial cells shows a broad and highly significant enrichment of pathways characteristic of malignancy, altered metabolism, stress responses, and infection. Key terms include:
- Cellular Proliferation & Survival: 'Endocytosis', 'Protein processing in endoplasmic reticulum', 'Ubiquitin mediated proteolysis', 'Spliceosome', 'Cell cycle', 'Autophagy', 'Apoptosis', 'p53 signaling pathway', 'mTOR signaling pathway', and 'Cellular senescence'.
- Infection & Inflammation: A striking number of terms related to various viral and bacterial infections such as 'Salmonella infection', 'Epstein-Barr virus infection', 'Human T-cell leukemia virus 1 infection', 'Shigellosis', 'Human papillomavirus infection', 'Hepatitis B', 'Coronavirus disease', 'Pathogenic Escherichia coli infection', 'Viral carcinogenesis', 'Human immunodeficiency virus 1 infection', 'Measles infection', and 'Influenza A' are highly enriched.
- Cancer-Specific Pathways: Direct terms like 'Colorectal cancer' and 'Pathways in cancer' are also among the top enriched categories.
- Neurodegenerative Pathways: Consistent with the 'Adj_normal' observation, several neurodegenerative disease-related pathways such as 'Amyotrophic lateral sclerosis', 'Huntington disease', 'Pathways of neurodegeneration', 'Alzheimer disease', 'Parkinson disease', 'Prion disease', and 'Spinocerebellar ataxia' are also highly represented.
Biological Interpretation
The Gene Ontology analysis provides a clear functional landscape of Intestinal Epithelial cells under different conditions within the colorectal cancer microenvironment.
Metabolic Reprogramming in Cancer Progression:
- Adjacent Normal Cells: The adjacent normal Intestinal Epithelial cells are highly active metabolically, as evidenced by the strong enrichment of pathways for oxidative phosphorylation, fatty acid, and amino acid metabolism. This reflects their essential role in nutrient absorption and energy generation. The enrichment of 'Non-alcoholic fatty liver disease' may point to systemic metabolic perturbations in cancer patients or early metabolic stress in the tissue adjacent to the tumor.
- Tumor Cells: In contrast, tumor epithelial cells exhibit significant enrichment for pathways like 'Endocytosis' and 'Autophagy'. Endocytosis facilitates increased nutrient uptake, supporting rapid proliferation, while autophagy and associated pathways (e.g., 'Mitophagy') are crucial for cellular recycling and energy provision under stress, contributing to tumor cell survival and growth. This reflects the metabolic plasticity and reprogramming typical of cancer cells PubMed Search: "cancer metabolic reprogramming".
- Hallmarks of Cancer in Tumor Epithelium: The pronounced enrichment of 'Cell cycle' and 'mTOR signaling pathway' in tumor Intestinal Epithelial cells directly indicates uncontrolled proliferation and heightened anabolic processes characteristic of malignancy. The activation of 'Apoptosis' and 'p53 signaling pathway' suggests dysregulation of cell death and genomic stability mechanisms, which are critical for cancer cells to evade programmed cell death and propagate GeneCards: TP53. Furthermore, heightened 'Protein processing in endoplasmic reticulum' and 'Ubiquitin mediated proteolysis' point to increased protein synthesis and turnover demands in rapidly proliferating tumor cells, alongside mechanisms for managing protein quality control under cellular stress.
Immune and Pathogen Interactions:
- Diploid Cells: Diploid Intestinal Epithelial cells show activation of pathways like 'Cell adhesion molecules' for maintaining tissue integrity, and some infection-related terms ('Coronavirus disease', 'Pathogenic Escherichia coli infection') indicating their active role in baseline immune surveillance and barrier function against gut pathogens.
- Tumor Cells: The extensive enrichment of numerous viral and bacterial infection pathways in tumor cells is a significant observation. This suggests that the tumor microenvironment may be characterized by an altered microbiome, chronic infection, or a specific pathogenic etiology (e.g., 'Viral carcinogenesis'). Such chronic inflammation and infection can drive oncogenesis and shape the immune landscape of the tumor PubMed Search: "colorectal cancer microbiome infection".
- Shared Cellular Stress Responses: The consistent appearance of pathways related to various neurodegenerative diseases (e.g., Parkinson, Alzheimer, ALS) across 'Adj_normal' and 'Tumor' epithelial cells is intriguing. These pathways often involve fundamental cellular processes such as mitochondrial dysfunction, oxidative stress, protein aggregation, and altered proteostasis, which are not exclusive to neurological tissues but are broadly implicated in cellular aging, stress, and pathologies including cancer.
Clinical or Translational Implications
- Therapeutic Targeting of Cancer Hallmarks: The strong enrichment of pathways like 'mTOR signaling pathway' and 'Cell cycle' in tumor Intestinal Epithelial cells highlights these as established and potential therapeutic targets. Inhibitors of mTOR (e.g., everolimus, sirolimus) or cell cycle checkpoints are already used in oncology, suggesting their potential relevance in treating colorectal cancer, possibly with specific efficacy in patient subgroups driven by these pathways GeneCards: MTOR.
- Targeting Metabolic Vulnerabilities: The specific metabolic adaptations in tumor cells, such as enhanced endocytosis and altered autophagy, present opportunities for novel therapeutic strategies aiming to disrupt nutrient supply or cellular recycling essential for tumor growth and survival.
- Modulating the Tumor Microenvironment and Infection: The pervasive presence of infection-related pathways in tumor cells suggests a critical role of pathogens and inflammation in colorectal cancer. Therapeutic interventions could include targeting specific microbial components within the tumor microenvironment, addressing chronic inflammatory responses, or potentially using antimicrobial strategies alongside traditional cancer treatments, depending on the specific pathogens identified.
- Biomarker Identification: The distinct pathway signatures across 'Adj_normal', 'Diploid', and 'Tumor' epithelial cells provide a rich source for identifying novel diagnostic, prognostic, or predictive biomarkers. For instance, specific up-regulated genes within the highly enriched infection or metabolic pathways in tumor cells could serve as indicators of disease presence or progression.
- Understanding Early Pathogenesis: The metabolic and stress-related pathways in 'Adj_normal' tissue might offer insights into early events in colorectal cancer development, potentially guiding preventive strategies or interventions aimed at reversing precancerous changes.
21. Gene Set Enrichment Analysis (GSEA) Across Colorectal Cancer Cell Types
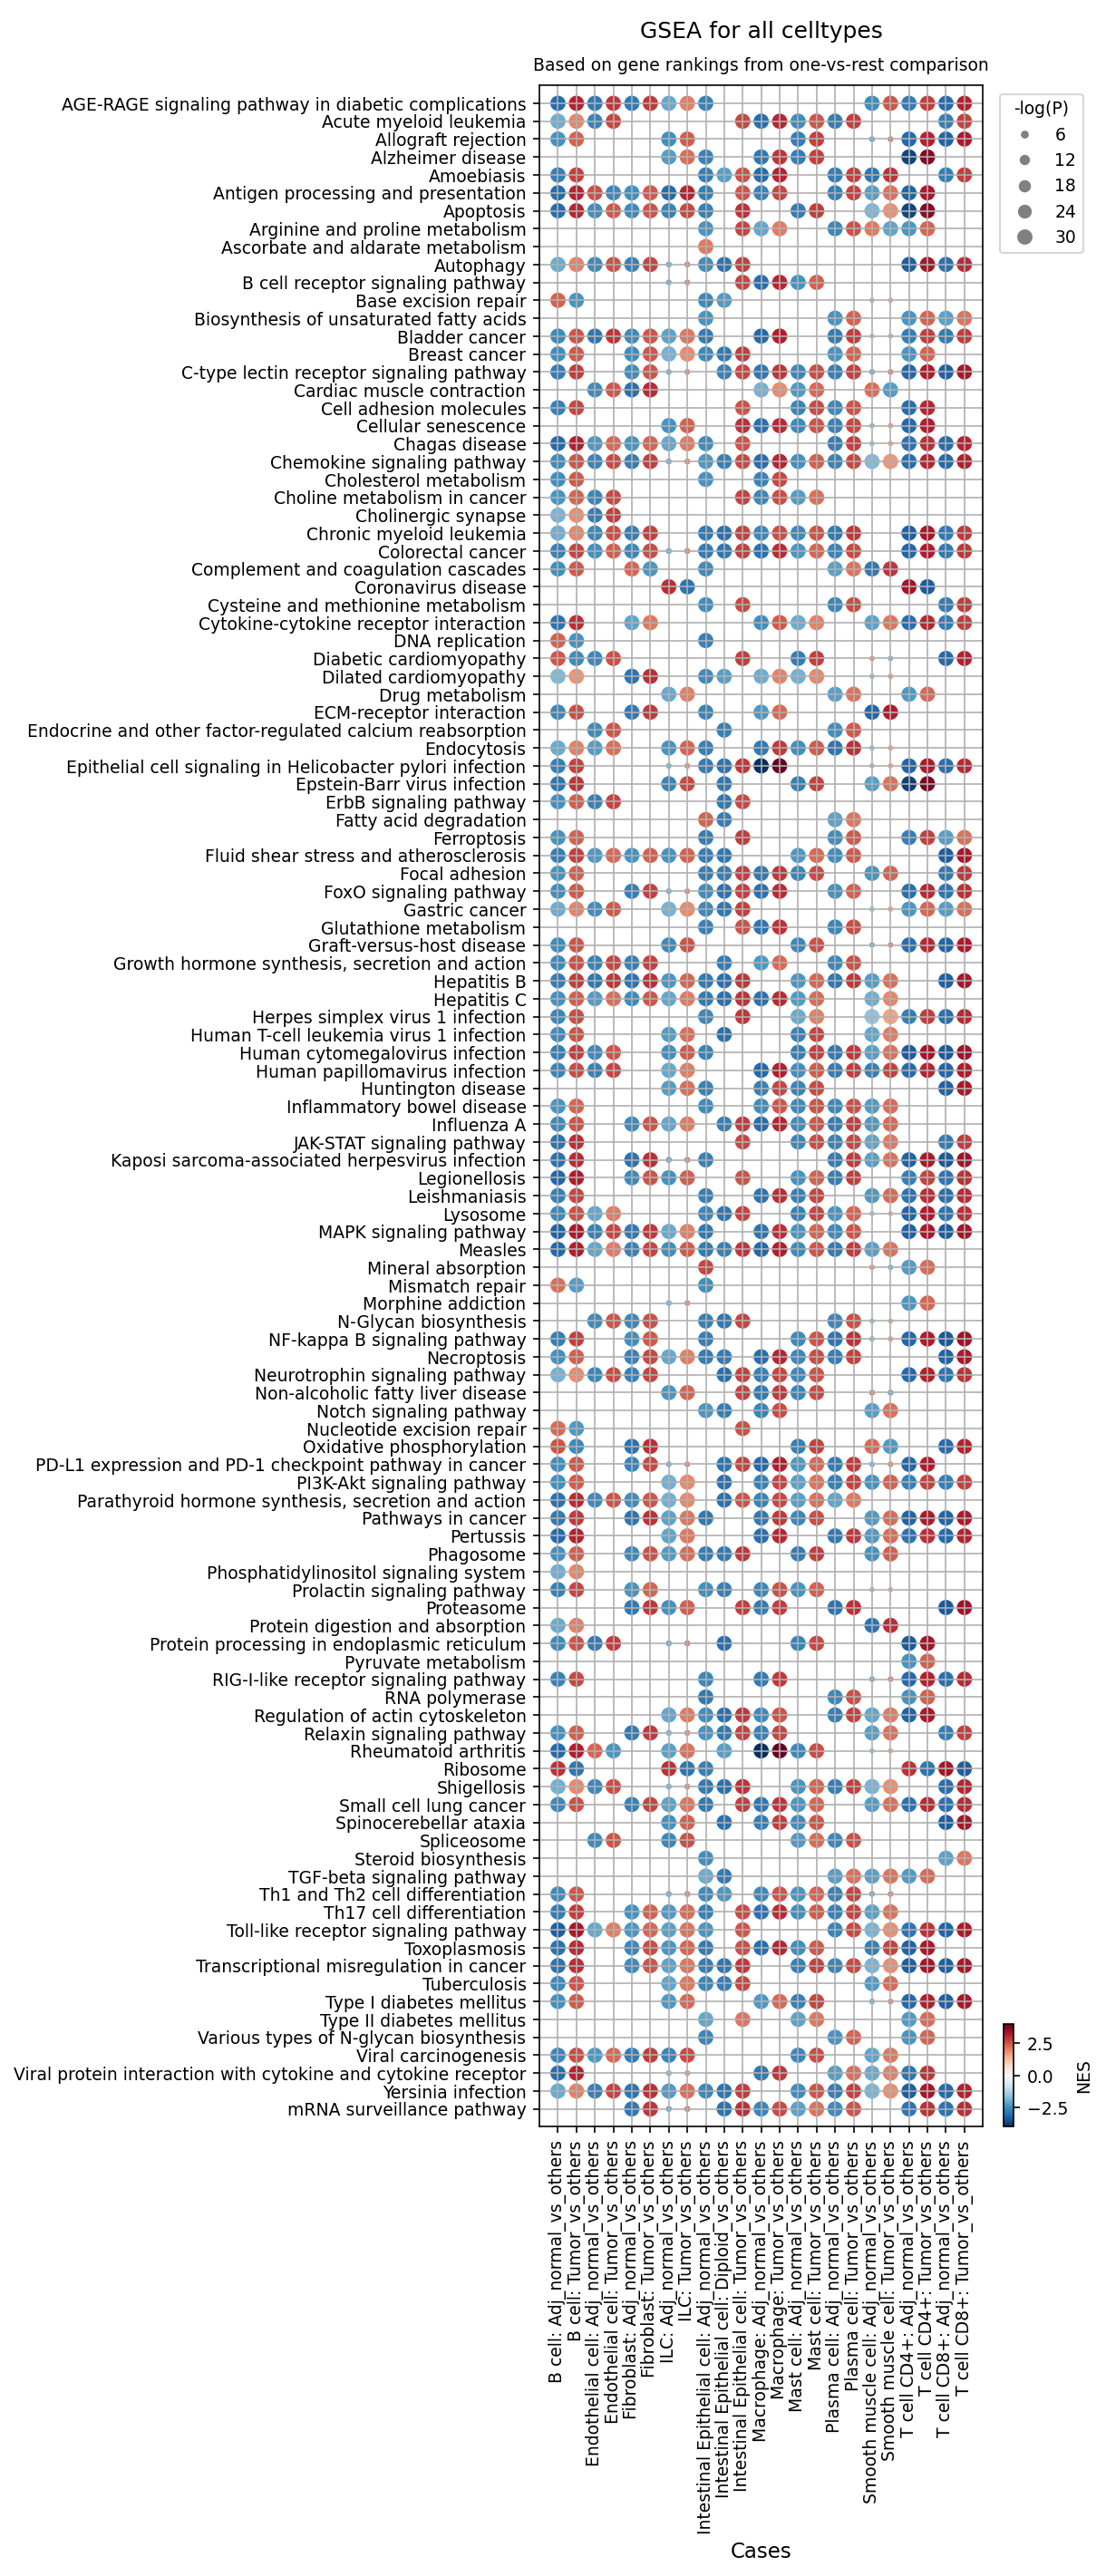
[Analysis Visualization Results]...
Analysis Overview
This dot plot visualizes the results of Gene Set Enrichment Analysis (GSEA) for various cell types identified in single-cell RNA-seq data from human colon tissue. The analysis compares gene expression profiles for each celltype_minor under two conditions: 'Adj_normal' (adjacent normal tissue) and 'Tumor' (tumor tissue), against all other cells in the dataset (one-vs-rest comparison). The aim is to identify biological pathways or processes that are significantly enriched (upregulated) or depleted (downregulated) in specific cell types and conditions. The plot displays 120 gene sets (pathways) with their Normalized Enrichment Score (NES) indicated by dot color (red for positive NES, blue for negative NES) and statistical significance (-log(p-value)) by dot size.
Visual Summary
The GSEA dot plot reveals distinct and comprehensive patterns of pathway enrichment and depletion across different cell types and tissue conditions (Adj_normal vs. Tumor).
- Widespread Pathway Dysregulation: A large number of pathways show significant enrichment or depletion (indicated by varying dot sizes and colors) across most cell types, particularly in the tumor microenvironment.
- Condition-Specific Patterns: For many cell types, there is a clear difference in pathway activity between 'Adj_normal_vs_others' and 'Tumor_vs_others' comparisons. Pathways frequently enriched in tumor cells (positive NES, red dots) often show depletion or less enrichment in adjacent normal cells (negative NES, blue dots), and vice-versa.
- Intestinal Epithelial Cell Specificity: As the resolved tumor-origin cell type, Intestinal Epithelial cells demonstrate strong enrichment for numerous cancer-related pathways in the 'Tumor_vs_others' condition. Notably, a distinct column for 'Intestinal Epithelial cell: Diploid_Tumor_vs_others' shows very similar enrichment patterns to the general 'Intestinal Epithelial cell: Tumor_vs_others' group, suggesting that even diploid tumor cells exhibit a strong oncogenic signature.
- Immune and Stromal Cell Involvement: Immune cells (Macrophage, T cell CD4+, T cell CD8+, B cell, Plasma cell, ILC, Mast cell) and stromal cells (Fibroblast, Endothelial cell, Smooth muscle cell) also exhibit significant pathway alterations in the tumor context, highlighting their active roles in shaping the tumor microenvironment.
- Key Enriched Pathways in Tumor: Pathways like "Colorectal cancer," "PI3K-Akt signaling pathway," "MAPK signaling pathway," "Wnt signaling pathway," "TGF-beta signaling pathway," "PD-L1 expression and PD-1 checkpoint pathway in cancer," "ECM-receptor interaction," "Focal adhesion," "DNA replication," and various inflammatory pathways (e.g., "NF-kappa B signaling pathway," "Chemokine signaling pathway") are frequently positively enriched in tumor-associated cell populations.
- Key Depleted Pathways in Tumor: Conversely, pathways such as "Oxidative phosphorylation," "Fatty acid degradation," and "Mismatch repair" often show negative enrichment or depletion in tumor epithelial cells compared to adjacent normal counterparts.
Biological Interpretation
The GSEA results provide critical insights into the biological processes underpinning colorectal cancer progression and the dynamics of its microenvironment.
- Oncogenic Signaling Activation: The strong positive enrichment of established cancer pathways like PI3K-Akt, MAPK, Wnt, and TGF-beta signaling in Intestinal Epithelial cells (both general tumor and diploid tumor subsets), Fibroblasts, and Endothelial cells underscores their central role in promoting tumor growth, survival, and metastasis. These pathways are frequently hyperactivated in colorectal cancer PubMed Search: PI3K-Akt Wnt MAPK TGF-beta colorectal cancer.
Tumor Microenvironment Remodeling:
- Immune Dysregulation: The PD-L1 expression and PD-1 checkpoint pathway, along with other immune and inflammatory pathways (e.g., NF-kappa B, Chemokine signaling, Cytokine-cytokine receptor interaction), are highly active in various immune cells (T cells, Macrophages, Plasma cells) within the tumor. This indicates an ongoing immune response that is likely shaped by the tumor to promote immune evasion and chronic inflammation, a hallmark of cancer PubMed Search: tumor microenvironment immune evasion colorectal cancer.
- Stromal Reprogramming: Fibroblasts in the tumor context show significant enrichment in ECM-receptor interaction and Focal adhesion pathways, consistent with their transformation into cancer-associated fibroblasts (CAFs) that extensively remodel the extracellular matrix, promoting tumor invasion and metastasis PubMed Search: cancer associated fibroblasts ECM colorectal cancer.
- Metabolic Reprogramming: The depletion of oxidative phosphorylation and fatty acid degradation pathways in tumor epithelial cells compared to normal counterparts suggests a shift towards aerobic glycolysis (Warburg effect), a common metabolic adaptation in rapidly proliferating cancer cells PubMed Search: Warburg effect colorectal cancer.
- MMR Deficiency Implications: The depletion of the "Mismatch repair" pathway in tumor epithelial cells, particularly when compared to adjacent normal cells, aligns with the known prevalence of mismatch repair deficiency (MMR-D) in a significant subset of colorectal cancers, which has implications for genomic instability and response to certain therapies PubMed Search: mismatch repair deficiency colorectal cancer.
- Ploidy and Tumor Heterogeneity: The observation that diploid tumor epithelial cells exhibit similar oncogenic pathway enrichment as the broader tumor epithelial cell population suggests that ploidy status is not the sole determinant of oncogenic transformation. Diploid tumor cells might represent early stages of transformation, specific tumor clones, or a subset of cancer cells maintaining a diploid state while still being highly malignant. This highlights intratumoral heterogeneity.
- Potential Viral Associations: The enrichment of "Viral carcinogenesis" in Intestinal Epithelial cells, Fibroblasts, and Macrophages within the tumor microenvironment is an intriguing finding. While not directly observed as a viral infection, this could suggest activation of host pathways mimicking viral responses or potentially indicate an uncharacterized viral involvement in a subset of tumors.
Clinical or Translational Implications
The comprehensive GSEA findings hold several clinical and translational implications for colorectal cancer:
- Therapeutic Target Identification: The consistently activated oncogenic pathways (e.g., PI3K-Akt, MAPK, Wnt, TGF-beta) across various tumor-associated cell types represent promising targets for novel therapeutic interventions. Multi-target strategies or combination therapies addressing different cell types within the TME might be more effective.
- Immunotherapy Biomarkers: The prominent enrichment of the "PD-L1 expression and PD-1 checkpoint pathway in cancer" in T cells and macrophages within the tumor environment strongly supports the use of immune checkpoint inhibitors in a subset of colorectal cancer patients, particularly those with high PD-L1 expression or MMR-D.
- Targeting the Tumor Microenvironment: The significant alterations in fibroblasts (ECM remodeling) and macrophages (inflammatory signaling) suggest that therapies designed to reprogram CAFs or M2-like macrophages could be beneficial in inhibiting tumor growth and metastasis.
- Metabolic Intervention Strategies: The metabolic shift observed in tumor epithelial cells points to potential therapeutic avenues that target cancer-specific metabolic vulnerabilities, such as glycolysis inhibitors.
- Prognostic and Predictive Markers: The specific GSEA signatures identified for different cell types and conditions could serve as potential prognostic biomarkers to predict disease aggressiveness or as predictive biomarkers to stratify patients for specific targeted or immunotherapies. For instance, a strong activation of MMR pathways in adjacent normal tissue but strong depletion in tumor cells could be a marker of MMR status.
22. Discussion
The single-cell analysis of colorectal tissue revealed a profoundly altered cellular and molecular landscape in tumor samples compared to adjacent normal tissue. A cornerstone finding is the clear distinction between tumor and normal cells, with aneuploidy predominantly observed within the malignant Intestinal Epithelial cell population across diverse tumor samples. This genomic instability, characterized by recurrent copy number amplifications in known oncogenes like MYC (8q24.21), EGFR (7p11.2), and ERBB2 (17q12), and deletions in tumor suppressors like TP53 (17p) and SMAD4 (18q), underscores a fundamental genomic chaos driving colorectal cancer progression. Notably, even 'Diploid Tumor' cells exhibited focal CNVs, suggesting a spectrum of genomic alterations beyond overt aneuploidy.
The tumor microenvironment (TME) undergoes extensive remodeling. We observed a significant increase in tumor-infiltrating immune cells, particularly CD4+ and CD8+ T cells, and macrophages, alongside an expanded fibroblast population indicative of cancer-associated fibroblasts (CAFs). A critical aspect of immune dysregulation is the striking enrichment of immunosuppressive T cell subsets, including regulatory T cells (Tregs), T helper 17 (Th17), regulatory Innate Lymphoid Cells (ILCreg), T helper 22 (Th22), and T helper 9 (Th9) cells, while naive and Th2 T cells were decreased. Macrophages in the tumor tissue demonstrated a pronounced shift towards pro-tumorigenic M2-like phenotypes, with significant increases in M2B and M2C subsets and a reduction in M1 and M2A populations. This re-polarization of macrophages and the influx of immunosuppressive T cell subsets collectively foster an environment conducive to immune evasion and tumor growth.
Cell-cell interaction (CCI) analysis further delineated the complex communication networks driving the TME. While adjacent normal tissue showed sparse, largely homotypic interactions, tumor tissue exhibited dramatically more diverse and stronger heterotypic interactions. Key interactions included extensive collagen-integrin complexes between fibroblasts and endothelial cells, promoting extracellular matrix remodeling and angiogenesis. Oncogenic signaling pathways like EGFR (autocrine/paracrine within tumor epithelial cells) and TGFB1 (autocrine in tumor cells and heterotypic with macrophages/fibroblasts) were highly active. Crucially, the PD-1/PD-L1 immune checkpoint interaction (CD274_PDCD1) between tumor epithelial cells and CD8+ T cells was robustly engaged, a classic mechanism of immune evasion. Other pro-tumorigenic interactions like SPP1-integrin (promoting adhesion/migration), JAG1-NOTCH1 (angiogenesis/stemness), and PGE2-PTGER4 (immunosuppression) also highlighted active crosstalk within the TME.
The malignant intestinal epithelial cells displayed pervasive and highly significant upregulation of cell cycle pathway genes (e.g., CCND1, CDK4, MYC, MCMs), indicating uncontrolled proliferation. Gene Ontology and GSEA consistently reinforced these findings, showing strong enrichment of cancer hallmarks like PI3K-Akt, MAPK, Wnt, TGF-beta signaling, DNA replication, and altered metabolic pathways (e.g., depleted oxidative phosphorylation, enriched endocytosis/autophagy) in tumor epithelial cells. An unexpected but consistent finding was the enrichment of various viral and bacterial infection pathways in tumor epithelial cells, suggesting a potential role of pathogens or chronic inflammation in colorectal cancer pathogenesis, which warrants further investigation. Furthermore, neurodegenerative disease-related pathways appeared across both normal and tumor epithelial cells, indicating shared fundamental cellular stress responses. The collective findings underscore the profound and multifaceted reprogramming of both tumor cells and their surrounding microenvironment in colorectal cancer.
Hypotheses:
- The extensive genomic instability, characterized by recurrent CNVs (e.g., MYC, EGFR, ERBB2 amplifications), drives specific oncogenic programs and contributes to the observed inter-patient and intra-tumor heterogeneity in colorectal cancer.
- The coordinated increase of diverse immunosuppressive (Treg, ILCreg) and pro-inflammatory (Th17, Th22, Th9) T cell subsets, alongside the polarization of tumor-associated macrophages (TAMs) towards an M2-like phenotype (M2B, M2C), collectively establishes an immune-evasive and tumor-promoting microenvironment in colorectal cancer.
- Aberrant cell-cell interactions, particularly involving integrin-mediated adhesion, EGFR, TGFB1, PD-1/PD-L1, and Notch signaling, extensively remodel the tumor microenvironment, supporting tumor epithelial cell proliferation, stromal activation, angiogenesis, and immune evasion.
- Colorectal tumor epithelial cells exhibit a unique metabolic reprogramming, characterized by enhanced nutrient uptake (endocytosis), cellular recycling (autophagy), and altered energy metabolism (depleted oxidative phosphorylation), to sustain uncontrolled proliferation and survival.
- Upregulation of specific surfaceome markers (e.g., CDH17, MUC13, LY6E, ITGA6, SDC1) on tumor epithelial cells and unique surface markers on CAFs (e.g., PDGFRB, CDH11, ITGAV) and TAMs (e.g., CD36, PLAUR, GPNMB) contributes to colorectal cancer progression by enhancing cell adhesion, migration, survival, and immune evasion.
Potential therapeutic targets:
- EGFR (Epidermal Growth Factor Receptor): Autocrine/paracrine EGFR signaling is widely active in aneuploid Intestinal Epithelial cells, driving tumor cell proliferation, survival, angiogenesis, and metastasis. This is a primary oncogenic driver in CRC. Evidence: Prominent 7p11.2 amplification (Section 4); widespread EGFR-ligand/EGFR interactions (HBEGF_EGFR, EREG_EGFR, TGFA_EGFR, BTC_EGFR) strongly active in tumor epithelial cells (Section 14); strong positive enrichment of 'MAPK signaling pathway' and 'PI3K-Akt signaling pathway' in tumor epithelial cells (Section 21). Validation: Clinical efficacy of EGFR inhibitors (cetuximab, panitumumab) in KRAS/NRAS/BRAF wild-type mCRC; preclinical testing in patient-derived organoids/xenografts with EGFR overexpression/amplification.
- PD-1 / PD-L1 (Programmed Death-1 / Programmed Death-Ligand 1): The PD-1/PD-L1 axis is a canonical immune checkpoint exploited by tumor cells to evade anti-tumor immunity by inducing T cell exhaustion. Blocking this pathway can restore T cell function. Evidence: Highly active CD274_PDCD1 interaction between aneuploid Intestinal Epithelial (tumor) cells and CD8+ T cells (Section 14); 'PD-L1 expression and PD-1 checkpoint pathway in cancer' strongly enriched in T cells and macrophages within the tumor (Section 21); upregulation of CTLA4 and TIGIT (other checkpoints) on CD4+ T cells (Section 18). Validation: Approved PD-1 (pembrolizumab, nivolumab) and PD-L1 (atezolizumab, durvalumab) inhibitors show significant efficacy in MSI-H/dMMR colorectal cancer; preclinical testing for combination therapies in other CRC subtypes.
- TGF-beta Signaling Pathway (via TGFB1 and its receptors): TGFB1 signaling is extensively involved in diverse cell interactions within the tumor microenvironment, promoting epithelial-mesenchymal transition (EMT), immune suppression, angiogenesis, and fibrosis. Evidence: Multiple strong interactions involving TGFB1 and its receptors (TGFbeta_receptor1, TGFbeta_receptor2, TGFBR3) spanning tumor epithelial cells, macrophages, and fibroblasts (Section 14); 'TGF-beta signaling pathway' strongly enriched in tumor-associated cells (Section 21). Validation: Clinical trials with TGF-beta inhibitors (e.g., galunisertib, fresolimumab, TGF-beta receptor kinase inhibitors), often in combination with chemotherapy or immunotherapy, to overcome immunosuppression and reduce tumor fibrosis.
- Integrin-Mediated Interactions (e.g., ITGA6, ITGAV, and their complexes): Integrins are critical for cell adhesion, migration, proliferation, and interaction with the extracellular matrix (ECM). Their widespread involvement in tumor epithelial cells and CAFs promotes invasion, metastasis, and stromal remodeling. Evidence: Numerous collagen-integrin and SPP1-integrin interactions prominently enriched in tumor cell-cell interactions, particularly between Fibroblasts and Endothelial cells, and Endothelial cells and Macrophages (Sections 12, 13); ITGA6 highly upregulated on tumor epithelial cells (Section 15); ITGAV and CD44 highly upregulated on tumor fibroblasts (Section 17); 'ECM-receptor interaction' and 'Focal adhesion' pathways enriched in tumor-associated cells (Section 21). Validation: Development of specific integrin inhibitors (e.g., αvβ3/αvβ5 inhibitors like cilengitide), or antibodies targeting specific integrin subunits (e.g., anti-ITGA6 or anti-ITGAV antibodies) to disrupt tumor cell adhesion, invasion, and CAF activity.
- Macrophage Repolarization (via CD36, PLAUR, GPNMB): Tumor-associated macrophages (TAMs) are significantly polarized towards pro-tumorigenic M2-like phenotypes (M2B, M2C), promoting tumor growth, angiogenesis, and immune suppression. Repolarizing or depleting these TAMs can be therapeutic. Evidence: Significant increase in M2B and M2C macrophage subsets in tumors (Section 10); high expression of CD36, PLAUR, GPNMB on tumor macrophages (Section 16). These markers are associated with lipid metabolism, ECM degradation, and immunosuppression. Validation: Strategies to inhibit CD36 (small molecules), PLAUR (antibodies/inhibitors), or GPNMB (ADCs like Glembatumumab vedotin) to reduce TAM pro-tumorigenic functions or deplete TAMs, potentially combined with checkpoint inhibitors.
- CDK4/6 (Cyclin-Dependent Kinases 4 and 6): CDK4/6 are crucial for G1-S phase progression. Their widespread activation drives uncontrolled proliferation, a hallmark of cancer in malignant intestinal epithelial cells. Evidence: CCND1 (Cyclin D1) and CDK4 show marked, highly significant upregulation in the fraction of expressing cells within tumor Intestinal Epithelial cells (Section 19); 'Cell cycle' pathway highly enriched in tumor epithelial cells (Section 20); 'DNA replication' pathway enriched in tumor-associated cells (Section 21). Validation: Clinical trials with CDK4/6 inhibitors (e.g., palbociclib, abemaciclib, ribociclib) in colorectal cancer, particularly in specific molecular subtypes, or in combination with other therapies to overcome resistance.
Follow-up validation ideas:
- Perform flow cytometry or immunohistochemistry on independent human colorectal cancer (CRC) patient cohorts to validate shifts in T cell (Treg, Th17, ILCreg, Th2, T_Naive) and macrophage (M1, M2A, M2B, M2C) subset proportions, as well as CAF numbers (e.g., α-SMA, FAP) and spatial distribution.
- Utilize spatial transcriptomics or proteomics to investigate the precise spatial localization and co-expression of identified cell types and key ligand-receptor interactions (e.g., PD-L1/PD-1, Collagen-Integrin, SPP1-integrin, JAG1-NOTCH1) within tumor and adjacent normal tissues.
- Conduct functional _in vitro_ co-culture assays using patient-derived organoids, primary immune cells, and fibroblasts to elucidate the causal impact of specific cell-cell interactions (e.g., EGFR ligands on tumor epithelial cells, HBEGF from macrophages to tumor cells, PGE2 from macrophages to T cells) on tumor cell proliferation, migration, and immune cell polarization.
- Validate differential expression of key marker genes (e.g., EPCAM, CEACAM5, CD47, CDH17, MUC13, PDGFRB, CD36, CTLA4) and cell cycle regulators (e.g., CCND1, CDK4, MYC) via targeted qPCR or Western blot in sorted cell populations from fresh patient samples or orthogonal bulk omics data.
- Perform FISH or targeted sequencing on additional CRC samples to confirm recurrent amplifications (e.g., MYC, EGFR, ERBB2) and deletions (e.g., TP53) in malignant epithelial cells and correlate these genomic alterations with disease progression and therapeutic response.
- Conduct perturbation assays in preclinical models (e.g., patient-derived xenografts or genetically engineered mouse models of CRC) to test the therapeutic efficacy of targeting identified pathways and markers using small molecule inhibitors, antibodies, or genetic tools, both as single agents and in combination strategies.
Limitations:
This report is based on an inferred disease context from dataset metadata and observed single-cell analysis results, not a definitive clinical diagnosis. While the analyses identify strong associations and potential mechanisms, further functional validation is required to establish causality. The single-cell RNA-seq data provides a snapshot of the cellular and molecular landscape, but does not capture temporal dynamics of disease progression or treatment response. Some rare cell types or transient states may be undersampled or challenging to resolve. While sample integration was generally good, subtle patient-specific heterogeneity or residual technical variations may exist. Further clinical correlation with patient outcomes is needed to establish the definitive prognostic or predictive value of the identified biomarkers and therapeutic targets.
23. Query List
- Show and save UMAPs for condition, sample, major cell type, minor cell type, ploidy_dec, and celltype_subset in two columns.
- Show major cell type scores on UMAP and save the result.
- Show and save a marker expression dot plot for celltype_subset. SET target_cell = None and var_group_rotation = 45. Leave all other arguments at their default values.
- Select tumor-origin cells, show a CNV heatmap grouped by sample together with a summary of regions with significantly amplified copy numbers, and save the results.
- Show and save UMAPs of CNV patterns colored by major cell type, minor cell type, ploidy results, condition, and sample in two columns.
- Show and save a population bar plot of minor cell types.
- Show and save a population bar plot of T cell subsets.
- Show and save box plots of T cell subset populations with statistically significant differences between conditions, if any. Choose ncols based on the total number of panels.
- Show and save a population bar plot of macrophage subsets.
- Show and save box plots of macrophage subset populations with statistically significant differences between conditions, if any. Choose ncols based on the total number of panels.
- Select tumor-origin cells, show their ploidy populations as a bar plot, and save the result.
- Show and save cell-cell interaction patterns involving Intestinal Epithelial cells, Fibroblasts, Macrophages, T cells, and other relevant cell types. Select at most 80 cell-cell interactions per group.
- Find cell-cell interactions involving Intestinal Epithelial cells, major immune and stromal cells that differ significantly between conditions, show them as a dot plot, and save the result. Set max_n_items_per_group to 60. For each interaction identified under each condition, using the provided dataset context, describe the associated signaling pathways and mechanisms, its potential as a therapeutic target, and relevant therapeutic agents.
- Find cell-cell interactions containing immune checkpoint and cell cycle pathway genes and involving Intestinal Epithelial cells, major immune and stromal cells that differ significantly between conditions, show them as a dot plot, and save the result. Set max_n_items_per_group to 60. For each interaction identified under each condition, using the provided dataset context, describe the associated signaling pathways and mechanisms, its potential as a therapeutic target, and relevant therapeutic agents.
- Show marker expressions for Intestinal Epithelial cells in a dot plot, and save the result. Use only surfaceome markers, with at most 60 markers per condition. For the markers identified under each condition, distinguish between established therapeutic targets and less well-characterized markers with potential as therapeutic targets. For each marker, using the provided dataset context, describe the associated signaling pathways and mechanisms, relevant therapeutic agents, and supporting evidence.
- Show marker expressions for Macrophage in a dot plot, and save the result. Use only surfaceome markers, with at most 40 markers per condition. For each marker identified under each condition, using the provided dataset context, describe the associated signaling pathways, the role of the corresponding cell type in the tumor microenvironment, the marker’s potential as a therapeutic target, relevant therapeutic agents, and other pertinent information.
- Show marker expressions for Fibroblast in a dot plot, and save the result. Use only surfaceome markers, with at most 40 markers per condition. For each marker identified under each condition, using the provided dataset context, describe the associated signaling pathways, the role of the corresponding cell type in the tumor microenvironment, the marker’s potential as a therapeutic target, relevant therapeutic agents, and other pertinent information.
- Show marker expressions for T cell CD4+ in a dot plot, and save the result. Use only surfaceome markers, with at most 40 markers per condition. For each marker identified under each condition, using the provided dataset context, describe the associated signaling pathways, the role of the corresponding cell type in the tumor microenvironment, the marker’s potential as a therapeutic target, relevant therapeutic agents, and other pertinent information.
- Among cell cycle pathway genes, select those with statistically significant expression differences between conditions in major disease-related cells, show box plots, and save the result. Set max_n_items_to_plot to 24 and choose ncols based on the total number of panels for an overall width-to-height ratio of approximately 2:3.
- Show and save Gene Ontology (GSA) analysis results for Intestinal Epithelial cells as a bar plot.
- Show Gene Set Enrichment Analysis results as a dot plot, and save it. Set the color map to RdBu_r, n_pws_to_show to 120, and target_cells to None.